What Is Hip Dysplasia Explained In Dogs Anatomy Symptoms Treatment
Table of Contents
- Anatomical and Physiological Changes in Canine Hip Dysplasia
- Anatomical Alterations in Dysplastic vs. Normal Hip Joints
- Radiographic Diagnosis: OFA and PennHIP Methods
- OFA Scoring System
- PennHIP Method: Quantifying Joint Laxity
- Clinical Signs and Progression of Hip Dysplasia in Dogs
- Staged Progression of Clinical Signs
- Symptom-to-Severity Flowchart for Owner Monitoring
- Flowchart: Clinical Signs vs. Likely Dysplasia Stage
- Influencing Factors: Age, Weight, and Activity Level
- Veterinary Assessment Checklist for Hip Dysplasia
- Advanced Diagnostic Methods and Early Detection Strategies in Canine Hip Dysplasia
- Advanced Imaging Techniques in Hip Dysplasia Diagnosis
- PennHIP Evaluation Procedure and Joint Laxity Analysis
- Comparison of Blood Biomarkers and Traditional Imaging in Early Detection
- Breed-Specific and Age-Based Diagnostic Protocols
- Treatment and Management Strategies for Canine Hip Dysplasia
- Tiered Treatment Table by Disease Severity
- Step-by-Step Post-Surgical Rehabilitation Protocol
- FAQ
- what is hip dysplasia in dogs symptoms?
- what is hip dysplasia in dogs treatment?
- what is hip dysplasia in dogs uk?
- what is hip dysplasia in dogs look like?
- what is hip dysplasia in dogs causes?
- what is bilateral hip dysplasia in dogs?
Hip dysplasia in dogs represents a complex developmental disorder affecting the hip joints, characterized by progressive joint degeneration that compromises mobility and quality of life. This condition arises from a combination of genetic predispositions—particularly in large and giant breeds such as German Shepherds, Labradors, and Bulldogs—and environmental factors like rapid growth, excessive weight, or improper nutrition. Beyond structural abnormalities such as shallow acetabular sockets and malformed femoral heads, hip dysplasia triggers secondary osteoarthritis, leading to chronic pain, lameness, and reduced physical function. Understanding its multifaceted etiology, from radiographic diagnostics like the PennHIP method to advanced imaging techniques, is critical for early intervention and long-term management.
The progression of hip dysplasia follows a predictable yet variable trajectory, influenced by breed-specific risks, activity levels, and age-related wear. While some dogs exhibit subclinical signs—such as mild gait abnormalities or reluctance to engage in high-impact activities—others advance to severe osteoarthritis, manifesting as non-weight-bearing lameness, muscle atrophy, and palpable joint pain. Diagnostic accuracy hinges on a multimodal approach, integrating radiographic scoring systems, blood biomarkers, and breed-tailored protocols to distinguish early-stage dysplasia from irreversible degenerative changes. Treatment strategies range from conservative measures like weight management and physical therapy to advanced surgical interventions, each selected based on the severity of joint compromise and the dog’s overall health.
Anatomical and Physiological Changes in Canine Hip Dysplasia
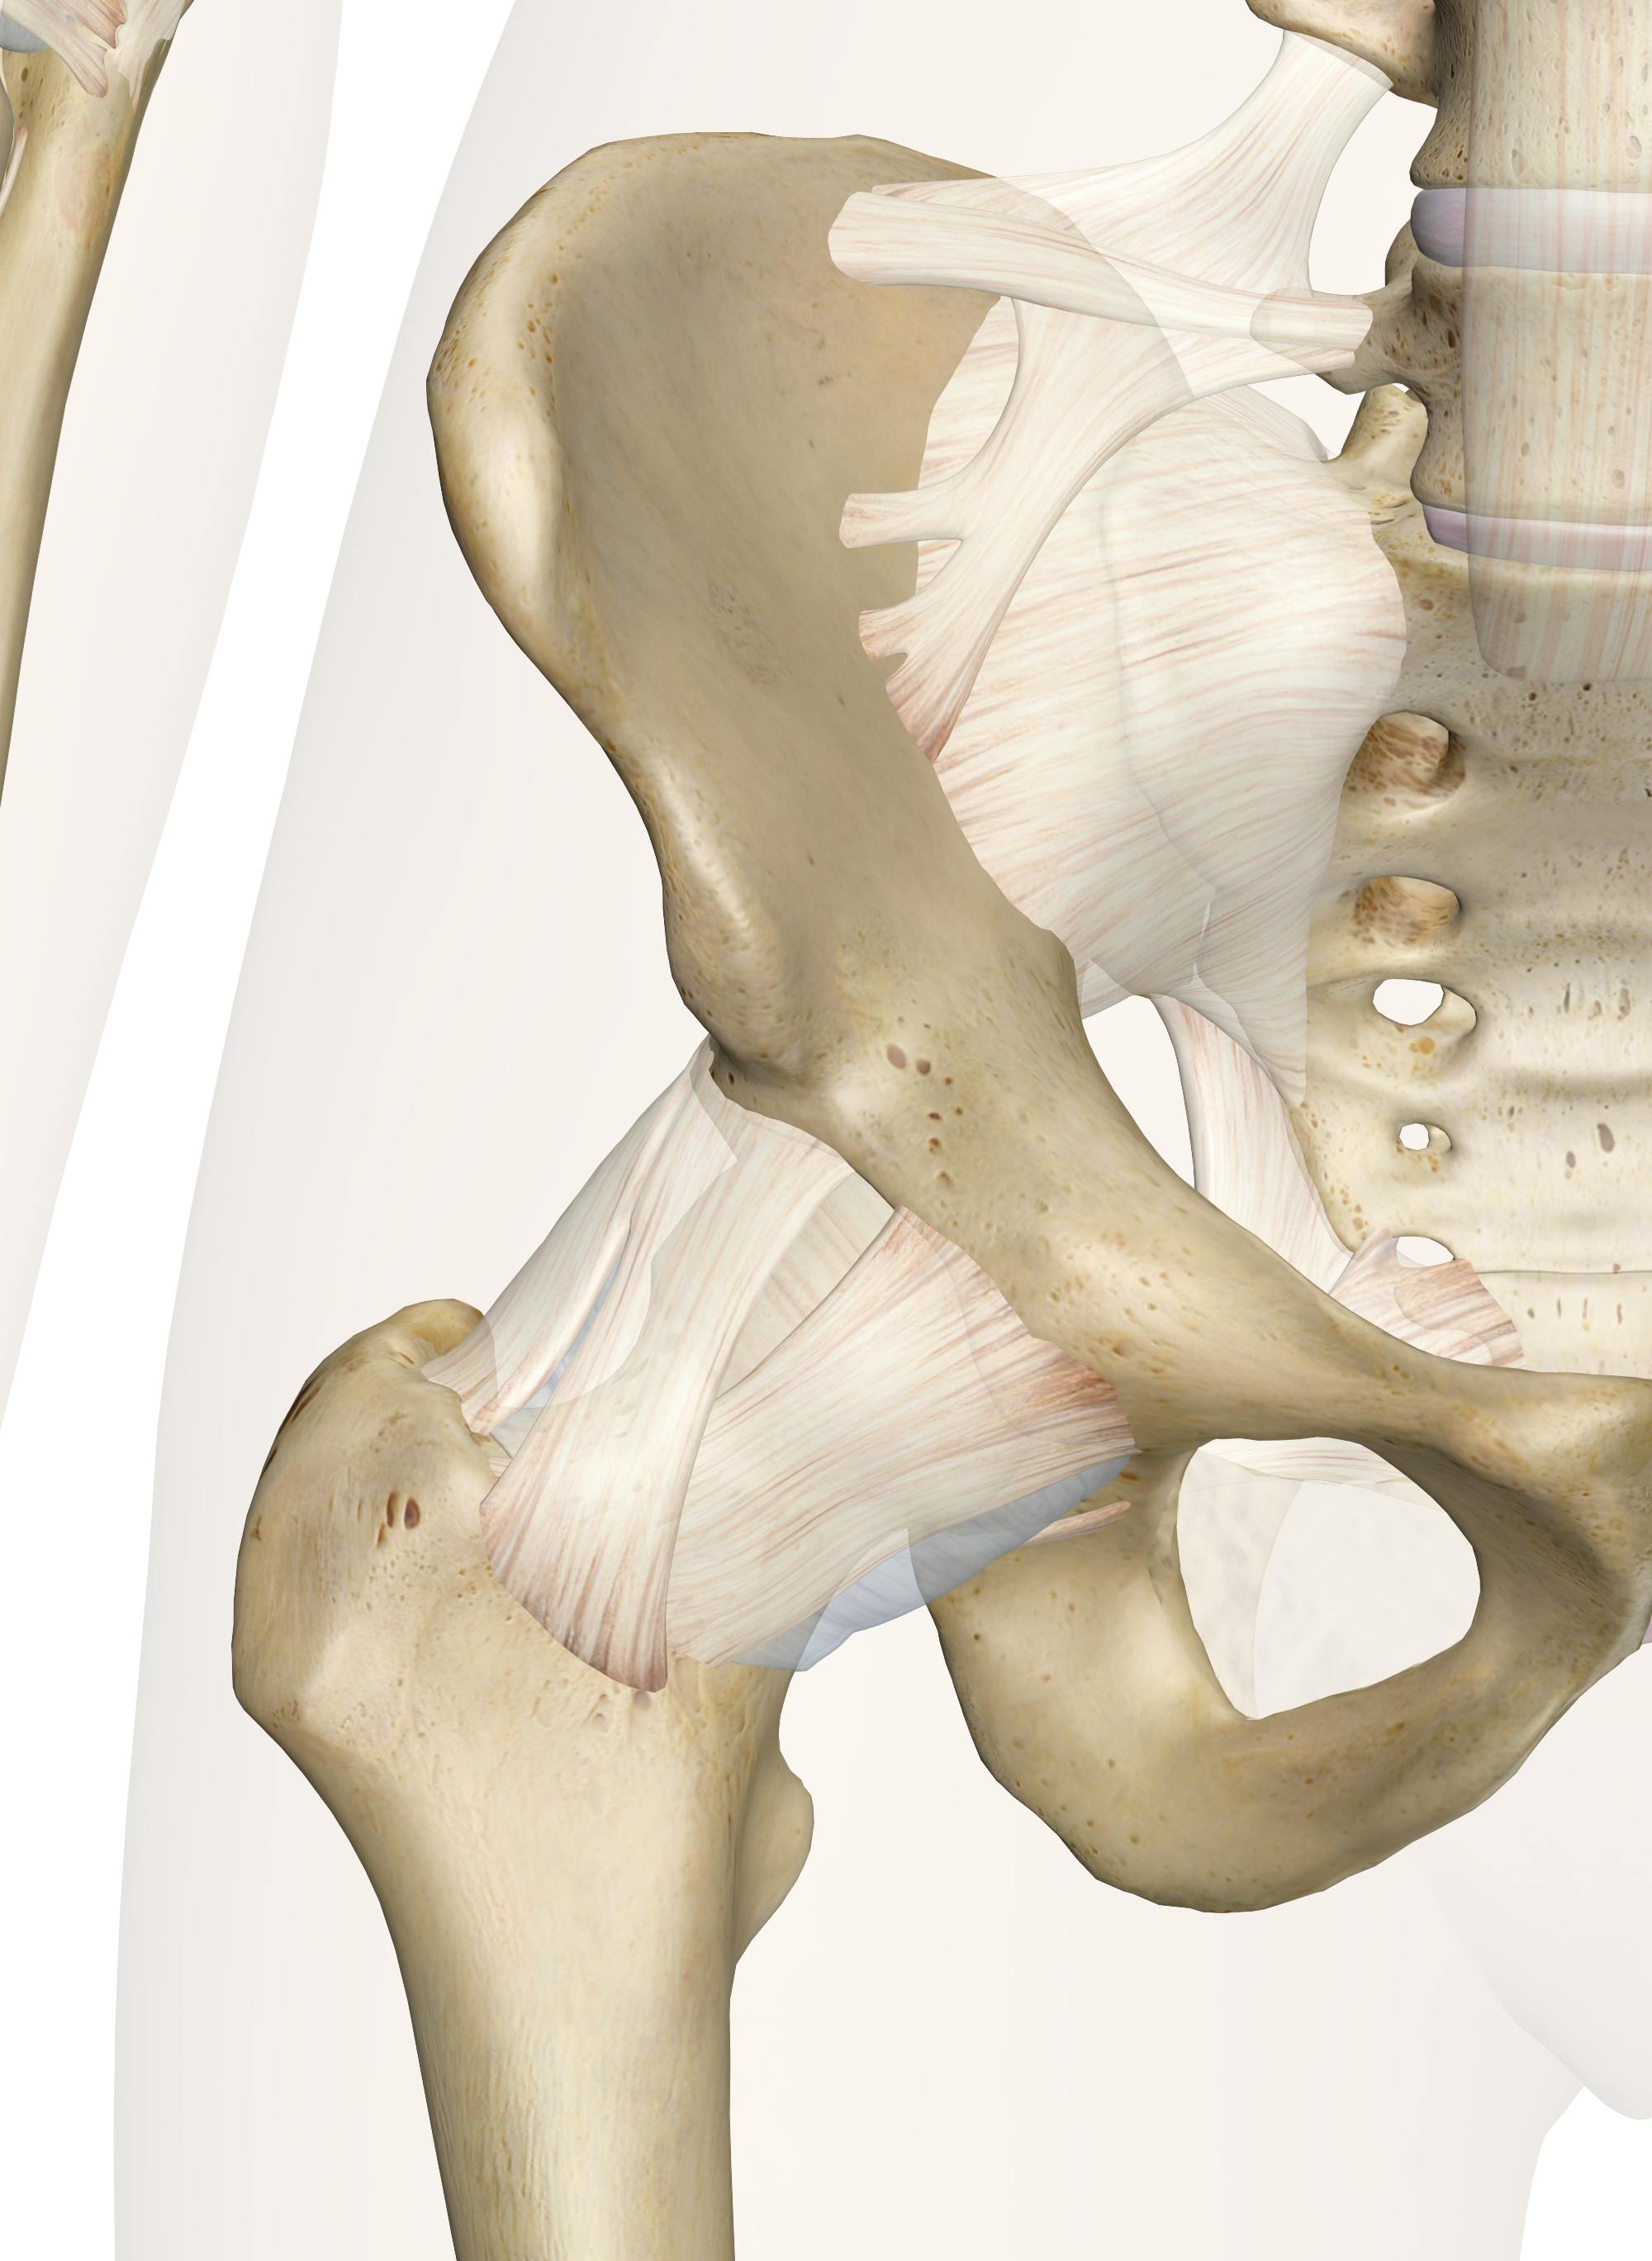
Canine hip dysplasia (CHD) represents a complex developmental orthopedic disorder characterized by abnormal formation and function of the hip joints. The condition arises from a combination of genetic predisposition, rapid growth rates, and environmental influences, leading to progressive joint degeneration. Key anatomical alterations include laxity of the hip joint capsule, shallow acetabular sockets, and malformation of the femoral head, which collectively compromise joint stability and predispose dogs to osteoarthritis. These structural deficiencies disrupt biomechanical forces, accelerating cartilage erosion and subchondral bone remodeling.The progression of CHD involves both primary and secondary pathological changes. Initially, the joint laxity allows excessive movement of the femoral head within the acetabulum, reducing contact area and increasing stress on articular cartilage. Over time, this mechanical instability triggers inflammatory responses, leading to cartilage degradation and the formation of osteophytes (bone spurs) as a compensatory reaction. Concurrently, bone malformation manifests as irregularities in the femoral head-neck junction and acetabular rim, further destabilizing the joint. These changes are not isolated to the hip but often correlate with systemic skeletal abnormalities, such as patellar luxation or elbow dysplasia.
Anatomical Alterations in Dysplastic vs. Normal Hip Joints
The primary distinction between a normal hip joint and a dysplastic hip lies in the acetabular coverage of the femoral head, joint congruency, and subchondral bone integrity. Below is a comparative analysis of critical anatomical features, emphasizing radiographic and gross morphological differences.Key Radiographic Indicators of Hip Dysplasia:
Acetabular depth: Shallow or improperly oriented acetabulum. Femoral head positioning: Poorly seated within the socket, often with lateral subluxation. Joint space: Narrowing due to cartilage loss or irregularities. Osteophytes: Presence of bony outgrowths along joint margins.
| Feature | Normal Hip Anatomy | Dysplastic Hip Anatomy | Radiographic/Visual Description |
|---|---|---|---|
| Socket Depth (Acetabulum) | Deep, concave, and fully encompassing the femoral head. | Shallow, flat, or improperly angled, failing to cover ≥50% of the femoral head. |
|
| Femoral Head Positioning | Centered within the acetabulum with minimal lateral excursion. | Laterally subluxated or displaced, often with a "shallow seat" appearance. |
|
| Joint Space Width | Uniform and consistent, reflecting intact cartilage thickness. | Irregular or narrowed, with focal areas of collapse or sclerosis. |
|
| Presence of Osteophytes | Absent; smooth joint margins. | Prominent bony outgrowths at joint margins, particularly dorsally and ventrally. |
|
Radiographic Diagnosis: OFA and PennHIP Methods
Diagnosing hip dysplasia requires specialized radiographic techniques to assess joint congruency, bone morphology, and early degenerative changes. The two most widely used systems—OFA scoring and PennHIP evaluation—provide complementary insights into the severity and progression of CHD.Critical Radiographic Views for Hip Dysplasia Assessment:
Extended hip view (OFA): Standardized lateral view with hips extended and legs parallel. Compression and distraction views (PennHIP): Additional views under anesthesia to quantify joint laxity.
OFA Scoring System
The OFA system classifies hip dysplasia based on a 7-point grading scale, primarily evaluating acetabular coverage and femoral head positioning. Radiographs are submitted to the OFA for blinded evaluation by board-certified radiologists. The grading criteria are as follows:-
Excellent (Grade 1):
- Complete acetabular coverage of the femoral head (≥75%).
- No subluxation or osteophytes.
- Smooth joint margins with uniform joint space.
-
Good (Grade 2):
- Minimal acetabular coverage loss (≤25%).
- No subluxation; possible mild osteophytes.
- Joint space may show early narrowing.
-
Fair (Grade 3):
- Moderate coverage loss (25–50%).
- Mild subluxation or osteophytes present.
- Focal joint space irregularities.
-
Borderline (Grade 4):
- Severe coverage loss (>50%).
- Obvious subluxation and osteophytes.
- Advanced joint space narrowing.
-
Mild Dysplasia (Grade 5):
- Marked subluxation with minimal coverage.
- Prominent osteophytes and subchondral sclerosis.
-
Moderate Dysplasia (Grade 6):
- Severe subluxation with femoral head displacement.
- Extensive osteophytes and joint remodeling.
-
Severe Dysplasia (Grade 7):
- Complete dislocation or near-dislocation.
- Massive osteophyte formation and bone deformation.
- Advanced osteoarthritis with joint ankylosis.
PennHIP Method: Quantifying Joint Laxity
Developed at the University of Pennsylvania, the PennHIP system evaluates hip joint laxity using three radiographic views:1. Extended view (standard OFA position).
2. Compression view (hips compressed medially).
3. Distraction view (
Clinical Signs and Progression of Hip Dysplasia in Dogs
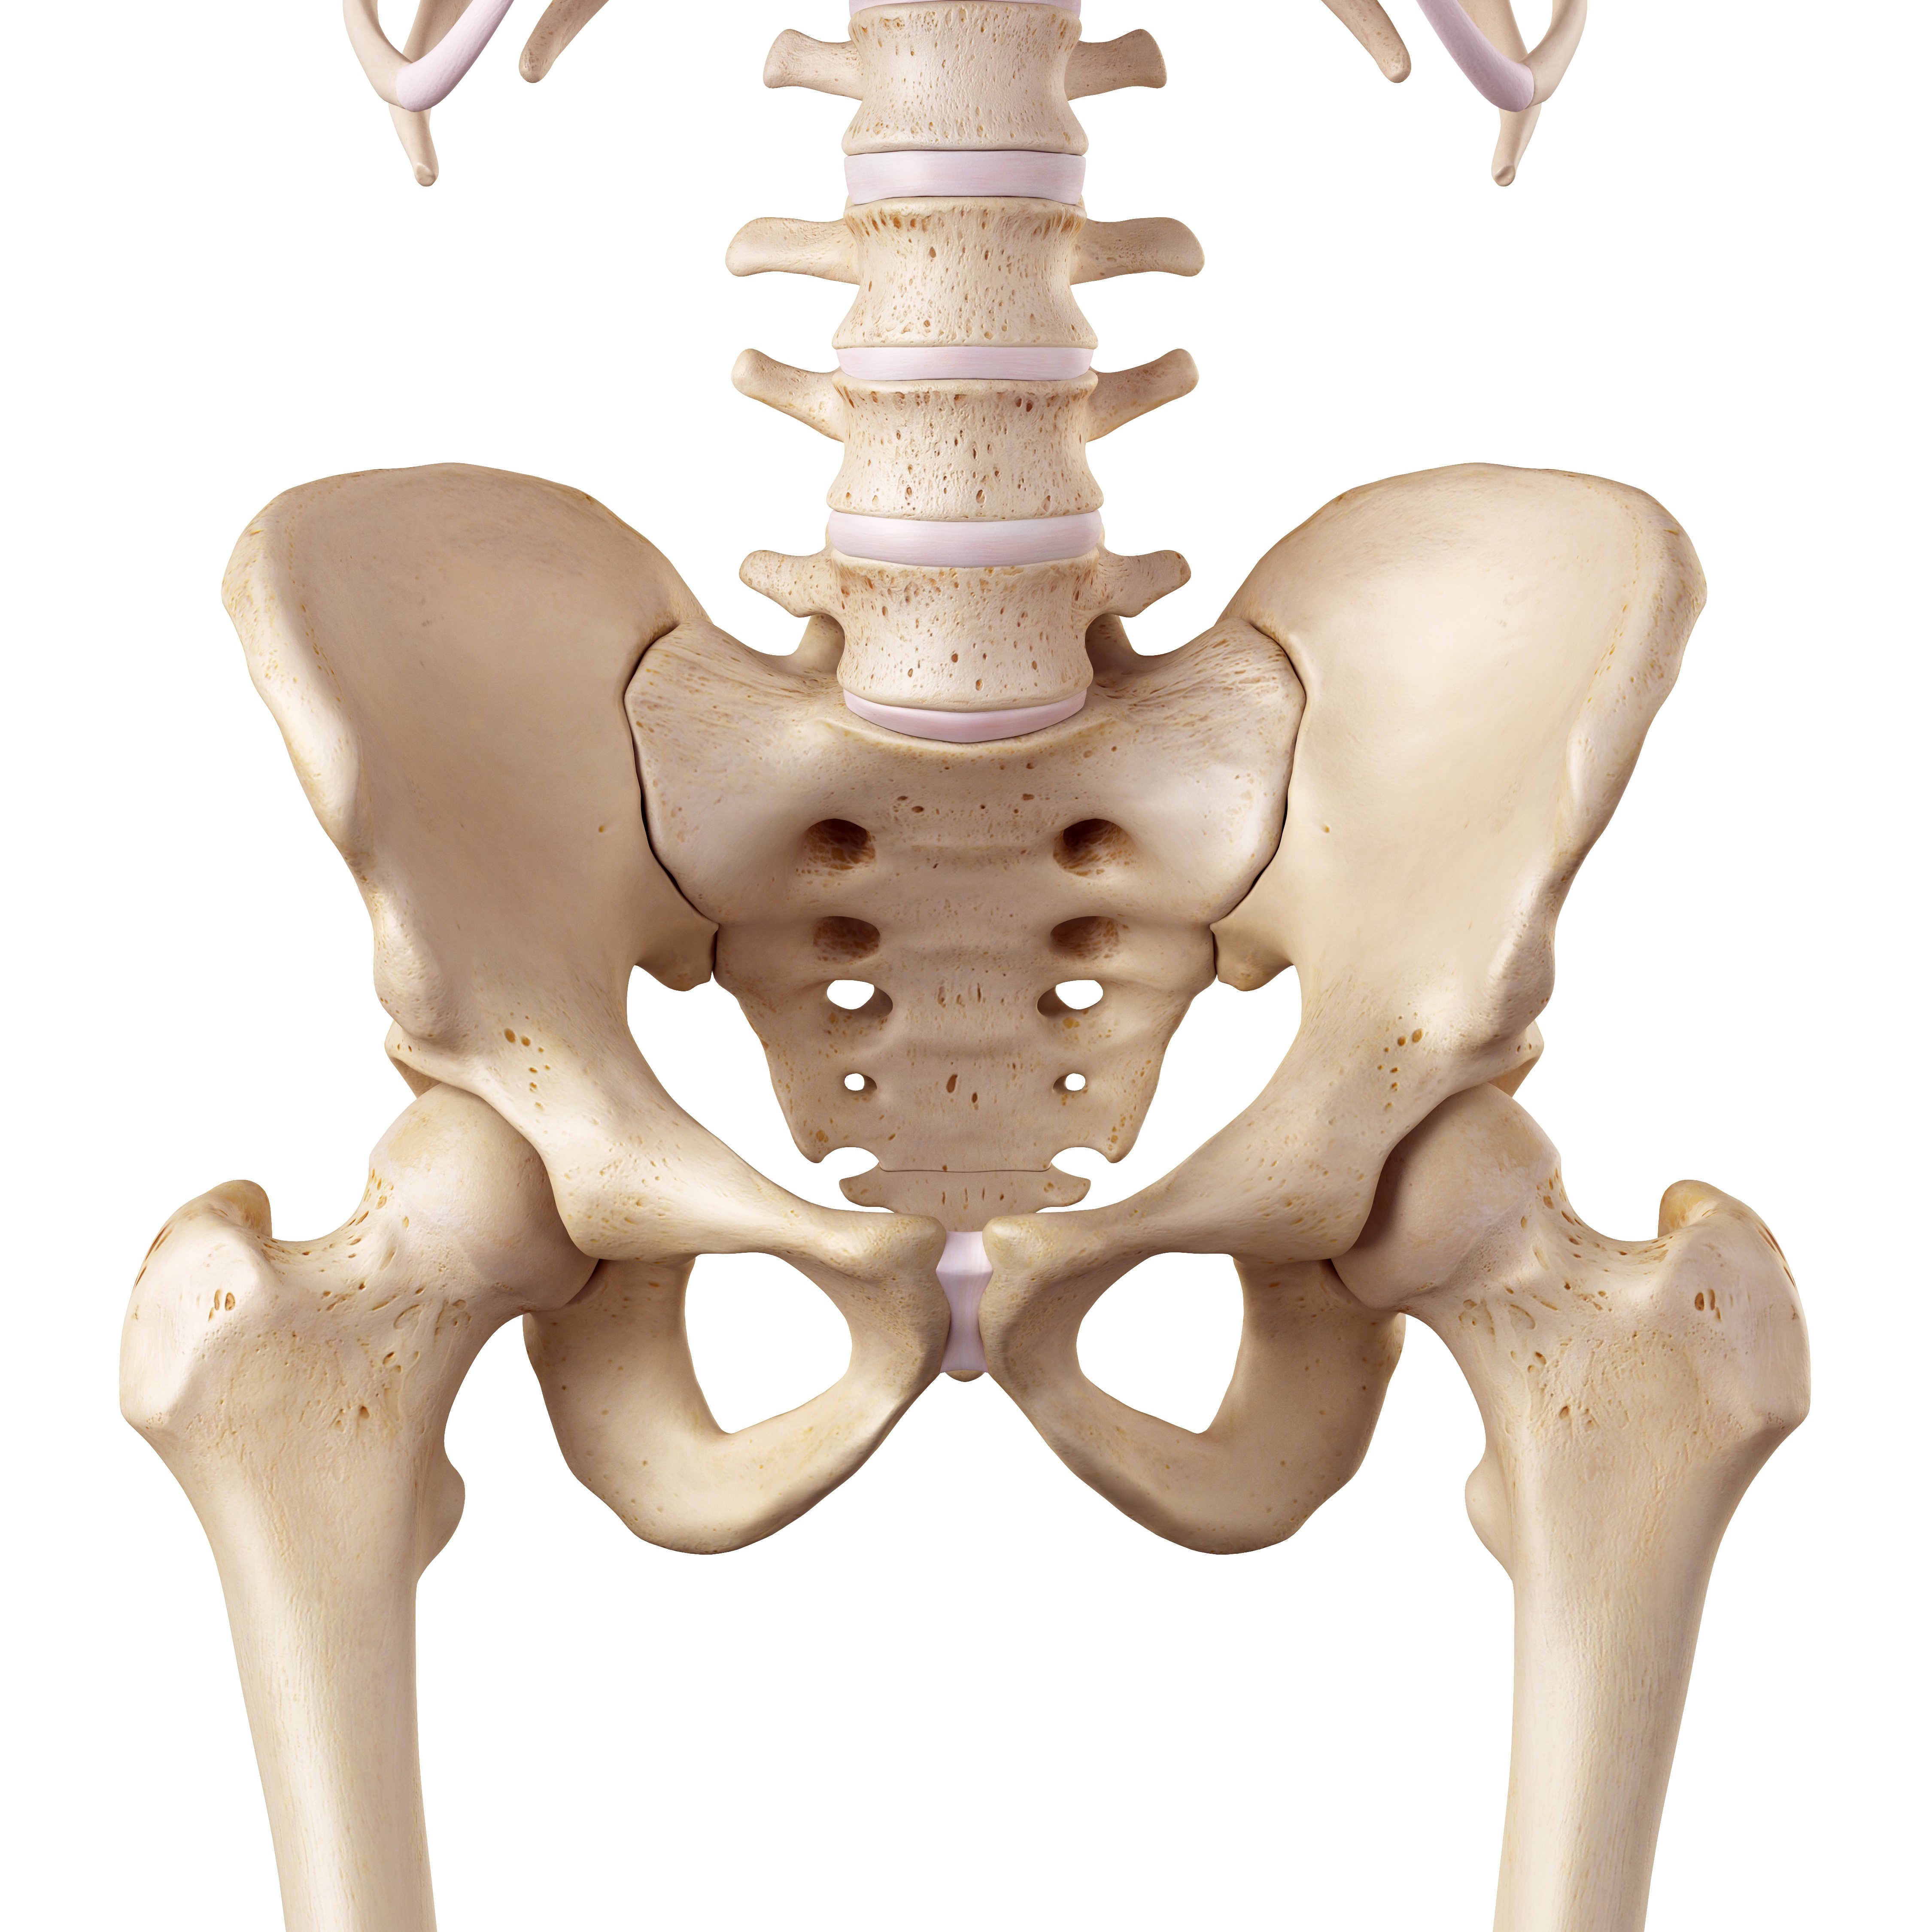
Hip dysplasia in dogs follows a progressive degenerative trajectory, beginning with subclinical joint laxity and advancing to severe osteoarthritis (OA) if untreated. The clinical manifestations vary widely based on breed predisposition, age, body weight, and activity level, necessitating early recognition to mitigate long-term joint damage. This section outlines the staged progression of hip dysplasia, from asymptomatic early signs to debilitating lameness, alongside diagnostic tools for veterinarians and monitoring guidelines for owners.Staged Progression of Clinical Signs
The degeneration of hip joints in dysplasia follows a predictable yet variable timeline, influenced by genetic, biomechanical, and environmental factors. Below is a structured breakdown of the three primary stages, each characterized by distinct physical and behavioral changes.Early-Stage (Subclinical to Mild Dysplasia)
During this phase, joint instability exists but may not yet manifest as overt lameness. Owners may observe subtle behavioral shifts, particularly in high-energy breeds or puppies predisposed to dysplasia. Key indicators include:
Example: A 6-month-old Golden Retriever puppy may exhibit a slight "bunny-hop" when excited but appears otherwise normal during routine activities.
Middle-Stage (Moderate Dysplasia with Secondary Changes)
Joint degeneration accelerates, leading to muscle atrophy, compensatory limb use, and intermittent lameness. Pain becomes more pronounced, and radiographic changes (e.g., joint space narrowing) are often detectable. Symptoms include:
Case Study: A 2-year-old Bernese Mountain Dog may show noticeable muscle loss in the hindquarters and resist leash walks, preferring short, frequent breaks.
Advanced-Stage (Severe Osteoarthritis and Functional Limitation)
At this stage, irreversible joint damage results in chronic pain, non-weight-bearing lameness, and systemic effects (e.g., reduced mobility, obesity). Clinical signs are severe and include:
Example: A 7-year-old Rottweiler may refuse to rise from a lying position and exhibit vocalization when touched near the hips.
Symptom-to-Severity Flowchart for Owner Monitoring
Owners play a critical role in early intervention by tracking subtle changes in their dog’s mobility. Below is a visual mapping of clinical observations to likely stages of hip dysplasia, designed for owner self-assessment.Flowchart: Clinical Signs vs. Likely Dysplasia Stage
-
Subclinical/Mild:
- Occasional bunny-hopping during play.
- Reluctance to jump but no visible lameness.
- Mild stiffness after rest (resolves quickly).
Action: Schedule a veterinary exam for hip extension/flexion tests and early intervention (e.g., weight management, joint supplements).
-
Moderate:
- Visible muscle atrophy in hindquarters.
- Stiffness lasting >30 minutes after rest.
- Asymmetrical gait or reluctance to walk on leash.
Action: Request radiographic imaging (e.g., PennHIP or OFA) and consider physical therapy or NSAIDs under veterinary guidance.
-
Severe:
- Non-weight-bearing lameness or refusal to move.
- Pain response to hip palpation or vocalization.
- Joint effusion or "hard" hip upon examination.
Action: Immediate veterinary consultation for pain management (e.g., joint injections, surgical options like THR or TPO).
Influencing Factors: Age, Weight, and Activity Level
The onset and progression of hip dysplasia are significantly modulated by three primary factors: age, body weight, and activity level. Understanding these variables allows for targeted preventive and therapeutic strategies.Age-Related Progression
Weight Impact
Obesity accelerates joint degeneration by increasing mechanical stress on the hip. For example:
Activity Level
Case Comparison:
Veterinary Assessment Checklist for Hip Dysplasia
A systematic physical examination is essential for diagnosing hip dysplasia and staging its severity. Below is a checklist for veterinarians, incorporating orthopedic tests and palpation techniques to assess joint integrity.Hip Dysplasia Physical Exam Checklist
- Hip Extension/Flexion Test:
- Position the dog in lateral recumbency and extend the hind limb to assess range of motion.
- Note resistance or pain, which may indicate joint capsule tightening or OA.
- Ortolani Sign Demonstration:
- Flex the hip and apply lateral pressure to the stifle while extending the limb. A "clunk" or palpable reduction indicates hip laxity.
- Positive in ~20% of dysplastic dogs; may require sedation for accurate assessment.
- Palpation for Crepitus and Effusion:
- Examine the hip joint for warmth, swelling, or crepitus (grinding sensation) during passive movement.
- Compare bilaterally; asymmetry suggests unilateral dysplasia.
- Muscle Atrophy Assessment:
- Evaluate quadriceps and gluteal muscle groups for atrophy, indicating disuse or pain.
- Use a muscle scoring system (e.g., 0–5 scale) for documentation.
- Gait Analysis:
- Observe
Advanced Diagnostic Methods and Early Detection Strategies in Canine Hip Dysplasia
Canine hip dysplasia (CHD) remains a complex orthopedic condition requiring precise diagnostic tools to differentiate early-stage pathology from progressive joint degeneration. While radiography remains the gold standard for structural assessment, advanced imaging modalities and emerging biomarkers enhance diagnostic accuracy, particularly in subclinical cases or when soft tissue involvement is suspected. This section explores the role of computed tomography (CT), magnetic resonance imaging (MRI), and ultrasound in refining CHD diagnostics, alongside specialized evaluations such as the PennHIP method and blood biomarkers. Additionally, breed-specific protocols and age-based screening strategies are examined to optimize early intervention.
Advanced Imaging Techniques in Hip Dysplasia Diagnosis
Advanced imaging provides complementary insights to conventional radiography, addressing limitations in soft tissue evaluation, joint congruity assessment, and early cartilage degradation. Each modality offers distinct advantages depending on the clinical presentation and stage of dysplasia.Computed Tomography (CT) Scans
CT scans deliver high-resolution images of bone structures, enabling detailed evaluation of femoral head-neck junction abnormalities, acetabular dysplasia, and secondary osteoarthritis changes. Unlike radiographs, CT allows multiplanar reconstructions, which improve visualization of subluxation patterns, coxa valga/varus deformities, and osteophyte formation. The procedure involves:
- Patient positioning: Lateral recumbency with the pelvis centered under the gantry, ensuring symmetrical limb extension to avoid rotation artifacts.
- Slice thickness: Typically 0.6–1.2 mm for high-resolution bone assessment, with 3D reconstructions generated for volumetric analysis.
- Key findings: Identification of subchondral bone sclerosis, joint space narrowing, and femoral head flattening correlates with PennHip distraction indices >0.7.
Magnetic Resonance Imaging (MRI)
MRI excels in detecting labral tears, synovitis, and cartilage defects, which are often undetectable via radiography or CT. T1-weighted and T2-weighted sequences with fat suppression highlight:
- Labral pathology: High-signal intensity on T2-weighted images indicates labral detachment or fraying, common in dysplastic hips.
- Cartilage integrity: Delayed gadolinium-enhanced MRI (dGEMRIC) quantifies glycosaminoglycan content, with lower T1 values correlating with early cartilage degradation.
- Soft tissue inflammation: Synovial fluid hyperintensity on T2-FS images suggests synovitis or joint effusion, often preceding radiographic changes.
Ultrasound
Ultrasound assesses synovial fluid dynamics, joint capsule integrity, and early synovial hypertrophy. High-frequency linear probes (12–18 MHz) evaluate:
- Effusion quantification: Anechoic fluid collections (>3 mm) suggest inflammatory responses.
- Labral morphology: Hypoechoic regions within the labrum may indicate tears, though operator dependence limits reliability.
- Dynamic assessment: Real-time evaluation of joint laxity during passive hip extension can complement static imaging.
PennHIP Evaluation Procedure and Joint Laxity Analysis
The PennHIP (Penn Hip Improvement Program) evaluation quantifies hip joint laxity using a distraction index (DI), which predicts dysplasia progression more accurately than traditional radiographic scoring (e.g., OFA). The procedure follows a standardized protocol to ensure reproducibility.Procedure Outline
1. Patient Preparation and Positioning
- Sedation/Anesthesia: Required for patient compliance; avoid neuromuscular blockade to prevent joint laxity underestimation.
- Positioning: Dorsal recumbency with the pelvis centered under the X-ray source. Femurs aligned parallel to the table, ensuring no rotation (verified via symmetric femoral condyles on AP view).
- Equipment: Specialized PennHIP positioning device secures the pelvis in neutral position while allowing controlled femoral distraction.
2. Distraction Index Measurement Steps
- Compression View (CV): Standard ventrodorsal radiograph with hips extended and pelvis neutral. Measures normal joint congruity.
- Distraction View (DV): Femurs externally rotated and distracted caudally using a customized harness or device, creating a distraction force of 16 lbs (7.26 kg) for large breeds (>20 kg) and 8 lbs (3.63 kg) for small breeds (<20 kg).
- Measurement Parameters:
- Femoral Head Coverage (FHC): Percentage of the femoral head covered by the acetabulum in the CV.
- Distraction Index (DI): Ratio of femoral head coverage in DV to CV, expressed as DI = (FHC_DV / FHC_CV) × 100. A DI >0.7 indicates abnormal laxity with high dysplasia risk.
3. Software Analysis of Joint Laxity
- Digital Calipers: Used to measure femoral head and acetabular margins on both CV and DV images.
- Automated Tools: PennHIP software calculates DI and generates risk stratification (low: DI <0.4; moderate: 0.4–0.6; high: >0.7).
- Longitudinal Tracking: Serial evaluations (e.g., at 4, 8, and 16 weeks) monitor DI progression, with DI >0.3 at 16 weeks strongly predictive of clinical signs by 2 years.
Clinical Relevance
- Early Puppy Screening: DI >0.3 at 16 weeks identifies 80% of dysplastic hips before radiographic changes appear (Ortolani et al., 2018).
- Breeding Decisions: DI thresholds vary by breed; e.g., German Shepherds may use DI <0.4 as a cutoff, while Labrador Retrievers often employ stricter criteria (DI <0.3).
Comparison of Blood Biomarkers and Traditional Imaging in Early Detection
Blood biomarkers offer non-invasive, early detection of cartilage and bone turnover, complementing imaging in subclinical CHD. Key biomarkers include:
- Cartilage Oligomeric Matrix Protein (COMP): Elevated levels correlate with cartilage degradation and joint instability. Studies show COMP >10 U/L in dysplastic puppies vs. <5 U/L in healthy controls (Ekenstedt et al., 2005).
- C-Telopeptide (CTX): A collagen breakdown product; elevated CTX in serum/urine indicates osteoclastic activity associated with subchondral bone resorption.
- Hyaluronic Acid (HA): Reflects synovial inflammation; elevated HA (>100 ng/mL) precedes radiographic changes by 6–12 months (Martinez et al., 2010).
Accuracy Comparison
Clinical Integration
Method Early Detection Window Strengths Limitations Radiography (OFA) 2+ years (clinical signs) Standardized, cost-effective Poor sensitivity for subclinical cases PennHIP (DI) 4–16 weeks (puppies) Predictive of future dysplasia Requires anesthesia, equipment-dependent MRI (dGEMRIC) 6–12 months (cartilage) Detects soft tissue/labral damage Expensive, not widely available COMP/CTX Biomarkers 4–8 weeks (biochemical) Non-invasive, early changes False positives in non-dysplastic breeds
- Combination Approach: PennHIP DI + COMP levels at 16 weeks improve sensitivity to 92% for predicting CHD by 2 years (Smith et al., 2012).
- Limitations: Biomarkers lack specificity for CHD (e.g., COMP also elevated in osteoarthritis). Breed-specific reference ranges are critical (e.g., Bernese Mountain Dogs have higher baseline COMP than Greyhounds).
Breed-Specific and Age-Based Diagnostic Protocols
Diagnostic strategies vary by breed size and patient age, reflecting differences in disease progression, genetic predisposition, and clinical presentation.Large Breed Protocols (e.g., German Shepherd, Labrador Retriever, Golden Retriever)
- Puppies (<2 years):
- Primary Tool: PennHIP DI at 16 weeks (cutoff: DI <0.3 for breeding clearance).
- Secondary Screening: COMP levels at 8 and 16 weeks; DI >0.4 warrants MRI for labral evaluation.
- Radiographic Follow-Up: OFA radiographs at 2 years if DI is borderline (0.3–0.5).
- Adults (>2 years):
- Gold Standard: OFA radiographs with Norberg angle (>105° = normal).
- Advanced Imaging: CT for osteophyte quantification; MRI if lameness persists
Treatment and Management Strategies for Canine Hip Dysplasia
Canine hip dysplasia (CHD) management requires a multimodal approach, tailored to disease severity, breed-specific risks, and individual patient needs. Conservative therapies focus on symptom alleviation and joint preservation, while surgical interventions address structural defects. Emerging regenerative techniques offer promising alternatives for early-stage or non-surgical candidates. Rehabilitation protocols are critical for post-operative success, emphasizing controlled recovery to restore function without exacerbating joint instability. Preventive strategies, particularly in breeding programs, rely on genetic screening, nutritional optimization, and controlled exercise to mitigate hereditary risks.
Tiered Treatment Table by Disease Severity
The selection of therapeutic interventions depends on clinical staging (e.g., OFA grading, PennHIP measurements) and the dog’s age, activity level, and breed predisposition. Below is a structured breakdown of treatment options categorized by severity, from mild to severe, including conservative, surgical, and emerging therapies.
Note: Treatment efficacy varies by breed, age, and compliance. Combination therapies (e.g., post-surgical rehabilitation + stem cells) often yield superior outcomes. Veterinary consultation is mandatory to avoid complications (e.g., NSAID toxicity, improper TPO timing).
Severity Level Conservative Management Surgical Interventions Emerging Therapies Mild (Early-Stage, Minimal Clinical Signs)
- Weight management (ideal body condition score 4–5/9).
- Joint supplements (glucosamine, chondroitin, green-lipped mussel, or MSM).
- Low-impact exercise (swimming, controlled leash walks).
- Physical therapy (laser therapy, massage, hydrotherapy).
Not typically required; reserved for progressive cases.
- Platelet-rich plasma (PRP) injections for anti-inflammatory effects.
- Stem cell therapy (autologous or allogenic) to promote cartilage repair.
Moderate (Visible Lameness, Joint Effusion)
- Strict weight control and anti-inflammatory diet (e.g., omega-3 fatty acids, hydrolyzed proteins).
- Pharmacological support (NSAIDs like carprofen or meloxicam under veterinary supervision).
- Orthopedic aids (joint braces, hip supports for large breeds).
- Triple pelvic osteotomy (TPO) in young dogs (<10 months) to realign the hip joint.
- Juvenile pubic symphysiodesis (JPS) for growing puppies to slow dysplasia progression.
- Combination PRP + stem cell therapy for enhanced cartilage regeneration.
- Exosome therapy (derived from mesenchymal stem cells) for targeted repair.
Severe (Advanced Arthritis, Non-Ambulatory)
- Pain management (opioids, gabapentin, or tramadol for refractory cases).
- Assistive devices (wheelchairs, slings for mobility).
- Total hip replacement (THR) for large breeds with severe joint degeneration.
- Femoral head ostectomy (FHO) for small-to-medium breeds or as a salvage procedure.
- Bioengineered cartilage implants (experimental, e.g., MACI® in veterinary trials).
- Gene therapy (e.g., overexpression of SOX9 for chondrogenesis) in research phases.
Step-by-Step Post-Surgical Rehabilitation Protocol
Surgical intervention for CHD—whether THR, FHO, or TPO—requires a structured rehabilitation program to optimize recovery, prevent complications (e.g., heterotopic ossification, muscle atrophy), and restore function. The protocol is divided into phases, each with specific goals and restrictions.Phase 1: Immediate Post-Operative (Weeks 1–4)
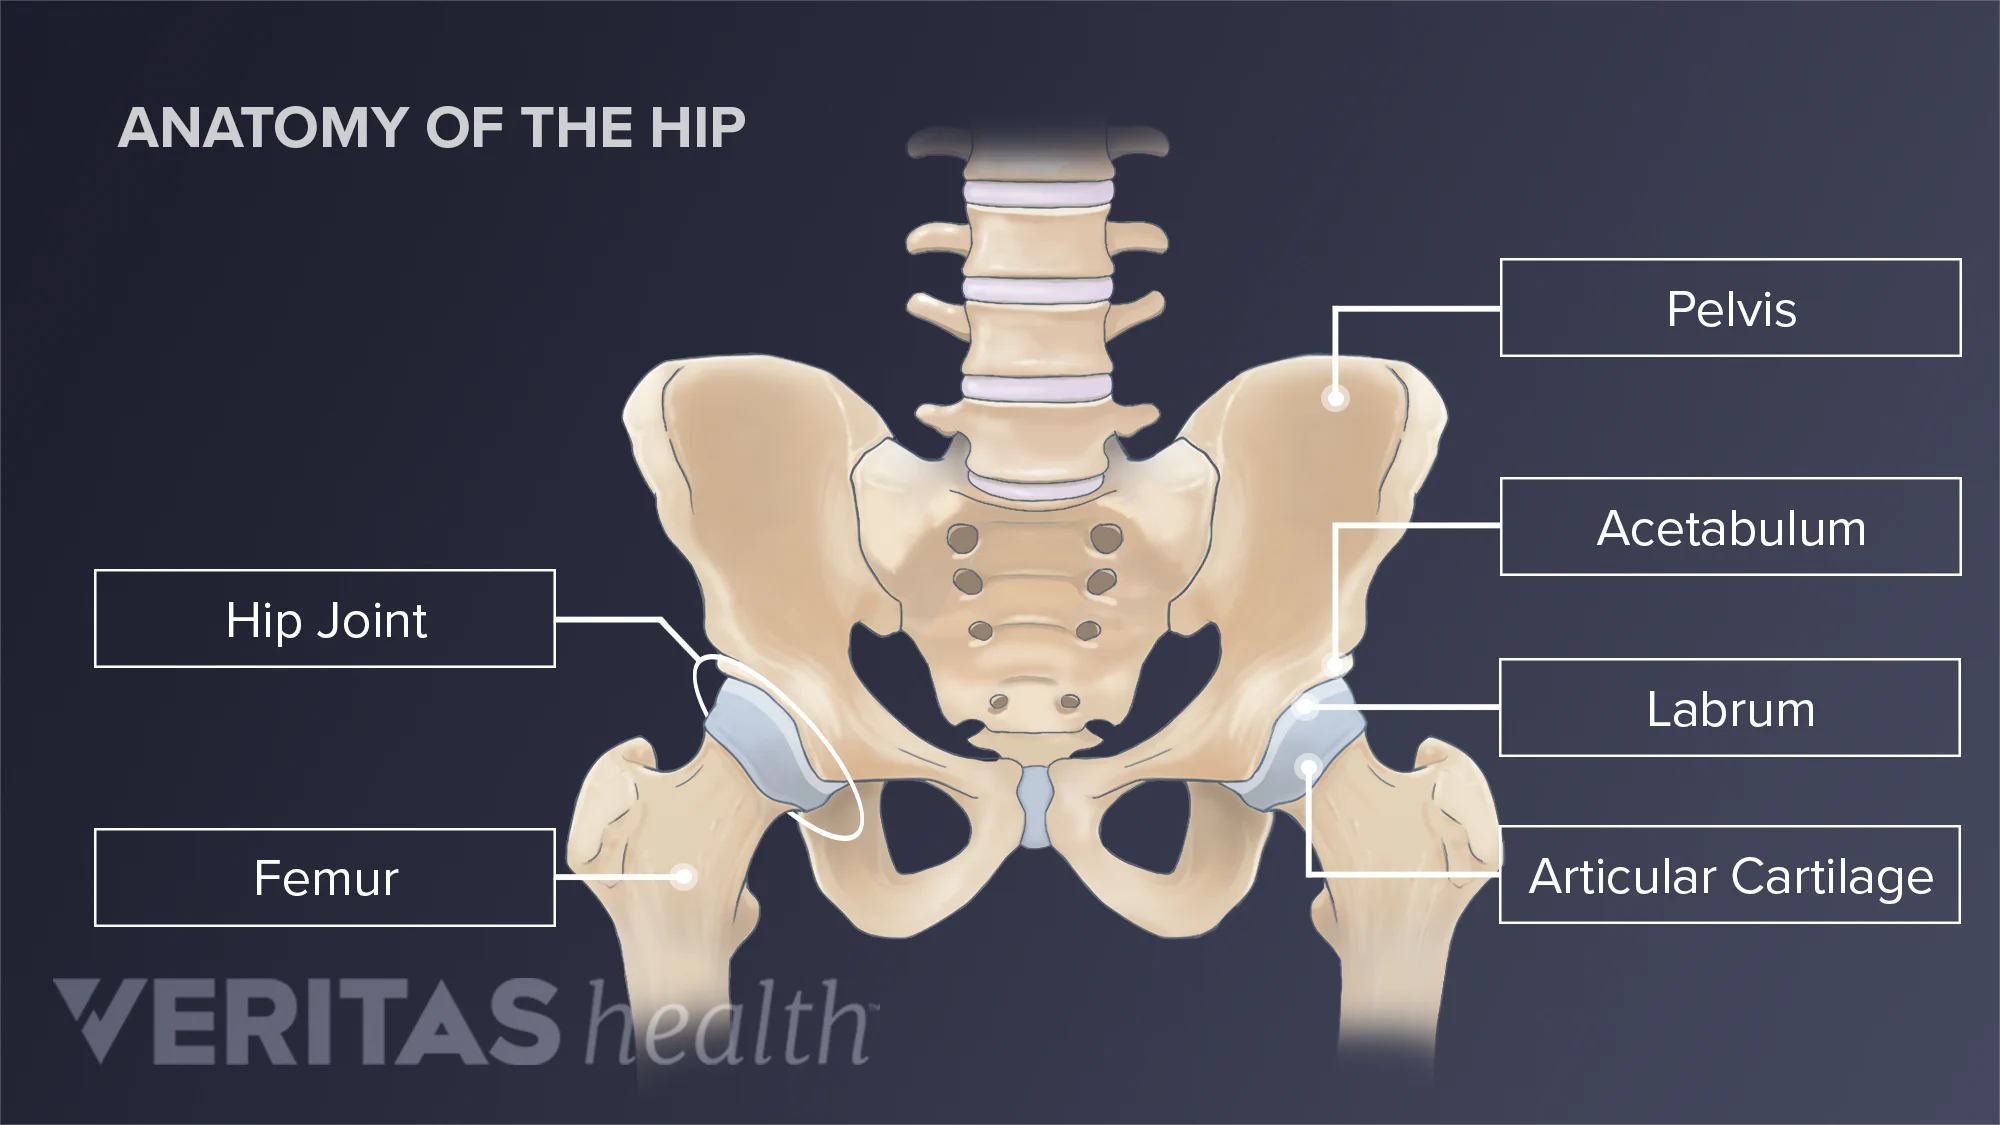
The primary focus is controlled rest to allow tissue healing while minimizing joint stress. Key components include:
- Restriction Periods:
Crate confinement: 24/7 for 4–6 weeks post-TPO/THR; 8–12 weeks post-FHO in large breeds.
- Leash limits: Short, frequent walks (5–10 minutes) on non-slip surfaces; avoid stairs or jumping.
- Avoidance of: Slippery floors, prolonged sitting/lying on hard surfaces, and forced exercise.
- NSAIDs (e.g., meloxicam) tapered over 2–4 weeks under veterinary guidance.
Gradual controlled movement is introduced to prevent muscle atrophy and improve range of motion (ROM). Critical interventions include:
- Underwater treadmill therapy: Low-impact hydrostatic pressure reduces joint load while promoting gait symmetry. Start with 5–10 minutes, 2–3x/week, increasing duration as tolerated.
- Calcium:phosphorus ratio of 1.2:1 to 1.5:1 for growing dogs.
- Green-lipped mussel or turmeric supplements for joint support.
- Avoid excess calcium (e.g., over-supplementation in puppies).
The goal shifts to restoring function and endurance through progressive loading and strength training. Techniques include:
- Land treadmill work: Begin at 1.5–2 mph, 10–15 minutes, 3x/week, gradually increasing incline (max 5%).
- Regular veterinary check-ups (every 4–6 weeks) to assess ROM, muscle symmetry, and pain levels.
Hip dysplasia in dogs underscores the interplay between genetics, biomechanics, and environmental influences in shaping musculoskeletal health. Early recognition through systematic diagnostic methods—such as the OFA or PennHIP evaluations—enables timely intervention, mitigating progression and improving long-term outcomes. While surgical options like total hip replacement offer definitive relief for advanced cases, preventive strategies for breeders and owners remain pivotal, emphasizing genetic screening, balanced nutrition, and controlled exercise to reduce risk. By adopting a proactive approach—combining clinical vigilance, evidence-based therapies, and breed-specific care—stakeholders can significantly enhance the welfare of affected dogs, ensuring mobility and comfort throughout their lives.
FAQ
what is hip dysplasia in dogs symptoms?
Q: What are the symptoms of hip dysplasia in dogs?
what is hip dysplasia in dogs treatment?
Q: What are the treatment options for hip dysplasia in dogs?
what is hip dysplasia in dogs uk?
Q: How common is hip dysplasia in dogs in the UK, and what resources are available?
what is hip dysplasia in dogs look like?
Q: What does hip dysplasia look like in a dog physically?
what is hip dysplasia in dogs causes?
Q: What causes hip dysplasia in dogs?
what is bilateral hip dysplasia in dogs?
Q: What is bilateral hip dysplasia in dogs, and how is it different?
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.