<
Medical Procedures and Surgical Techniques in Sinus Lift Surgery
Sinus lift procedures are critical in dental implantology for restoring vertical bone height in the posterior maxilla, where anatomical limitations often preclude direct implant placement. The selection of surgical technique depends on factors such as bone quality, sinus membrane integrity, and patient-specific anatomy. Two primary approaches—the lateral window approach and the osteotome sinus lift—differ in invasiveness, precision, and clinical applications. This section details their procedural mechanics, indications, limitations, and the decision-making framework guiding their selection.
Types of Sinus Lift Procedures
Sinus lift techniques are categorized based on surgical access and bone augmentation strategy. The lateral window approach is the gold standard for extensive bone deficiencies, while the osteotome sinus lift (or closed sinus lift) is reserved for minimal vertical bone loss. Each method involves distinct anatomical considerations, graft materials, and recovery protocols.
Lateral Window Approach
The lateral window technique is an open sinus lift procedure characterized by direct visualization of the sinus membrane and precise graft placement. It is indicated for patients with ≥5 mm of vertical bone loss or compromised sinus membrane integrity (e.g., perforations, scarring from prior infections). The procedure involves:
Surgical access: A crestal incision followed by a full-thickness flap elevation to expose the lateral maxillary wall.
Osteotomy: Creation of a rectangular window (typically 15–20 mm) in the lateral bone using a piezoelectric or rotary instrument.
Membrane elevation: Gentle separation of the Schneiderian membrane from the bony floor using blunt dissection instruments (e.g., sinus elevators, ball burnishers).
Graft placement: Introduction of bone graft material (autogenous, allograft, xenograft, or synthetic) into the created space.
Fixation and closure: Membrane stabilization (e.g., resorbable membranes, fixation screws) and flap suturing.Limitations:
Higher risk of membrane perforation (reported in 5–15% of cases) due to direct manipulation.
Longer healing time (3–9 months) before implant placement, influenced by graft integration.
Potential for postoperative complications, including sinusitis or graft displacement.
Osteotome Sinus Lift
The osteotome technique is a minimally invasive, closed sinus lift designed for cases with ≤5 mm of bone loss and intact sinus membranes. It leverages sequential osteotome taps to fracture the maxillary floor and elevate the sinus membrane indirectly. Key steps include:
Crestal incision and flap reflection: Limited exposure to minimize soft tissue trauma.
Osteotomy: Sequential tapping with progressively larger osteotomes (1.0–3.0 mm increments) to create a fracture line in the maxillary floor.
Graft condensation: Introduction of bone graft material through the osteotomy site using condensers or injectable graft matrices.
Implant placement: Immediate or staged implant insertion into the augmented site, contingent on primary stability.Limitations:
Technique sensitivity: Requires precise control to avoid membrane perforation or incomplete elevation.
Limited graft volume: Maximum vertical gain typically ≤8 mm, restricting its use in severe atrophy.
Higher failure rates in cases with pre-existing sinus pathology (e.g., polyps, mucosal thickening).
Decision-Making Flowchart for Sinus Lift Technique Selection
The choice between lateral window and osteotome techniques is guided by preoperative imaging, bone quality, and patient anatomy. Below is a structured flowchart to facilitate clinical decision-making:
-
Assess vertical bone height (CBCT measurement):
- ≥5 mm bone loss → Lateral window approach (direct visualization, higher graft volume).
- <5 mm bone loss → Proceed to osteotome evaluation.
-
Evaluate sinus membrane integrity (CBCT/surgical exploration):
- Perforations, scarring, or mucosal thickening → Lateral window approach (controlled repair possible).
- Intact membrane → Proceed to osteotome feasibility.
-
Assess bone quality (D1–D4 classification):
- Poor quality (D3–D4) → Lateral window approach (better graft containment).
- Moderate quality (D1–D2) → Osteotome sinus lift (if <5 mm deficiency).
-
Patient-specific factors:
- Medical comorbidities (e.g., uncontrolled diabetes, osteoporosis) → Lateral window (longer healing tolerance).
- High patient anxiety or limited compliance → Osteotome (shorter procedure time).
-
Final technique selection:
- Lateral window: Preferred for complex cases, high graft volume needs, or membrane compromise.
- Osteotome: Suitable for minimal deficiencies, intact membranes, and immediate implant placement.
Instruments and Materials for Sinus Lift Surgery
Sinus lift procedures require specialized instruments to ensure membrane integrity, graft stability, and implant primary stability. The selection of materials is critical for graft success and complication avoidance.
Surgical Instruments
Essential instruments for both techniques include:
Osteotomy tools:- Rotary burs (round or fissure) for lateral window creation.
Piezoelectric or ultrasonic tips for atraumatic bone removal.
Osteotomes (sequential sizes, 1.0–3.0 mm) for closed sinus lifts.
Membrane elevation aids:- Sinus elevators (e.g., Summers, Balloon Sinus Lift kits).
Blunt dissectors (e.g., Freer elevators, sinus curettes).
Ball burnishers for membrane stabilization.
Graft condensation devices:- Condensers (manual or hydraulic) for osteotome lifts.
Injectable graft delivery systems (e.g., syringes with cannulas).
Fixation and closure:- Resorbable membranes (e.g., collagen, bioabsorbable barriers).
Fixation screws or tacks for membrane stabilization.
Suturing materials (e.g., PTFE, vicryl).
Bone Graft Materials
Graft selection depends on osteoconductivity, osteoinductivity, and patient-specific needs. Common options include:
Autogenous grafts (gold standard):- Intraoral (e.g., ramus, symphysis) or extraoral (e.g., iliac crest).
Advantages: High success rates, no immune response.
Limitations: Donor-site morbidity, limited volume.
Allografts (processed human bone):- Demineralized freeze-dried bone (DFDB), freeze-dried bone allograft (FDBA).
Advantages: Osteoconductive, no disease transmission risk (if properly processed).
Limitations: Slower integration, potential immune response.
Xenografts (bovine/animal-derived):- Deproteinized bovine bone mineral (DBBM), hydroxyapatite.
Advantages: Abundant supply, predictable resorption.
Limitations: Lack of osteoinductivity, potential for particle extrusion.
Synthetic grafts:- Calcium sulfate, tricalcium phosphate (TCP), bioactive glass.
Advantages: Standardized composition, no immunogenicity.
Limitations: Variable integration, limited long-term data.
Combination grafts:- Mixed autogenous
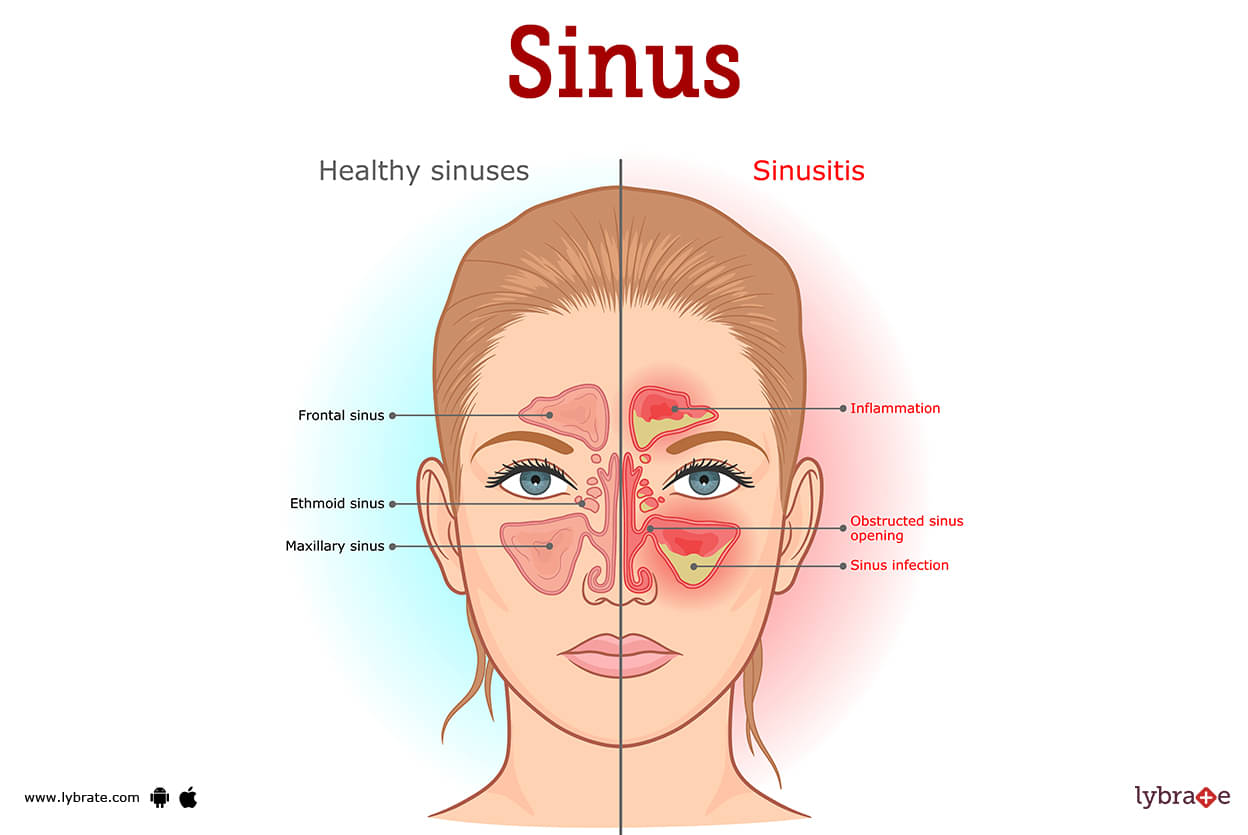
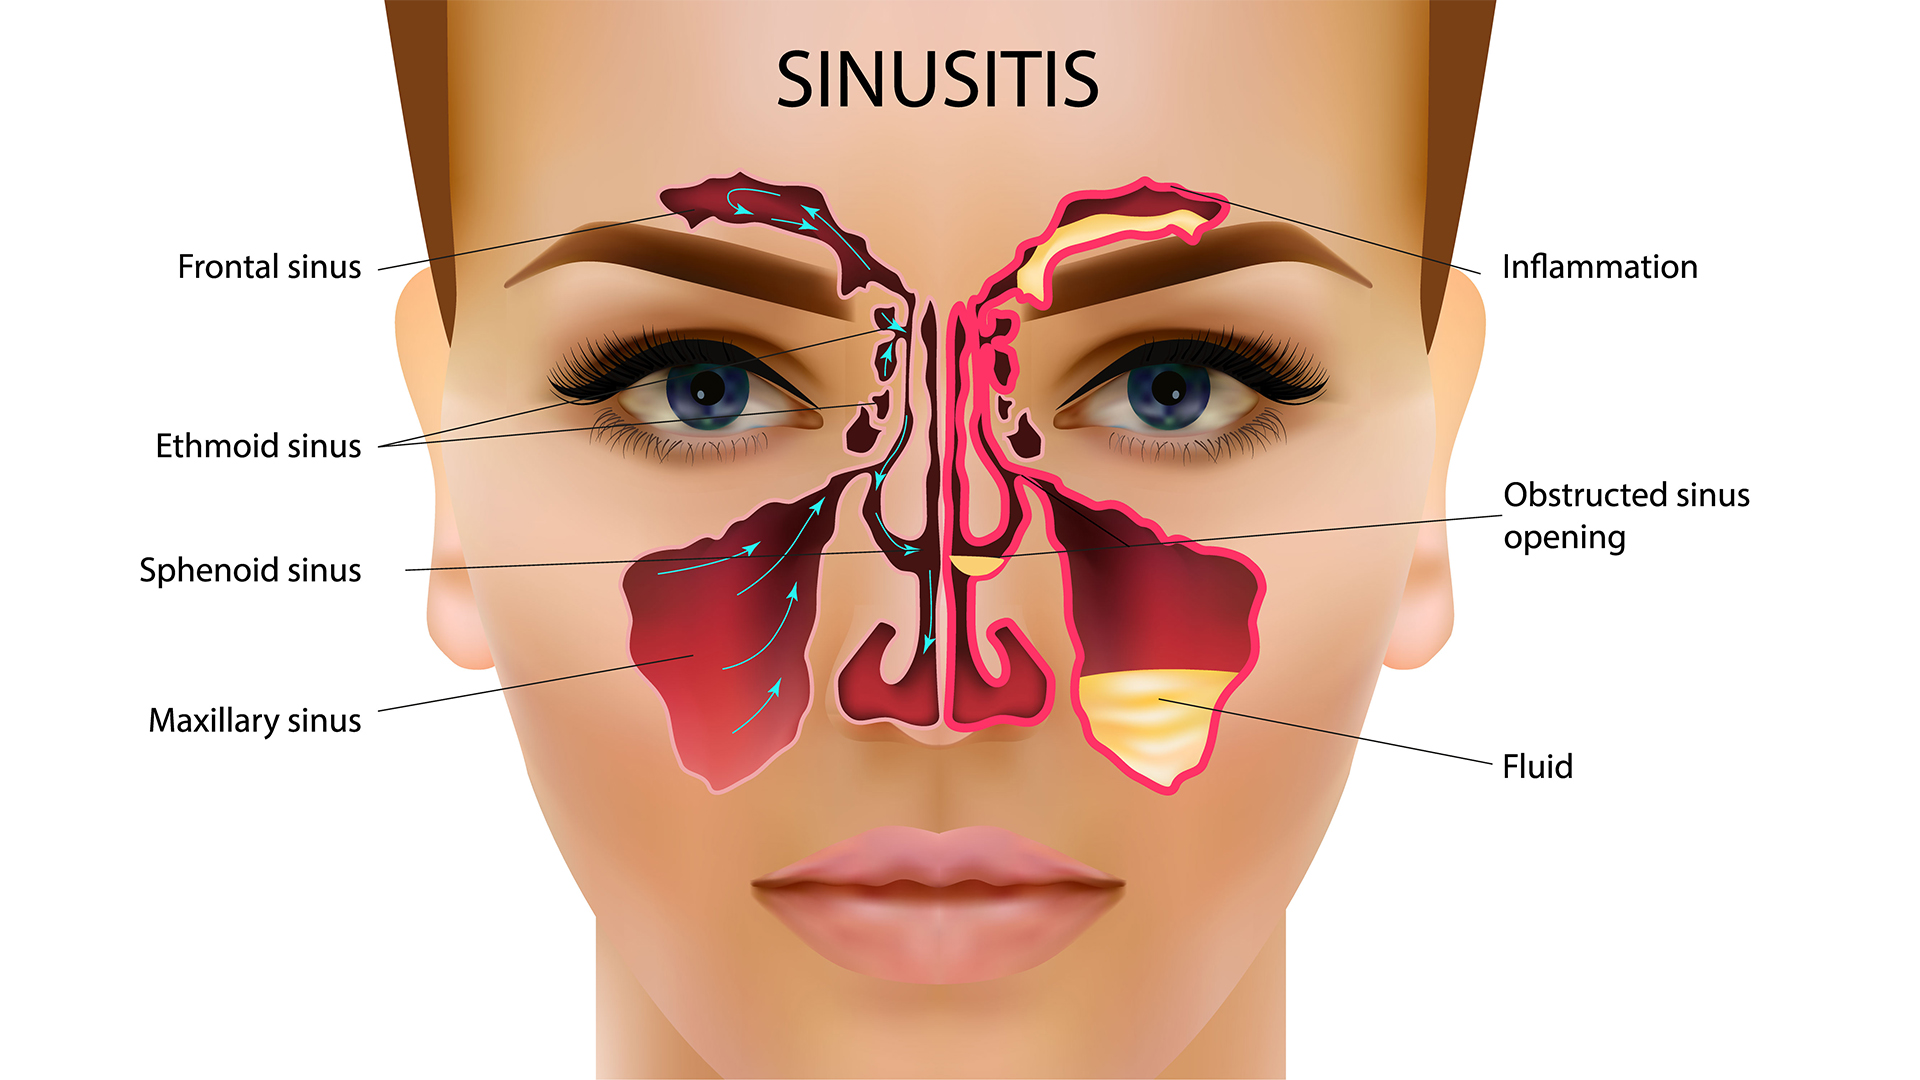
Bone Graft Materials and Integration in Sinus Lift Procedures
The selection of bone graft materials and their integration mechanisms are critical determinants of sinus lift success, influencing long-term implant stability and patient outcomes. Bone regeneration in sinus augmentation relies on three primary biological processes—osteoconduction, osteoinduction, and osseointegration—each modulated by graft properties, surgical technique, and patient physiology. The choice between autogenous, allograft, xenograft, and synthetic grafts involves trade-offs between biocompatibility, resorption rates, and clinical performance. Equally important is the role of barrier membranes in maintaining graft volume and protecting the surgical site from premature epithelial ingrowth, with resorbable and non-resorbable options offering distinct advantages and risks.
Comparison of Bone Graft Materials in Sinus Lift Surgery
Bone graft materials used in sinus lifts vary in origin, composition, and clinical behavior, each presenting unique advantages and limitations. Autogenous bone (harvested from the patient’s own body, typically the iliac crest or mandibular ramus) remains the gold standard due to its superior osteogenic potential and lack of immunogenicity. However, its use is limited by donor-site morbidity and graft availability. Allografts (processed human bone from cadaveric sources) and xenografts (derived from bovine or porcine sources) offer abundant supply and favorable handling properties but may carry risks of immune response or disease transmission. Synthetic grafts (e.g., hydroxyapatite, tricalcium phosphate) provide consistent composition and reduced immunogenicity but often lack osteoinductive properties, necessitating combination with growth factors or cells.The following table summarizes key characteristics of graft materials, including success rates, integration timelines, and patient recovery profiles, based on clinical evidence and systematic reviews:
| Graft Material |
Success Rate (Long-Term Implant Survival) |
Integration Time (Osseointegration Period) |
Patient Recovery and Complications |
|---|
| Autogenous Bone |
95–98% (highest reported in literature) |
4–6 months (rapid osteoinduction and vascularization) |
- Donor-site morbidity (pain, infection, nerve damage)
- Extended surgical time and cost
- Minimal risk of rejection or resorption beyond 1 year
|
| Allografts (e.g., demineralized freeze-dried bone) |
85–92% (comparable to xenografts; lower than autogenous) |
6–9 months (slower osteoinduction; relies on host osteoprogenitor cells) |
- Lower risk of disease transmission (processed under strict protocols)
- Potential for immune response in rare cases (e.g., HLA mismatch)
- Moderate resorption rates (30–50% volume loss in 12 months)
|
| Xenografts (e.g., bovine-derived hydroxyapatite) |
80–88% (variable; depends on membrane integration) |
6–12 months (osteoconductive; minimal osteoinductive properties) |
- High biocompatibility and ease of handling
- Risk of bovine-derived prion transmission (theoretical; no documented cases in sinus lifts)
- Resorption rates similar to allografts; may require supplemental grafting
|
| Synthetic Grafts (e.g., β-TCP, biphasic calcium phosphate) |
75–85% (lower in high-resorption sites; improves with growth factors) |
9–12 months (highly osteoconductive; resorption rate varies by material) |
- No immunogenic or infectious risks
- May require longer healing periods for full integration
- Higher failure rates in smokers or patients with poor healing
|
Note: Success rates are influenced by patient factors (e.g., smoking, diabetes, osteoporosis) and surgical variables (e.g., membrane stability, graft volume). Studies indicate that combination grafts (e.g., autogenous bone + xenograft) often achieve intermediate outcomes with reduced complications.
Biological Mechanisms of Bone Regeneration Post-Sinus Lift
Bone regeneration in sinus augmentation follows a sequence of cellular and molecular events governed by the graft’s biological properties. Osteoconduction refers to the graft’s ability to serve as a scaffold for new bone formation, facilitated by its porosity and surface chemistry. Osteoinduction involves the recruitment and differentiation of undifferentiated mesenchymal stem cells into osteoblasts, a process enhanced by growth factors (e.g., BMP-2, PDGF) and autogenous bone. Osseointegration describes the direct structural and functional connection between the graft and host bone, critical for implant stability.The timeline of bone healing post-sinus lift can be divided into:
1. Inflammatory Phase (Days 1–7): Clot formation, angiogenesis, and macrophage activity to clear debris.
2. Reparative Phase (Weeks 2–12): Osteoprogenitor cell migration, extracellular matrix deposition, and early bone matrix mineralization.
3. Remodeling Phase (Months 3–12+): Resorption of graft material and replacement with lamellar bone, influenced by mechanical loading (e.g., implant placement).
Key Biological Processes:
- Osteoconduction: Dependent on graft porosity and surface area (e.g., granular vs. block grafts).
- Osteoinduction: Requires growth factors or viable cells (autogenous bone > allografts > xenografts > synthetics).
- Osseointegration: Achieved through mechanical interlocking and biological bonding (critical for implant primary stability).
The integration rate varies by graft type: autogenous bone exhibits rapid vascularization and osteogenic activity, while synthetic grafts rely on slow osteoconductive remodeling. Clinical studies demonstrate that grafts with higher surface area (e.g., demineralized freeze-dried bone allografts) accelerate healing but may increase resorption if not stabilized by a membrane.
Impact of Membrane Selection on Graft Stability and Healing
Barrier membranes in sinus lift surgery serve to contain the graft within the augmented space, prevent epithelial downgrowth, and maintain space for bone formation. The choice between resorbable (e.g., collagen, PLGA) and non-resorbable (e.g., expanded PTFE, titanium) membranes influences graft stability, healing dynamics, and complication rates.Resorbable Membranes:
Advantages:
Eliminate need for secondary membrane removal surgery.
Gradual integration with host tissue, reducing inflammation.
Suitable for one-stage sinus lifts with simultaneous implant placement.
Disadvantages:
Limited mechanical strength; may collapse under high graft pressure.
Resorption timing can vary (e.g., collagen membranes resorb in 4–6 months), risking premature exposure.
Higher risk of membrane perforation (reported in 5–15% of cases).Non-Resorbable Membranes:
Advantages:
Superior mechanical stability, ideal for large defects or high-pressure grafts.
Long-term containment reduces graft resorption and epithelial invasion.
Disadvantages:
Requires a second surgical procedure for removal (typically 6–9 months post-op).
Potential for membrane-related complications (e.g., infection, exposure, or chronic inflammation).
Higher cost and patient discomfort associated with additional surgery.
Critical Considerations for Membrane Selection:
Graft Volume: Non-resorbable membranes are preferred for lifts exceeding 8–10 mm in height.
Patient Risk Factors: Resorbable membranes may be contraindicated in smokers or patients with poor healing.
Surgical Technique: One-stage implants favor resorbable membranes to avoid interference with osseointegration.
Clinical evidence suggests that composite membranes (e.g., collagen-coated PTFE) offer a compromise, combining resorbable properties with enhanced stability. However, their use requires careful patient selection to mitigate risks of exposure or infection.
Complications Associated with Graft Material Re
Patient Considerations and Recovery in Sinus Lift Procedures
The success of a sinus lift procedure depends not only on surgical precision but also on careful patient selection, thorough pre-operative preparation, and structured post-operative care. Medical contraindications, patient compliance with pre-surgical protocols, and adherence to recovery guidelines significantly influence outcomes, including bone integration, implant stability, and overall patient satisfaction. This section outlines critical factors in patient management, from contraindications and pre-operative instructions to post-operative protocols and a structured recovery timeline, ensuring optimal healing and minimizing complications.
Medical Contraindications and Risk Factors
Patient history and current health status determine eligibility for sinus lift surgery. Certain medical conditions and medications increase the risk of complications such as infection, poor wound healing, or graft failure. Key contraindications include:- Uncontrolled systemic diseases:
Chronic conditions such as poorly managed diabetes (HbA1c > 8.5%), uncontrolled hypertension, or active infections (e.g., sinusitis, periodontal disease) impair tissue regeneration and elevate infection risk. Patients with a history of keloid formation or connective tissue disorders (e.g., Ehlers-Danlos syndrome) may experience delayed healing or graft extrusion. - Medications affecting bone metabolism or healing:
Bisphosphonate use (e.g., alendronate, zoledronic acid) is a well-documented contraindication due to the risk of osteonecrosis of the jaw (ONJ), particularly in high-dose or intravenous formulations. Other medications, such as long-term corticosteroids, chemotherapy agents (e.g., doxorubicin), or immunosuppressants (e.g., tacrolimus), may compromise graft integration and increase infection susceptibility. - Smoking and substance use:
Smoking reduces blood flow to the graft site, leading to higher failure rates (studies report a 30–50% reduction in graft success in smokers). Alcohol and illicit drug use further impair immune response and wound healing. - Anatomical limitations:
Insufficient sinus floor height (<4–5 mm of residual bone) or severe maxillary atrophy may necessitate alternative procedures (e.g., zygomatic implants). Patients with a history of radiation therapy to the head/neck region face increased fibrosis and poor graft vascularization. - Psychological or compliance factors:
Patients with unrealistic expectations, poor oral hygiene habits, or inability to follow post-operative instructions are at higher risk for complications. A thorough psychological assessment may be warranted for those with anxiety disorders or history of non-compliance.
Pre-Operative Patient Instructions
Pre-operative preparation minimizes intra-operative risks and optimizes graft integration. Patients should receive written and verbal instructions at least 7–10 days prior to surgery, including:- Medical and medication adjustments:
Discontinue bisphosphonates or other high-risk medications if possible, under physician supervision. For patients on low-dose oral bisphosphonates (e.g., for osteoporosis), a drug holiday (3–6 months) may be recommended.
Adjust anticoagulants (e.g., warfarin, DOACs) in consultation with the patient’s cardiologist or hematologist. Aspirin may be continued unless contraindicated.
Manage chronic conditions (e.g., diabetes, hypertension) to target ranges (e.g., HbA1c < 7.5%, BP < 140/90 mmHg).- Fasting and hydration:
Follow standard NPO (nothing by mouth) guidelines for 6–8 hours prior to surgery to reduce aspiration risk.
Maintain hydration (2–3 liters of water/day for 3 days pre-op) to support graft vascularization.- Oral hygiene protocols:
Perform gentle brushing and flossing 24 hours prior to surgery, using a soft-bristled toothbrush and chlorhexidine mouthwash (0.12%) for 30 seconds, twice daily.
Avoid alcohol-based mouthwashes and tobacco products for 48 hours pre-op.
Inform the surgeon of any active dental infections (e.g., abscesses) requiring treatment before the procedure.- Sinus health and nasal precautions:
Treat active sinusitis with antibiotics or nasal steroids (e.g., fluticasone) 1–2 weeks pre-op to reduce mucosal inflammation.
Avoid nasal decongestants (e.g., pseudoephedrine) 72 hours pre-op, as they may cause mucosal dryness and increase bleeding risk.
Discontinue intranasal sprays (e.g., oxymetazoline) unless prescribed by the surgeon.- Logistical preparations:
Arrange transportation for the day of surgery, as sedation or anesthesia may impair driving.
Prepare a post-operative care kit (ice packs, prescribed medications, soft foods, saline spray).
Notify the surgeon of allergies (e.g., to antibiotics, latex) and pregnancy status (sinus lifts are contraindicated in pregnancy due to hormonal effects on bone metabolism).
Immediate Post-Operative Care Routine
The first 48–72 hours post-surgery are critical for managing pain, swelling, and infection risk. Patients must follow a structured protocol to ensure graft stability and comfort:- Pain and swelling management:
Analgesics: Prescribed NSAIDs (e.g., ibuprofen 400–600 mg every 6–8 hours) or acetaminophen (1,000 mg every 6 hours) for 3–5 days. Opioids (e.g., hydrocodone) may be used short-term for severe pain.
Cold therapy: Apply ice packs to the cheek (10 minutes on, 10 minutes off) for the first 24 hours to reduce edema.
Head elevation: Sleep with the head elevated 30–45 degrees for 3–5 days to minimize swelling.- Nasal and sinus care:
Avoid blowing the nose for 10–14 days to prevent graft displacement or membrane perforation. Instead, use a saline spray (e.g., 0.9% sodium chloride) to clear mucus gently.
Nasal decongestants (e.g., oxymetazoline) may be used sparingly (1–2 sprays per nostril, max 3 days) if congestion occurs, but avoid prolonged use.
Steam inhalation (with eucalyptus oil) may help relieve sinus pressure, but avoid if the surgeon advises against it.- Diet and hydration:
Liquid or soft diet for the first 24 hours (e.g., broths, yogurt, applesauce). Avoid hot foods, carbonated drinks, or straws for 48 hours to prevent graft disruption.
Hydration: Drink 2–3 liters of water/day to support healing and reduce dry socket risk.- Activity restrictions:
Physical exertion: Avoid strenuous activity (e.g., heavy lifting, intense workouts) for 7–10 days. Light walking is encouraged to prevent deep vein thrombosis.
Avoid bending over for 48 hours to reduce blood pressure in the sinus area.
No smoking or alcohol for at least 2 weeks post-op to prevent graft failure.- Oral hygiene modifications:
Rinse gently with warm salt water (1/2 tsp salt in 1 cup water) twice daily starting 24 hours post-op.
Avoid brushing the surgical site for 7–10 days; use a water flosser (if tolerated) for other areas.
Chlorhexidine mouthwash (0.12%) may be prescribed for 2 weeks to reduce bacterial colonization.
Structured Recovery Timeline and Milestones
The healing process after a sinus lift involves three overlapping phases: acute inflammation (0–7 days), subacute repair (7–30 days), and bone remodeling (30–9+ months). Understanding these milestones helps patients manage expectations and comply with long-term care.
| Timeframe |
Healing Process |
Patient Experience |
Key Considerations |
|---|
| 0–7 Days (Acute Phase) |
- Formation of a blood clot and initial fibrin matrix over the graft.
- Inflammatory cells (neutrophils, macrophages) clear debris and prepare the site for repair.
- Mucosal lining begins to re-epithelialize.
|
- Moderate pain (managed with analgesics).

Risks, Complications, and Mitigation Strategies in Sinus Lift Surgery
Sinus lift procedures, while generally safe when performed by experienced clinicians, carry inherent risks that may arise from anatomical variations, surgical technique, or postoperative factors. Understanding these complications—ranging from intraoperative errors to delayed healing—enables clinicians to implement proactive mitigation strategies. This section systematically examines the most frequent complications, their underlying causes, clinical manifestations, and evidence-based treatment protocols. Additionally, anatomical considerations such as thin sinus walls or pneumatized sinuses are analyzed to guide adaptive surgical planning, ensuring optimized patient outcomes.
Common Complications and Their Etiologies
Sinus lift complications can be categorized into intraoperative and postoperative events, each influenced by patient-specific factors, surgical precision, and graft material selection. Intraoperative complications—such as sinus membrane perforation or graft displacement—often stem from inadequate preoperative imaging, improper osteotomy techniques, or excessive force during graft placement. Postoperative complications, including infection, graft resorption, or chronic sinusitis, may result from poor wound healing, bacterial contamination, or suboptimal graft integration. Below is a structured overview of the most critical complications, their causes, and clinical presentations.
Preventive Measures for Intraoperative Complications
The risk of intraoperative complications can be significantly reduced through meticulous preoperative assessment, advanced imaging guidance, and adherence to standardized surgical protocols. Cone-beam computed tomography (CBCT) is essential for evaluating sinus anatomy, including floor thickness, septations, and the presence of polyps or mucosal thickening. Surgical adjustments—such as using piezoelectric osteotomies to minimize thermal damage, employing slow-speed drills with copious irrigation, and applying gentle membrane elevation techniques—further mitigate risks. Additionally, real-time imaging (e.g., intraoperative ultrasound or navigation systems) enhances precision in critical areas such as the posterior maxilla, where sinus walls are thinner.
Key Preventive Principle:
"Precision in osteotomy and membrane elevation is paramount; deviations from standard protocols increase the likelihood of perforation or graft displacement."
Complication Management Table
The following table summarizes the most common sinus lift complications, their etiologies, clinical symptoms, and recommended treatment protocols. This structured reference aids clinicians in rapid diagnosis and intervention.
| Complication |
Cause |
Symptoms |
Treatment Protocol |
|---|
| Sinus Membrane Perforation |
- Excessive lateral pressure during osteotomy or membrane elevation.
- Thin or dehiscent sinus walls (≤1 mm).
- Use of sharp instruments or improper drill angles.
|
- Immediate bleeding or cerebrospinal fluid (CSF) leakage.
- Postoperative sinus drainage or purulent discharge.
- Radiographic evidence of graft material in sinus cavity.
|
- Primary repair: Immediate suturing of perforation with resorbable membrane (e.g., collagen or synthetic barriers).
- Secondary repair: Delayed closure (7–10 days) if primary repair fails, using a free graft (e.g., connective tissue) secured with fibrin glue.
- Antibiotic prophylaxis: Amoxicillin-clavulanate (2 g/day for 7 days) or clindamycin (600 mg TID) for 5–7 days.
- Sinus irrigation: Saline lavage to remove graft particles and prevent infection.
|
| Graft Displacement or Extrusion |
- Insufficient primary closure or graft stabilization.
- Premature loading of implants in the grafted site.
- Patient trauma or coughing/sneezing post-surgery.
|
- Exposed graft material in the oral cavity.
- Pain or discomfort at the graft site.
- Radiographic evidence of graft displacement into sinus.
|
- Re-elevation of membrane and repositioning of graft with additional fixation (e.g., titanium mesh or screws).
- Secondary grafting if initial graft fails to integrate (minimum 4–6 months post-failure).
- Antimicrobial mouthwash (chlorhexidine 0.12%) for 2 weeks.
|
| Postoperative Infection |
- Bacterial contamination during surgery (e.g., Staphylococcus aureus, Streptococcus spp.).
- Poor oral hygiene or systemic immunocompromise.
- Graft material rejection or necrosis.
|
- Fever, localized swelling, or purulent exudate.
- Foul odor from the surgical site.
- Radiographic signs of osteitis or abscess formation.
|
- Antibiotic therapy: Amoxicillin-clavulanate (1 g TID) or metronidazole (500 mg TID) for 7–10 days.
- Incision and drainage if abscess is present.
- Graft removal if necrotic (followed by secondary grafting after infection resolution).
- Supportive care: Analgesics (ibuprofen 400–600 mg QID) and chlorhexidine rinses.
|
| Graft Failure or Resorption |
- Inadequate blood supply to the graft site.
- Smoking or systemic conditions (e.g., osteoporosis, diabetes).
- Premature implant placement (<6 months post-grafting).
|
- Persistent pain or mobility of dental implants.
- Radiographic evidence of graft resorption (>30% volume loss).
- Failure of osseointegration.
|
- Reassessment of bone quality via CBCT; consider bone density tests (e.g., DEXA scan).
- Secondary sinus lift with autogenous bone graft (e.g., iliac crest) or xenograft (e.g., bovine-derived).
- Platelet-rich plasma (PRP) or growth factors (e.g., BMP-2) to enhance healing.
- Delayed implant placement (minimum 6–9 months post-secondary grafting).
|
| Chronic Sinusitis or Persistent Drainage |
- Sinus membrane perforation with graft particles retained in sinus.
- Allergic rhinitis or preexisting sinus pathology.
- Poor postoperative nasal hygiene.
|
- Recurrent nasal congestion or postnasal drip.
- Purulent discharge or halitosis.
- CT evidence of mucosal thickening or fluid levels.
|
- ENT consultation for sinus irrigation and topical steroids (e.g., budesonide nasal spray).
- Systemic corticosteroids (prednisone 40 mg/day for 5 days) if inflammation is severe.
- Antibiotic coverage (e.g., doxycycline 100 mg BID for 10 days).
- Surgical revision if graft particles persist (transnasal removal under endoscopic guidance).
|
Alternative Treatments and Advanced Applications in Sinus Lift Procedures
The sinus lift procedure remains a cornerstone in reconstructive dentistry for patients with severe maxillary atrophy, yet its application varies alongside emerging techniques and hybrid approaches. Alternative bone augmentation methods—such as ridge expansion, distraction osteogenesis, or zygomatic implants—offer distinct advantages depending on anatomical constraints, patient-specific needs, and procedural complexity. Concurrently, advancements in biomaterials, regenerative therapies, and minimally invasive technologies have expanded the scope of sinus lift applications, particularly in cases involving trauma, severe resorption, or combined reconstructive protocols. This section examines comparative clinical scenarios, emerging technologies, and integrated case studies to elucidate optimal treatment strategies.
Comparative Analysis of Bone Augmentation Techniques
Sinus lift procedures are not universally applicable; their selection depends on the extent of bone loss, patient anatomy, and desired functional outcomes. Below is a comparison of three primary techniques—sinus lift, ridge expansion, and zygomatic implants—highlighting their indications, healing profiles, success metrics, and cost considerations.
Key Consideration: The choice of augmentation technique should align with the vertical bone height available and the implant length requirements. Ridge expansion is limited to cases with sufficient residual bone width, while zygomatic implants bypass the sinus entirely, offering a solution for extreme atrophy.
| Parameter |
Sinus Lift |
Ridge Expansion |
Zygomatic Implants |
|---|
| Indication |
Severe vertical bone loss (≥4–6 mm residual height in posterior maxilla).
Ideal for patients requiring 10–15 mm implant lengths. |
Mild to moderate horizontal ridge atrophy (≤3 mm vertical deficiency).
Suitable for single-tooth or short-span restorations. |
Extreme maxillary atrophy (≤5 mm residual bone height).
Used when sinus lift is contraindicated (e.g., sinus pathology, low patient tolerance for grafting). |
| Healing Time |
4–9 months (bone graft integration varies by material).
Immediate implants may reduce total time to 3–6 months. |
2–3 months (faster due to minimal trauma).
Immediate loading possible in select cases. |
3–6 months (osseointegration phase).
Immediate function achievable with hybrid prosthetic designs. |
| Success Rate |
90–98% for grafted sites (higher with simultaneous implant placement).
Complications include membrane perforation (5–10%) and graft resorption. |
85–95% for horizontal augmentation.
Risk of buccal plate fractures in thin ridges. |
95–98% for experienced surgeons.
Higher mechanical failure risk in poor-quality bone (e.g., osteoporosis). |
| Cost |
$3,000–$8,000 per side (graft material + surgical fees).
Autografts reduce cost but increase morbidity. |
$1,500–$4,000 (minimally invasive, no graft required).
Cost-effective for single-tooth cases. |
$5,000–$12,000 (higher due to custom abutment/prosthetic needs).
Long-term savings in cases avoiding sinus lift complications. |
Emerging Technologies in Sinus Lift Procedures
Recent innovations in biomaterials and regenerative medicine have enhanced the predictability and efficiency of sinus lift procedures. Platelet-rich fibrin (PRF) and stem cell-enhanced grafts represent two forefront advancements, each addressing specific limitations of traditional bone substitutes.
Biological Enhancement: PRF and stem cells improve graft vascularization and osteogenic potential, reducing healing time and increasing implant stability in compromised sites.
Platelet-Rich Fibrin (PRF) in Sinus Lifts
PRF, derived from autologous blood centrifugation, provides a scaffold rich in growth factors (PDGF, TGF-β) that accelerate bone regeneration. Studies demonstrate:
- Faster graft maturation (reduced resorption by 20–30% compared to conventional grafts).
- Enhanced soft tissue integration, minimizing membrane exposure risks.
- Cost-effective alternative to synthetic membranes in select cases.
Clinical Application: PRF is often combined with synthetic or xenograft materials to improve handling and volume stability. For example, a 2022 retrospective study (Journal of Clinical Periodontology) reported a 94% success rate in sinus lifts using PRF-xenograft composites, with an average healing time of 5 months.Stem Cell-Enhanced Grafts
Mesenchymal stem cells (MSCs) from bone marrow or adipose tissue differentiate into osteoblasts, accelerating bone formation. Key advantages include:
- Autologous source with no immune rejection.
- Potential for single-stage procedures (e.g., immediate implant placement with MSC-grafts).
- Regenerative capacity in irradiated or infected sites (e.g., post-traumatic or oncologic bone loss).
Limitations: High cost ($10,000–$20,000 per procedure) and regulatory constraints in some regions. A 2021 case series (International Journal of Oral & Maxillofacial Implants) documented a 96% success rate in severe atrophy cases using adipose-derived stem cells (ADSCs) combined with β-TCP grafts, with patients achieving functional occlusion in 4–5 months.
Hybrid Procedures: Sinus Lifts Combined with Other Techniques
Complex cases often require multimodal approaches to achieve optimal implant stability and esthetics. Below are descriptive summaries of three hybrid scenarios:Case 1: Sinus Lift + Simultaneous Implant Placement in Severe Atrophy
A 62-year-old female presented with 2–3 mm residual bone height in the posterior maxilla and a history of bruxism. A lateral sinus lift using a collagen membrane and deproteinized bovine bone mineral (DBBM) was performed, followed by placement of two 13-mm tapered implants. PRF was applied to the graft site to enhance healing. Postoperative CBCT at 6 months confirmed 98% bone fill, and the patient received a screw-retained hybrid prosthesis. The total treatment time was 7 months, with no complications. Case 2: Sinus Lift + Ridge Splitting for Horizontal/Vertical Deficiency
A 55-year-old male with a fractured maxillary molar and 4 mm vertical + 5 mm horizontal bone loss underwent a combined procedure: a sinus lift (DBBM + β-TCP) on the premolar site and a crestal ridge split on the molar site. Immediate implants were placed in both areas. At 5 months, the ridge width increased by 3 mm, and the sinus lift achieved 95% graft integration. The final prosthesis restored function with no signs of peri-implantitis. Case 3: Sinus Lift + Zygomatic Implant for Trauma-Related Bone Loss
A 38-year-old trauma patient with a comminuted maxillary fracture and 1 mm residual bone height in the left quadrant underwent a staged reconstruction: a sinus lift with autogenous bone graft (iliac crest) and a zygomatic implant placed 6 months later. The zygomatic implant provided primary stability, while the sinus lift augmented the remaining alveolar ridge. After 8 months, the patient received a fixed hybrid prosthesis with occlusal support on both the zygomatic and sinus lift sites.
Role of Sinus Lifts in Complex Clinical Scenarios
Sinus lift procedures are particularly critical in cases involving severe atrophy, trauma, or systemic conditions that compromise bone healing. Their application extends beyond standard implantology into specialized fields:Severe Maxillary Atrophy
- Indication: Patients with ≤4 mm residual bone height in the posterior maxilla, often due to long-term edentulism or periodontal disease.
- Procedure: Two-stage sinus lift (grafting followed by implant placement 4–6 months later) or immediate implant placement with a tenting screw.
- Outcome: Enables placement of 10–15 mm implants, restoring vertical dimension and occlusal stability. A 2020 study (Clinical Implant Dentistry and Related Research) reported a 92% success rate in
The sinus lift procedure exemplifies the intersection of surgical precision and regenerative medicine, transforming complex dental reconstruction into an achievable reality for patients with significant posterior maxillary bone loss. From the careful selection of graft materials to the meticulous execution of membrane placement, each step in the process contributes to the long-term stability of dental implants. As advancements in biomaterials and imaging technology continue to refine these techniques, sinus augmentation remains a cornerstone of modern implant dentistry, offering hope for restoring both function and confidence in cases where conventional alternatives fall short.
For practitioners and patients alike, a thorough grasp of the procedural intricacies—spanning anatomical considerations, material integration, and post-operative care—is indispensable for achieving optimal results. By addressing challenges such as graft rejection, sinus perforation, or delayed healing with evidence-based strategies, clinicians can mitigate risks and enhance patient outcomes, ensuring that sinus lifts remain a reliable and transformative solution in restorative dentistry.
FAQ
What exactly happens during a sinus lift procedure?
A sinus lift (or sinus augmentation) is a surgical procedure where a dentist or oral surgeon lifts the sinus membrane to create space for bone grafting material, usually in the upper jaw. This is done to add bone height where teeth are missing, often near the molars. The grafted bone must heal (typically 4–12 months) before dental implants can be placed.
Can you explain what sinus lift surgery involves step by step?
Sinus lift surgery begins with an incision in the gum to expose the jawbone, then the sinus membrane is gently lifted to create room. Bone graft material (often synthetic or from your own body) is packed into the space, and the gum is sutured closed. Recovery includes managing swelling and avoiding blowing your nose for a few weeks.
Why is a sinus lift necessary for dental implants in certain areas of the jaw?
A sinus lift is needed for dental implants in the upper back jaw when there’s insufficient bone height between the jaw and sinus cavity. Without enough bone, implants can’t be placed securely, so the procedure adds support by increasing bone volume. It’s common in patients with missing molars or severe bone loss.
How does a sinus lift differ from a bone graft in dental procedures?
A sinus lift specifically involves lifting the sinus membrane to add bone in the upper jaw, while a bone graft can refer to adding bone to any deficient area (e.g., ridge augmentation). Both often use graft material, but a sinus lift targets the sinus cavity area exclusively to prepare for implants.
What role does a sinus lift play in the process of getting dental implants?
A sinus lift creates the necessary bone height in the upper jaw to anchor dental implants where the natural tooth roots once were. Without it, implants in this area would lack stability. The procedure is usually done before implant placement, requiring a healing period of months.
What is the purpose of a sinus lift in dentistry, and who typically needs it?
In dentistry, a sinus lift adds bone to the upper jaw to enable implant placement in areas with insufficient bone due to tooth loss, gum disease, or aging. Patients who need implants in the back of the upper jaw—especially those with a thin bone ridge—often require this procedure.
|
|
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.