What Is The Average Blood Sugar Reading And Its Clinical Significance
Table of Contents
- Understanding Blood Sugar Basics
- Biological Role of Glucose in the Human Body
- Fasting vs. Postprandial Blood Sugar Levels
- Blood Sugar Target Ranges for Different Populations
- Regulation of Blood Sugar by Insulin and Glucagon
- Factors Influencing Average Blood Sugar Readings
- Physiological and Lifestyle Factors Affecting Blood Sugar
- Medical Conditions Altering Blood Sugar Averages
- Medications Affecting Blood Sugar Levels
- Average Blood Sugar Ranges Across Demographics
- Blood Sugar Trends in Non-Diabetic, Pediatric, and Elderly Populations
- Blood Sugar Targets in Pregnant Women and Gestational Diabetes
- Ethnicity and Genetic Predispositions in Blood Sugar Regulation
- Blood Sugar Differences Between Active and Sedentary Individuals
- Methods for Measuring and Tracking Blood Sugar
- Continuous Glucose Monitors (CGMs) vs. Traditional Finger-Prick Tests
- Interpreting Blood Sugar Trends Over Time
- Structured Blood Sugar Logging with HTML Table Format
- Role of HbA1c in Estimating Average Blood Sugar Clinical Implications of Deviations from Average Blood Sugar Readings Blood sugar deviations—whether consistently elevated (hyperglycemia) or depressed (hypoglycemia)—have immediate physiological consequences and long-term systemic effects that can alter quality of life and increase mortality risk. Short-term symptoms often serve as warning signs, while chronic deviations accelerate organ damage, metabolic dysfunction, and secondary comorbidities. Understanding these correlations enables timely intervention and aligns with evidence-based guidelines, such as those from the American Diabetes Association (ADA), which prioritize individualized target ranges to mitigate complications. The relationship between blood sugar fluctuations and health outcomes is dose-dependent: prolonged exposure to hyperglycemia or hypoglycemia disrupts cellular metabolism, vascular integrity, and neural function. Below, the clinical pathways linking deviations to acute symptoms and chronic diseases are outlined, followed by comparative risk assessments and critical diagnostic red flags. Pathophysiological Correlations Between Blood Sugar Deviations and Health Outcomes
- American Diabetes Association Guidelines for Blood Sugar Management
- Comparative Risks of Chronic Hyperglycemia vs. Hypoglycemia
- Red Flags in Blood Sugar Patterns Requiring Medical Evaluation
- FAQ
- what is the healthy blood sugar reading?
- what is the average blood sugar level?
- what is the average blood sugar level for adults?
- what is the average blood sugar level for diabetics?
- what is the average blood sugar level after eating?
- what is the average blood sugar level for a male?
Blood sugar, or glucose, serves as the body’s primary energy source, yet maintaining its balance is critical to metabolic health. Understanding what constitutes an average blood sugar reading is essential for diagnosing conditions like diabetes, optimizing athletic performance, and preventing long-term complications. From the moment glucose enters circulation following a meal to its regulation by hormones like insulin and glucagon, fluctuations in these levels reflect both physiological precision and lifestyle influences. This discussion explores the scientific foundations of blood sugar dynamics, dissecting how demographics, medical conditions, and monitoring techniques shape individual averages—and why deviations carry profound clinical implications.
The human body operates within a delicate equilibrium where fasting and postprandial glucose levels adhere to distinct physiological thresholds. For non-diabetic adults, these ranges typically span 70–99 mg/dL (3.9–5.5 mmol/L) before meals and peak at 140 mg/dL (7.8 mmol/L) or below two hours after eating. However, variations emerge across populations—from gestational diabetes in pregnancy to insulin resistance in elderly individuals—highlighting the need for personalized targets. Beyond biological factors, external elements such as medication interactions, stress responses, and monitoring errors can distort readings, underscoring the importance of accurate measurement. By examining these variables, we uncover not only the mechanics of glucose regulation but also the broader implications for public health and clinical practice.
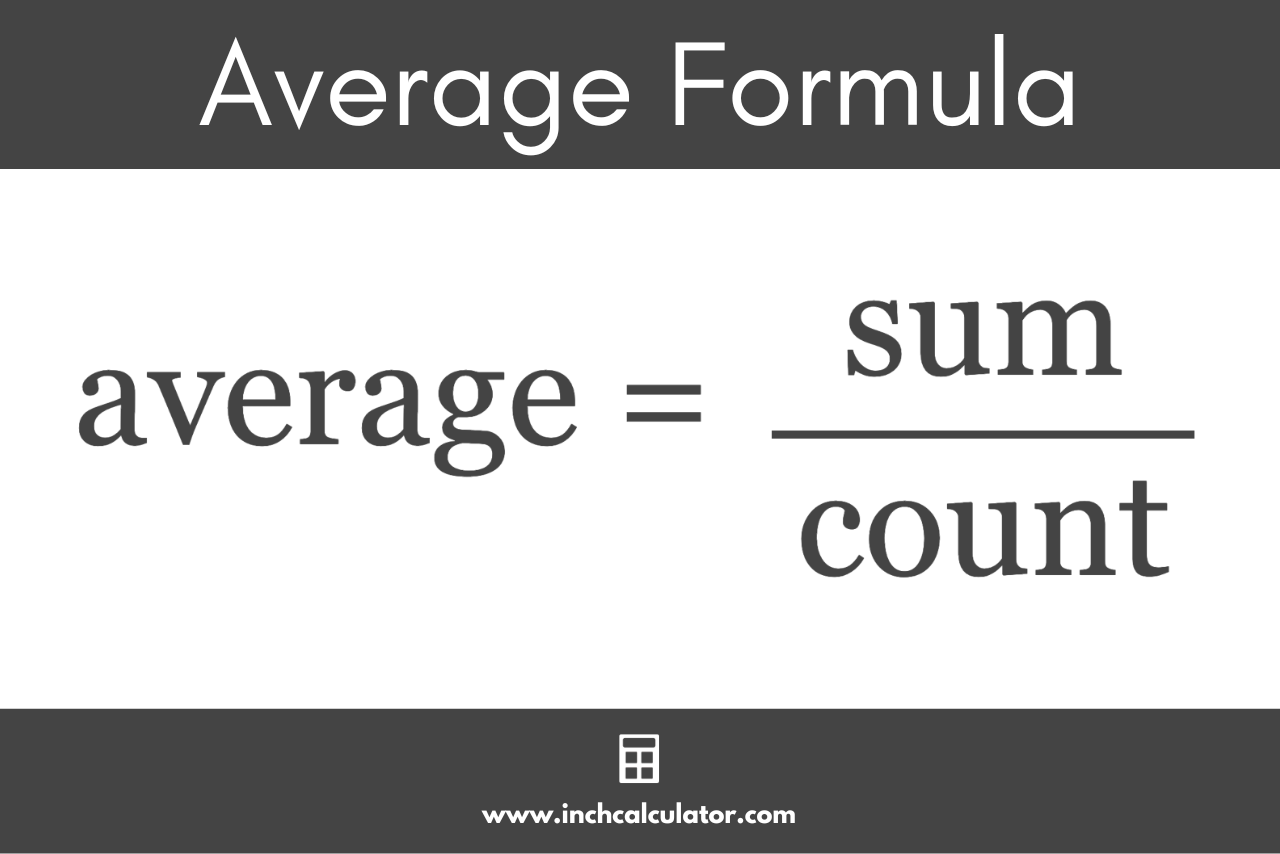
Understanding Blood Sugar Basics
Blood sugar, or glucose, is the primary energy source for the human body, fueling cellular metabolism, brain function, and physical activity. Derived from dietary carbohydrates, proteins, and fats, as well as endogenous production (e.g., gluconeogenesis), glucose is absorbed primarily in the small intestine and transported via the bloodstream to tissues. Cells utilize glucose through aerobic respiration to produce adenosine triphosphate (ATP), the energy currency of biological processes. Disruptions in glucose homeostasis—whether due to excessive intake, hormonal imbalances, or metabolic disorders—can lead to hyperglycemia (elevated blood sugar) or hypoglycemia (low blood sugar), both of which pose significant health risks.The regulation of blood sugar involves a delicate balance between fasting and postprandial states, each governed by distinct physiological mechanisms. Fasting blood sugar reflects glucose levels after an overnight fast (typically 8–12 hours), while postprandial levels measure the body’s response to carbohydrate ingestion. These states are critical for assessing metabolic health, with deviations often serving as early indicators of conditions such as diabetes or insulin resistance.
Biological Role of Glucose in the Human Body
Glucose serves as the immediate energy substrate for nearly all cells, particularly neurons, which rely exclusively on glucose for metabolic function. The body maintains blood glucose within a narrow range (70–99 mg/dL in fasting adults) through tightly regulated processes involving insulin secretion from pancreatic beta cells and glucagon release from alpha cells. Beyond energy production, glucose participates in glycogen synthesis (short-term storage in liver and muscle) and lipogenesis (long-term fat storage when excess). Additionally, glucose contributes to the formation of structural components like glycoproteins and glycolipids, essential for cell signaling and membrane integrity.The absorption of glucose occurs primarily in the small intestine via active transport mechanisms, including the sodium-glucose linked transporter 1 (SGLT1) and glucose transporter 2 (GLUT2). These processes are influenced by dietary composition, gut motility, and hormonal signals such as incretins (e.g., GLP-1), which enhance insulin secretion in response to meals. In the absence of exogenous glucose, the liver initiates gluconeogenesis, converting non-carbohydrate substrates (e.g., lactate, glycerol) into glucose to sustain energy demands during fasting or prolonged exercise.
Fasting vs. Postprandial Blood Sugar Levels
Fasting blood sugar levels represent the baseline glucose concentration after an overnight fast, reflecting the body’s ability to maintain energy stability without recent carbohydrate intake. In healthy adults, fasting glucose typically ranges between 70–99 mg/dL (3.9–5.5 mmol/L), with values below 70 mg/dL indicating hypoglycemia and above 126 mg/dL (diagnostic for diabetes) suggesting impaired fasting glucose (IFG) or diabetes mellitus. Postprandial glucose, measured 1–2 hours after a meal, assesses the body’s insulin sensitivity and carbohydrate metabolism. Optimal postprandial levels are generally <140 mg/dL (7.8 mmol/L) in non-diabetic individuals, though this threshold may vary based on age, activity level, and underlying health conditions.The distinction between fasting and postprandial states is critical for clinical evaluation, as each state is influenced by different physiological pathways. For example, fasting glucose is primarily regulated by hepatic glucose production and peripheral glucose uptake, while postprandial levels are driven by insulin-mediated glucose disposal in muscle and adipose tissue. Prolonged elevations in postprandial glucose—often observed in insulin-resistant states—are associated with increased cardiovascular risk and microvascular complications.
Blood Sugar Target Ranges for Different Populations
Blood sugar targets vary across populations due to differences in metabolic demands, hormonal profiles, and disease states. Below is a comparative table outlining recommended ranges for fasting and postprandial glucose in key demographic groups, based on clinical guidelines from organizations such as the American Diabetes Association (ADA) and the International Diabetes Federation (IDF).| Condition | Fasting Blood Sugar Range (mg/dL) | Postprandial Blood Sugar Range (mg/dL, 1–2 hours post-meal) | Timeframe for Measurement | Notes |
|---|---|---|---|---|
| Healthy Adults (Non-Diabetic) | 70–99 | <140 | Fasting: 8–12 hours post-meal; Postprandial: 1–2 hours after carbohydrate intake | Variations may occur with age, physical activity, or pregnancy. |
| Adults with Prediabetes | 100–125 | 140–199 | Same as above | Indicates increased risk for type 2 diabetes; lifestyle modifications recommended. |
| Adults with Type 1 Diabetes | 80–130 | <180 | Fasting: Before breakfast; Postprandial: Peak response (typically 1–2 hours) | Individualized targets based on age, duration of diabetes, and hypoglycemia risk. |
| Adults with Type 2 Diabetes | 80–130 | <180 | Same as above | Tighter control may be advised for younger patients or those with short diabetes duration. |
| Pregnant Women (Gestational Diabetes) | 70–95 | <140 (1-hour post-meal) or <120 (2-hour post-meal) | Fasting: Overnight; Postprandial: 1 or 2 hours after meal | Screening typically occurs at 24–28 weeks gestation; tight control reduces fetal complications. |
| Children and Adolescents (Non-Diabetic) | 70–99 | <140 | Same as adults | Children may exhibit wider fluctuations due to growth and developmental stages. |
| Children and Adolescents with Type 1 Diabetes | 90–130 | <180 | Fasting: Before morning activities; Postprandial: 1–2 hours after meals | Targets adjusted for age, puberty, and school schedules. |
Regulation of Blood Sugar by Insulin and Glucagon
The endocrine pancreas plays a pivotal role in maintaining glucose homeostasis through the counterregulatory actions of insulin and glucagon, two hormones secreted by the islets of Langerhans. Insulin, produced by beta cells, is the primary anabolic hormone that lowers blood glucose by facilitating its uptake into peripheral tissues (muscle, adipose) and inhibiting hepatic glucose production. Glucagon, secreted by alpha cells, exerts catabolic effects, stimulating glycogenolysis and gluconeogenesis to elevate blood glucose during fasting or hypoglycemia.Mechanisms of Insulin Action:
Mechanisms of Glucagon Action:
Factors Influencing Average Blood Sugar Readings
Blood sugar levels are dynamic and influenced by a complex interplay of physiological processes, lifestyle choices, and underlying medical conditions. While short-term fluctuations occur naturally in response to meals or activity, long-term averages reflect the balance between glucose production, utilization, and regulatory mechanisms. Understanding these influences is critical for individuals managing conditions like diabetes, prediabetes, or metabolic disorders, as well as those seeking to optimize metabolic health. This section examines the key determinants of average blood sugar, categorized into physiological, lifestyle-related, and pathological factors, alongside common pitfalls in monitoring accuracy.Physiological and Lifestyle Factors Affecting Blood Sugar
The body maintains blood glucose homeostasis through hormonal regulation, cellular uptake, and hepatic glucose metabolism. Lifestyle factors further modulate these processes, often leading to predictable yet variable shifts in glycemic control.Dietary Composition and Timing
Diet is the primary exogenous factor influencing blood sugar. The glycemic index (GI) and glycemic load (GL) of carbohydrates determine the speed and magnitude of postprandial glucose spikes. Foods high in refined sugars (e.g., sucrose, fructose) or rapidly digestible starches (e.g., white bread, potatoes) trigger acute hyperglycemia, often peaking 1–2 hours post-meal. Conversely, low-GI foods (e.g., whole grains, legumes, non-starchy vegetables) promote gradual glucose release, reducing fluctuations. Fiber, protein, and healthy fats (e.g., monounsaturated oils, omega-3s) further attenuate glycemic responses by slowing gastric emptying and enhancing insulin sensitivity. Meal timing also plays a role: skipping meals or prolonged fasting (e.g., overnight) can induce nocturnal hypoglycemia, while irregular eating patterns disrupt circadian rhythms linked to glucose metabolism.
Physical Activity and Exercise
Exercise lowers blood sugar by increasing glucose uptake in skeletal muscle (via GLUT4 translocation) and improving insulin sensitivity. Aerobic activities (e.g., walking, cycling) and resistance training both contribute, though their effects differ:
However, excessive or unaccustomed exercise can paradoxically raise blood sugar via stress hormone (e.g., cortisol, adrenaline) secretion or muscle glycogen depletion triggering gluconeogenesis.
Stress and Cortisol Response
Chronic stress elevates cortisol, which promotes gluconeogenesis in the liver and reduces insulin sensitivity in peripheral tissues. Acute stress (e.g., illness, trauma) can cause stress hyperglycemia, even in non-diabetic individuals, via adrenaline-mediated glycogenolysis. Psychological stress (e.g., anxiety, depression) may also impair glucose tolerance through altered autonomic nervous system activity and inflammatory pathways. Sleep deprivation exacerbates this effect by increasing cortisol levels and reducing growth hormone secretion, which normally enhances insulin sensitivity.
Sleep Patterns and Circadian Rhythms
Sleep quality and duration critically influence glucose metabolism. Short sleep duration (<6 hours/night) is associated with:
Medical Conditions Altering Blood Sugar Averages
Pathological conditions disrupt glucose homeostasis through hormonal imbalances, pancreatic dysfunction, or systemic inflammation. Below are key disorders and their mechanisms, along with typical blood sugar profiles.Diabetes Mellitus and Prediabetes
Thyroid Disorders
Pancreatic and Hepatic Diseases
Inflammatory and Autoimmune Conditions
Medications Affecting Blood Sugar Levels
Pharmacological agents can significantly alter glucose metabolism, either as primary therapeutic targets or secondary effects. Below is a categorized list with mechanisms and typical glycemic impacts.Medications That Raise Blood Sugar
Drugs increasing glucose levels primarily act through gluconeogenesis stimulation, insulin resistance, or reduced insulin secretion.
-
Glucocorticoids (e.g., prednisone, dexamethasone)
Mechanism: Enhances hepatic glucose production via cortisol-like effects; reduces peripheral glucose uptake by downregulating GLUT4. Also impairs insulin signaling in muscle and adipose tissue.
Impact: Fasting glucose may rise by 30–50 mg/dL; postprandial spikes can exceed 200 mg/dL in susceptible individuals. Risk of new-onset diabetes in prolonged use (>2 weeks).
-
Beta-2 Agonists (e.g., albuterol, salmeterol)
Mechanism: Stimulates β2-adrenergic receptors, increasing glycogenolysis and lipolysis. Chronic use reduces insulin sensitivity.
Impact: Acute hyperglycemia (100–150 mg/dL increase) during asthma exacerbations; long-term use associated with T2D risk.
-
Thiazide Diuretics (e.g., hydrochlorothiazide)

Average Blood Sugar Ranges Across Demographics
Blood sugar regulation varies significantly across different population groups due to physiological, lifestyle, and genetic factors. Understanding these variations is critical for diagnosing metabolic disorders, tailoring treatment plans, and implementing preventive measures. This section examines how age, gender, pregnancy, ethnicity, genetic predispositions, and physical activity influence average blood sugar levels, supported by empirical data and clinical guidelines.
Blood Sugar Trends in Non-Diabetic, Pediatric, and Elderly Populations
Average blood sugar levels differ across the lifespan, reflecting developmental stages and age-related metabolic changes. Non-diabetic adults typically maintain stable glucose levels, whereas children and the elderly exhibit distinct patterns influenced by growth, hormonal shifts, and declining pancreatic function.Non-Diabetic Adults (Ages 18–64)
- Fasting glucose: 70–99 mg/dL (3.9–5.5 mmol/L).
- Postprandial (2-hour): ≤140 mg/dL (≤7.8 mmol/L).
- Gender variations: Minimal differences exist, though women may exhibit slightly higher postprandial spikes due to hormonal fluctuations (e.g., menstrual cycle phases). Studies suggest estrogen’s role in insulin sensitivity may lead to marginal variations in glucose metabolism.
- Infants (0–2 years): Fasting glucose ranges from 60–100 mg/dL (3.3–5.6 mmol/L), with higher postprandial peaks (≤180 mg/dL or 10.0 mmol/L) due to rapid glucose utilization for growth.
- Children (2–12 years): Fasting levels align with adults (70–99 mg/dL), but postprandial targets may extend to ≤160 mg/dL (≤8.9 mmol/L) in some pediatric guidelines, reflecting higher metabolic demand.
- Adolescents (13–18 years): Approaches adult ranges, though insulin resistance (e.g., during puberty) may elevate fasting levels to 90–100 mg/dL (5.0–5.6 mmol/L) in some individuals.
- Fasting glucose: 80–100 mg/dL (4.4–5.6 mmol/L), with a broader acceptable range due to age-related insulin resistance and reduced beta-cell function.
- Postprandial: ≤160 mg/dL (≤8.9 mmol/L), though thresholds may be relaxed to ≤180 mg/dL (≤10.0 mmol/L) in frail elderly to account for reduced glucose tolerance.
- Gender-specific trends: Postmenopausal women exhibit higher fasting glucose (up to 95 mg/dL or 5.3 mmol/L) due to decreased estrogen, while older men may show greater variability linked to testosterone decline and sarcopenia.
- Hormonal influences: Placental hormones (e.g., human placental lactogen) antagonize insulin, reducing glucose uptake in maternal tissues and elevating postprandial levels.
- Ethnic disparities: Women of South Asian, Hispanic, or Indigenous descent exhibit higher GDM prevalence (up to 20–30%) due to genetic predispositions and higher rates of obesity.
- Monitoring frequency: Weekly glucose testing is recommended for high-risk groups, with tighter targets (fasting <90 mg/dL) in women with preexisting diabetes.
- South Asians: Higher prevalence of type 2 diabetes (T2D) (up to 12–15% in some populations) despite lower BMI. Genetic variants in TCF7L2 and PPARG genes are strongly associated with impaired insulin secretion and resistance.
- African Americans: Increased risk of T2D (13.4% prevalence) linked to ADRB3 and CAPN10 gene variants, which affect adiposity and insulin signaling.
- Hispanic/Latino populations: Elevated diabetes risk (12.8%) due to KCNJ11 mutations, which impair potassium channel function in pancreatic beta cells.
- Native Americans/Indigenous populations: Highest T2D rates globally (up to 50% in some tribes), attributed to MTNR1B variants and historical dietary shifts.
- A meta-analysis in Diabetologia (2018) found that individuals of African or South Asian descent had 1.5–2.3 times higher odds of developing diabetes at lower BMI thresholds compared to European populations.
- The UK Biobank study (2020) reported that carriers of the TCF7L2 risk allele had fasting glucose levels 5–10 mg/dL higher than non-carriers, independent of obesity.
- Personalized screening: Ethnic-specific thresholds may be warranted (e.g., fasting glucose ≥92 mg/dL for South Asians).
- Pharmacogenomics: Medications like metformin may require dose adjustments based on genetic profiles (e.g., MAT1A variants affecting drug metabolism).
- Active individuals (moderate-to-vigorous exercise ≥150 mins/week):
- Fasting glucose: 80–90 mg/dL (4.4–5.0 mmol/L), 10–15% lower than sedentary counterparts.
- Postprandial glucose: ≤120 mg/dL (≤6.7 mmol/L) due to improved muscle glycogen storage.
- Meta-analysis (Diabetes Care, 2019): Exercise reduced HbA1c by 0.3–0.6% in pre-diabetic adults, equivalent to a 20–30 mg/dL reduction in average glucose.
- Fasting glucose: 90–100 mg/dL (5.0–5.6 mmol/L), with higher variability.
- Postprandial glucose: ≥160 mg/dL (≥8.9 mmol/L) in 30–40% of cases, linked to visceral adiposity.
- Study (JAMA, 2021): Sedentary adults had 2.5-fold higher risk of developing prediabetes over 5 years compared to active peers.
- Muscle contraction: Activates AMPK pathways, enhancing GLUT4 translocation and glucose uptake.
- Ne
- Sensor placement errors: Improper insertion depth or location (e.g., near muscle or scar tissue) can distort readings.
- Delayed calibration: Skipping calibrations leads to drift, where sensor readings deviate from actual glucose levels.
- Interference from substances: Alcohol, high triglycerides, or certain medications (e.g., acetaminophen) may cause temporary inaccuracies.
- Sensor lifespan: Most sensors last 7–14 days; replacing them before expiration prevents signal degradation.
- CGMs: Provide trends, alerts for high/low glucose, and retrospective data but may lag by 5–15 minutes behind actual blood glucose. Accuracy varies (±10–15 mg/dL or 10–15%).
- Finger-prick tests: Offer precise point-in-time measurements but are invasive and less frequent. Accuracy depends on proper technique (±5–10%).
- In-range: 70–180 mg/dL (3.9–10.0 mmol/L) for most adults; narrower ranges (e.g., 70–140 mg/dL) may apply to individuals with tighter targets.
- Above range: >180 mg/dL (>10.0 mmol/L), indicating hyperglycemia.
- Below range: <70 mg/dL (<3.9 mmol/L), signaling hypoglycemia.
- Dawn phenomenon: Morning hyperglycemia due to hormonal surges.
- Somogyi effect: Nocturnal hypoglycemia followed by rebound hyperglycemia.
- Postprandial peaks: Glucose spikes 1–2 hours after meals.
- Ignoring context: A single high reading may reflect stress or illness rather than dietary patterns.
- Over-reliance on alerts: CGM alerts (e.g., for hypoglycemia) should be confirmed with finger-prick tests if symptoms are absent.
- Sensor artifacts: Movement or edema can cause temporary inaccuracies; exclude these outliers from analysis.
- Timestamp: Records the exact time of measurement, critical for identifying patterns (e.g., dawn phenomenon).
- Reading (mg/dL/mmol/L): Dual units accommodate global audiences; ensure consistency in logging.
- Food intake: Details carbohydrate content, fat/protein ratios, and timing relative to insulin administration.
- Activity level: Categorized as low, moderate, or high to assess physical activity’s impact on glucose.
- Notes: Captures contextual factors (e.g., illness, medication changes, or emotional stress) that may influence readings.
- Frequency: Record readings at least 4–6 times daily (pre/post-meals, bedtime) for CGMs; align finger-prick tests with CGM calibrations.
- Consistency: Use the same units and time format (e.g., 24-hour clock) throughout.
- Digital integration: Export logs to apps like Diabetes:M or Glooko for automated trend analysis and HbA1c predictions.
- Microvascular damage: Chronic hyperglycemia promotes glycation of hemoglobin (HbA1c), collagen, and lipoproteins, thickening basement membranes in capillaries. This impairs oxygen diffusion, leading to retinopathy (blindness), nephropathy (end-stage renal disease), and neuropathy (painful peripheral nerve damage).
- Macrovascular disease: Persistent hyperglycemia accelerates atherosclerosis via oxidative stress and endothelial dysfunction, increasing cardiovascular risk by 2–4 times compared to normoglycemia. Hypoglycemia, while less studied, may independently contribute to cardiovascular events through autonomic dysfunction and arrhythmias.
- Metabolic syndrome progression: Insulin resistance, a hallmark of type 2 diabetes, worsens with repeated hyperglycemic spikes, creating a vicious cycle of β-cell dysfunction and dyslipidemia.
- Hypoglycemia (<70 mg/dL or 3.9 mmol/L):
- Mild (70–54 mg/dL / 3.9–3.0 mmol/L): Oral glucose (15–20 g) or glucagon gel; retest in 15 minutes.
- Severe (<54 mg/dL / 3.0 mmol/L or unconscious): Glucagon injection (1 mg IM/SC) or IV dextrose (25–50 mL of 50% solution).
- Hyperglycemia:
- Prediabetes (100–125 mg/dL / 5.6–6.9 mmol/L): Lifestyle modification (diet, exercise) to delay progression.
- Diabetes (fasting ≥126 mg/dL / 7.0 mmol/L or HbA1c ≥6.5%): Target 70–130 mg/dL (3.9–7.2 mmol/L) preprandial and <180 mg/dL (10.0 mmol/L) postprandial. Adjust insulin/medications if targets persistently missed.
- Diabetic ketoacidosis (DKA) (>250 mg/dL / 13.9 mmol/L with ketones): Emergency treatment with IV fluids, insulin, and electrolyte correction.
- Polyuria, polydipsia, unexplained weight loss.
- Slow-healing wounds, recurrent infections (e.g., UTIs, skin abscesses).
- Fatigue, blurred vision, erectile dysfunction.
- Advanced stages: Nephropathy (proteinuria), retinopathy (floaters), autonomic neuropathy (gastroparesis).
- Correct with insulin/medications; monitor ketones if >250 mg/dL.
- Hydrate; seek emergency care for DKA/HHS.
- HbA1c <7% (or <6.5% for young/healthy individuals).
- Low-carbohydrate/mediterranean diet; regular physical activity.
- SGLT2 inhibitors or GLP-1 agonists for renal/cardiovascular protection.
- Adrenergic symptoms (tachycardia, sweating, anxiety) followed by neuroglycopenic symptoms (confusion, slurred speech).
- Seizures or coma at <50 mg/dL (<2.8 mmol/L).
- Long-term: Cognitive impairment, increased fall risk in elderly.
- Autonomic failure (e.g., hypoglycemia unawareness).
- 15–20 g rapid-acting carbohydrate; retest in 15 minutes.
- Glucagon for unconscious patients; call emergency services.
- Tight glucose monitoring; adjust insulin doses or switch to basal-only regimens.
- Educate on carbohydrate counting and snack timing.
- Continuous glucose monitors (CGMs) to detect trends pre-symptomatically.
- Avoid sulfonylureas/metformin in high-risk groups.
- Possible causes: Unrecognized DKA, insulin resistance, or medication non-adherence (e.g., missed doses of metformin/SGLT2 inhibitors).
- Action: Check ketones; evaluate for stress hyperglycemia (e.g., infection, pancreatitis).
- Possible causes: Sulfonylurea overdose,
Average blood sugar readings are more than numerical benchmarks; they are a window into metabolic health, reflecting the interplay between genetics, environment, and medical interventions. Whether through continuous glucose monitoring, HbA1c trends, or traditional finger-prick tests, precise tracking empowers individuals to preempt complications like neuropathy or cardiovascular disease before symptoms arise. The clinical significance of these readings extends beyond diabetes, influencing treatment strategies for thyroid disorders, pancreatitis, and even athletic training regimens. By synthesizing physiological data, demographic trends, and monitoring best practices, this exploration underscores a critical message: vigilance in blood sugar management is not merely reactive but a proactive cornerstone of long-term well-being. For patients, caregivers, and healthcare providers alike, mastery of these averages equips stakeholders to navigate the complexities of glucose regulation with confidence and precision.
Children and Adolescents (Ages 0–18)
Elderly Population (Ages 65+)
Blood Sugar Targets in Pregnant Women and Gestational Diabetes
Pregnancy induces significant metabolic adaptations, increasing the risk of gestational diabetes mellitus (GDM), defined as glucose intolerance first detected during pregnancy. The American Diabetes Association (ADA) and International Association of Diabetes and Pregnancy Study Groups (IADPSG) provide trimester-specific targets to mitigate maternal and fetal complications.| Trimester | Fasting Target (mg/dL) | 1-Hour Postprandial Target (mg/dL) | 2-Hour Postprandial Target (mg/dL) |
|---|---|---|---|
| First Trimester | 60–90 | 130–140 | 120 |
| Second Trimester | 60–95 | 135–145 | 120 |
| Third Trimester | 60–95 | 135–140 | 120 |
| Diagnostic Thresholds (IADPSG) | — | ≥180 (1-hour) | ≥153 (2-hour) |
Ethnicity and Genetic Predispositions in Blood Sugar Regulation
Genetic and ethnic backgrounds significantly influence blood sugar homeostasis, with certain populations exhibiting higher susceptibility to diabetes and altered glucose metabolism. These variations stem from polymorphisms in genes regulating insulin secretion, glucose uptake, and beta-cell function.High-Risk Ethnic Groups and Genetic Markers
Statistical Insights:
Clinical Implications:
Blood Sugar Differences Between Active and Sedentary Individuals
Physical activity enhances insulin sensitivity, reduces hepatic glucose production, and increases glucose uptake in skeletal muscles. Sedentary lifestyles, conversely, promote insulin resistance and elevated blood sugar levels, even in non-diabetic individuals.Comparative Data from Observational Studies
- Sedentary individuals (≤30 mins/week of physical activity):
Mechanisms and Lifestyle Interventions
Methods for Measuring and Tracking Blood Sugar
Accurate monitoring of blood sugar is essential for managing diabetes and preventing complications. While traditional methods rely on periodic finger-prick tests, advancements in technology—such as continuous glucose monitors (CGMs)—provide real-time, data-driven insights into glucose fluctuations. This section explores the procedural differences between CGMs and finger-prick tests, the interpretation of long-term trends, and the practical application of structured logging. Additionally, the role of HbA1c in estimating average glucose levels over extended periods is examined for its clinical relevance.Continuous Glucose Monitors (CGMs) vs. Traditional Finger-Prick Tests
CGMs and finger-prick tests serve distinct purposes in blood sugar management, differing in accuracy, frequency, and calibration requirements. CGMs use a subcutaneous sensor to measure interstitial fluid glucose levels every 1–15 minutes, transmitting data wirelessly to a receiver or smartphone app. In contrast, finger-prick tests provide immediate capillary blood glucose readings but require manual sampling and are less frequent.Steps for Accurate CGM Use
CGMs demand meticulous adherence to calibration protocols to ensure accuracy. Most systems require at least two daily finger-prick calibrations (typically before meals and at bedtime) to adjust sensor readings against reference values. However, newer models (e.g., factory-calibrated CGMs) eliminate this step by using proprietary algorithms. Common pitfalls include:
Steps for Accurate Finger-Prick Testing
Finger-prick tests rely on a glucometer and test strips to measure blood glucose. Key steps include:
1. Hand preparation: Warm the fingertip (e.g., by rubbing or using a warm cloth) to improve blood flow.
2. Lancing: Use a lancet at a 90° angle to the finger pad (avoiding the center to minimize pain).
3. Sample collection: Gently squeeze the finger to obtain a large enough blood drop (0.5–1.0 µL) for the strip.
4. Reading: Wait for the glucometer’s result (typically 5–30 seconds) and record the value.
5. Post-test care: Apply gentle pressure to the puncture site and avoid reusing lancets.
Comparison of Accuracy and Limitations
Interpreting Blood Sugar Trends Over Time
CGMs generate extensive data, enabling analysis of patterns such as daily variability, nocturnal hypoglycemia, and postprandial spikes. Time-in-range (TIR) reports are a cornerstone of this analysis, categorizing glucose levels into clinically relevant ranges:Calculating Averages from CGM Data
To derive meaningful averages, follow these steps:
1. Data aggregation: Export CGM data (e.g., from Dexcom or Freestyle Libre) into a spreadsheet or analysis tool.
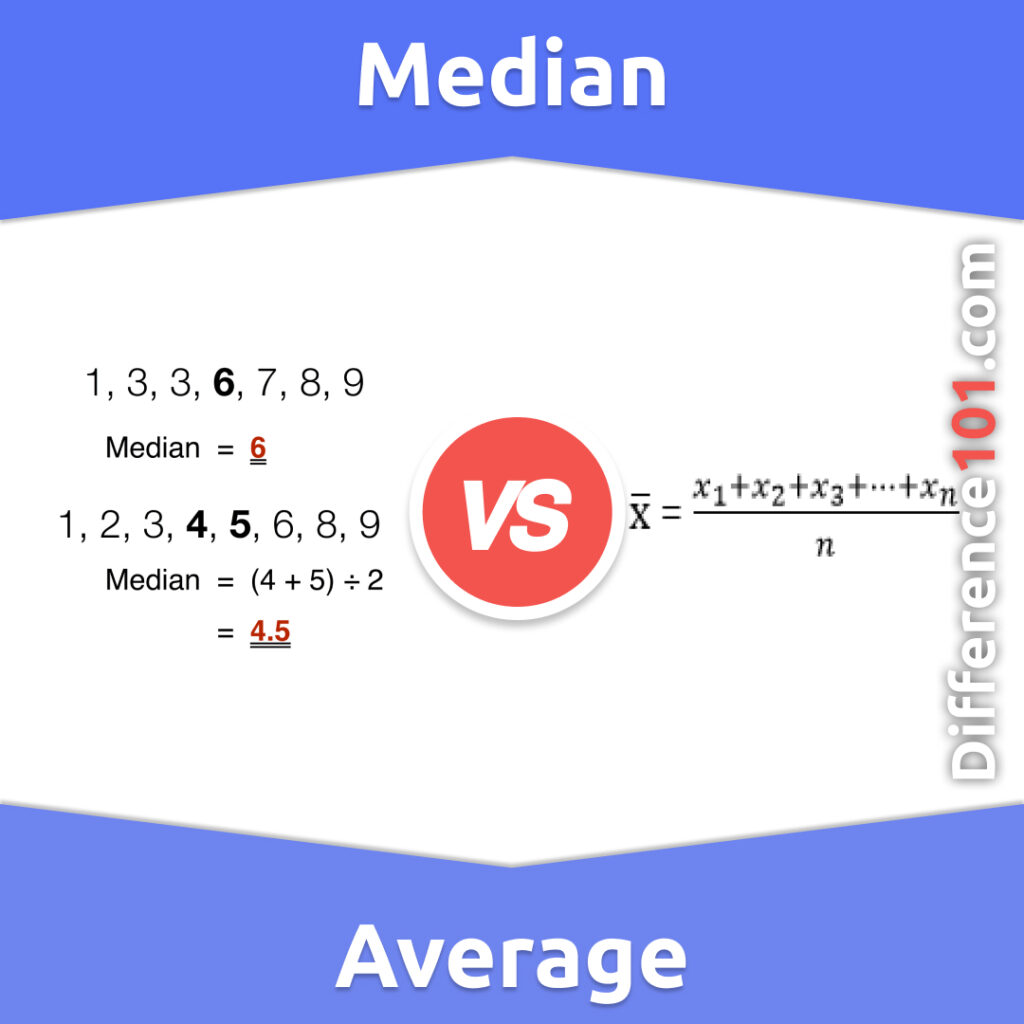
2. Time-weighted averaging: Calculate the mean glucose level by summing all readings and dividing by the total number of data points. For example:
Average glucose (mg/dL) = (Σ all glucose readings) / (total readings)
3. Estimated average glucose (eAG): Convert the mean glucose into an HbA1c-equivalent using the formula:
eAG (mg/dL) ≈ 28.7 × HbA1c (%) – 46.7
Example: An average glucose of 150 mg/dL correlates with an eAG of ~7.0% HbA1c.
4. Trend analysis: Identify patterns such as:
Common Pitfalls in Trend Interpretation
Structured Blood Sugar Logging with HTML Table Format
Maintaining a daily blood sugar log enhances self-awareness and facilitates discussions with healthcare providers. Below is a template for a structured log, incorporating key variables that influence glucose levels. The table uses UTF-8 encoding for compatibility with international units (mg/dL or mmol/L).| Timestamp | Reading (mg/dL) | Reading (mmol/L) | Food Intake | Activity Level | Notes |
|---|---|---|---|---|---|
| 2023-11-15 07:30 | 145 | 8.0 | Breakfast: 2 slices whole-grain toast + 1 tbsp peanut butter | Moderate (walked 10 min) | Felt fatigued; possible overnight hypoglycemia |
| 2023-11-15 12:00 | 190 | 10.6 | Lunch: Grilled chicken salad with olive oil dressing | Low (desk job) | Stress at work; skipped pre-lunch insulin dose |
| 2023-11-15 18:45 | 120 | 6.7 | Dinner: Baked salmon + quinoa + steamed broccoli | High (30-min yoga session) | Used rapid-acting insulin; no post-meal spike |
| 2023-11-15 23:00 | 105 | 5.8 | None | Low (sleeping) | CGM alert for low trend; ate 15g glucose before bed |
Key Columns Explained
Best Practices for Logging
Role of HbA1c in Estimating Average Blood Sugar
Clinical Implications of Deviations from Average Blood Sugar Readings
Blood sugar deviations—whether consistently elevated (hyperglycemia) or depressed (hypoglycemia)—have immediate physiological consequences and long-term systemic effects that can alter quality of life and increase mortality risk. Short-term symptoms often serve as warning signs, while chronic deviations accelerate organ damage, metabolic dysfunction, and secondary comorbidities. Understanding these correlations enables timely intervention and aligns with evidence-based guidelines, such as those from the American Diabetes Association (ADA), which prioritize individualized target ranges to mitigate complications.The relationship between blood sugar fluctuations and health outcomes is dose-dependent: prolonged exposure to hyperglycemia or hypoglycemia disrupts cellular metabolism, vascular integrity, and neural function. Below, the clinical pathways linking deviations to acute symptoms and chronic diseases are outlined, followed by comparative risk assessments and critical diagnostic red flags.
Pathophysiological Correlations Between Blood Sugar Deviations and Health Outcomes
Short-term symptoms arise from acute metabolic imbalances that impair cellular energy production and neurotransmitter function. For example, hyperglycemia exceeding 180–250 mg/dL (10–13.9 mmol/L) triggers osmotic diuresis, leading to dehydration, blurred vision (due to lens swelling), and fatigue from impaired glucose uptake in peripheral tissues. Conversely, hypoglycemia below 70 mg/dL (3.9 mmol/L) disrupts glucose-dependent organs like the brain, causing confusion, tremors, and seizures as counterregulatory hormones (e.g., epinephrine, glucagon) fail to compensate.Long-term complications emerge from cumulative cellular stress, including:
A 2018 meta-analysis in The Lancet Diabetes & Endocrinology demonstrated that for every 1% decrease in HbA1c, the risk of microvascular complications drops by 37%, while macrovascular benefits plateau at HbA1c <7% due to residual oxidative damage.
American Diabetes Association Guidelines for Blood Sugar Management
The ADA’s Standards of Medical Care in Diabetes emphasize personalized glycemic targets based on age, comorbidities, and hypoglycemia risk. Key interventions are stratified by severity:
ADA Target Ranges for Intervention:
The ADA also recommends time-in-range (TIR) analysis (70–180 mg/dL / 3.9–10.0 mmol/L) as a primary metric, with >70% TIR associated with reduced complications. For individuals at high hypoglycemia risk (e.g., elderly, insulin users), targets may be relaxed to 90–150 mg/dL (5.0–8.3 mmol/L) to balance safety and efficacy.
Comparative Risks of Chronic Hyperglycemia vs. Hypoglycemia
While hyperglycemia is more commonly associated with diabetes, hypoglycemia—particularly severe or recurrent—poses distinct risks, including cognitive decline and mortality. The following table contrasts their clinical profiles:
Condition
Symptoms
Immediate Actions
Preventive Measures
Chronic Hyperglycemia
Chronic Hypoglycemia
Note: Hypoglycemia unawareness develops in 25–30% of patients with type 1 diabetes and 10–20% with type 2 diabetes, increasing accident and mortality risk. The ADA recommends hypoglycemia awareness training and CGM use to mitigate this.
Red Flags in Blood Sugar Patterns Requiring Medical Evaluation
Erratic or unexplained blood sugar trends may indicate underlying pathologies, treatment failures, or emergent conditions. The following patterns warrant immediate assessment:- Unexplained spikes (>250 mg/dL / 13.9 mmol/L) without clear triggers (e.g., illness, diet):
- Recurrent hypoglycemia (<70 mg/dL / 3.9 mmol/L) despite adjustments:
FAQ
what is the healthy blood sugar reading?
Q: What is considered a healthy blood sugar reading for a person without diabetes?
what is the average blood sugar level?
Q: What is the average blood sugar level in a healthy population?
what is the average blood sugar level for adults?
Q: What is the average blood sugar level for adults without diabetes?
what is the average blood sugar level for diabetics?
Q: What is the average blood sugar level for someone with diabetes?
what is the average blood sugar level after eating?
Q: What is the average blood sugar level after eating a meal?
what is the average blood sugar level for a male?
Q: What is the average blood sugar level for a male?
Clinical Implications of Deviations from Average Blood Sugar Readings
Blood sugar deviations—whether consistently elevated (hyperglycemia) or depressed (hypoglycemia)—have immediate physiological consequences and long-term systemic effects that can alter quality of life and increase mortality risk. Short-term symptoms often serve as warning signs, while chronic deviations accelerate organ damage, metabolic dysfunction, and secondary comorbidities. Understanding these correlations enables timely intervention and aligns with evidence-based guidelines, such as those from the American Diabetes Association (ADA), which prioritize individualized target ranges to mitigate complications.The relationship between blood sugar fluctuations and health outcomes is dose-dependent: prolonged exposure to hyperglycemia or hypoglycemia disrupts cellular metabolism, vascular integrity, and neural function. Below, the clinical pathways linking deviations to acute symptoms and chronic diseases are outlined, followed by comparative risk assessments and critical diagnostic red flags.
Pathophysiological Correlations Between Blood Sugar Deviations and Health Outcomes
Short-term symptoms arise from acute metabolic imbalances that impair cellular energy production and neurotransmitter function. For example, hyperglycemia exceeding 180–250 mg/dL (10–13.9 mmol/L) triggers osmotic diuresis, leading to dehydration, blurred vision (due to lens swelling), and fatigue from impaired glucose uptake in peripheral tissues. Conversely, hypoglycemia below 70 mg/dL (3.9 mmol/L) disrupts glucose-dependent organs like the brain, causing confusion, tremors, and seizures as counterregulatory hormones (e.g., epinephrine, glucagon) fail to compensate.Long-term complications emerge from cumulative cellular stress, including:
A 2018 meta-analysis in The Lancet Diabetes & Endocrinology demonstrated that for every 1% decrease in HbA1c, the risk of microvascular complications drops by 37%, while macrovascular benefits plateau at HbA1c <7% due to residual oxidative damage.
American Diabetes Association Guidelines for Blood Sugar Management
The ADA’s Standards of Medical Care in Diabetes emphasize personalized glycemic targets based on age, comorbidities, and hypoglycemia risk. Key interventions are stratified by severity:ADA Target Ranges for Intervention:The ADA also recommends time-in-range (TIR) analysis (70–180 mg/dL / 3.9–10.0 mmol/L) as a primary metric, with >70% TIR associated with reduced complications. For individuals at high hypoglycemia risk (e.g., elderly, insulin users), targets may be relaxed to 90–150 mg/dL (5.0–8.3 mmol/L) to balance safety and efficacy.
Comparative Risks of Chronic Hyperglycemia vs. Hypoglycemia
While hyperglycemia is more commonly associated with diabetes, hypoglycemia—particularly severe or recurrent—poses distinct risks, including cognitive decline and mortality. The following table contrasts their clinical profiles:| Condition | Symptoms | Immediate Actions | Preventive Measures |
|---|---|---|---|
| Chronic Hyperglycemia | |||
| Chronic Hypoglycemia |
Red Flags in Blood Sugar Patterns Requiring Medical Evaluation
Erratic or unexplained blood sugar trends may indicate underlying pathologies, treatment failures, or emergent conditions. The following patterns warrant immediate assessment:- Unexplained spikes (>250 mg/dL / 13.9 mmol/L) without clear triggers (e.g., illness, diet):
- Recurrent hypoglycemia (<70 mg/dL / 3.9 mmol/L) despite adjustments:
FAQ
what is the healthy blood sugar reading?
Q: What is considered a healthy blood sugar reading for a person without diabetes?
what is the average blood sugar level?
Q: What is the average blood sugar level in a healthy population?
what is the average blood sugar level for adults?
Q: What is the average blood sugar level for adults without diabetes?
what is the average blood sugar level for diabetics?
Q: What is the average blood sugar level for someone with diabetes?
what is the average blood sugar level after eating?
Q: What is the average blood sugar level after eating a meal?
what is the average blood sugar level for a male?
Q: What is the average blood sugar level for a male?
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.