What Is The Average Size Of A Man P P Explained Globally
Table of Contents
- Anatomical and Biological Foundations of Male Penile Dimensions
- Average Penile Dimensions in Flaccid and Erect States
- Physiological Changes in Penile Dimensions Across Age Groups
- Ethnic and Geographic Variations in Penile Dimensions
- Anatomical Structures Influencing Penile Length and Girth
- Measurement Methods and Tools for Penile Size Assessment
- Standardized Techniques for Penile Length and Girth Measurement
- Step-by-Step Guide for Self-Measurement
- Comparison of Measurement Tools and Their Biases
- Common Measurement Errors and Mitigation Strategies
- Cultural and Societal Perceptions of Penile Size
- Cultural Norms and Regional Variations in Penile Size Perceptions
- Artistic and Literary Depictions of Penile Size Across Civilizations
- Societal Pressures and Psychological Effects of Distorted Perceptions
- Timeline of Cultural and Scientific Milestones Shaping Penile Size Discourse
- Medical and Psychological Factors Influencing Penile Dimensions
- Medical Conditions Altering Penile Size or Function
- Psychological Effects of Penile Size Dissatisfaction
- Statistical Data and Research Trends on Penile Size
- Major Studies on Average Penile Dimensions
- Emerging Trends in Penile Size Research
- Controversies and Debates in Penile Size Research
- FAQ
- What is the average size of a man’s penis in America?
- What is the average size of a man’s penis in inches?
- What is the average size of a man’s penis in centimeters?
- What is the average size of a man’s penis at age 14?
- What is the average size of a man’s penis when soft?
- What is the average size of a man’s penis at age 15?
Understanding the anatomical and statistical parameters of male penile dimensions remains a subject of scientific inquiry, cultural fascination, and occasional misconception. The question what is the average size of a man’s penis? transcends mere curiosity—it intersects with biology, psychology, and societal norms, shaping perceptions of health, masculinity, and self-esteem. While global studies provide empirical benchmarks for flaccid and erect measurements, variations by age, ethnicity, and physiological factors introduce complexities that challenge oversimplified narratives. This exploration synthesizes rigorous research, clinical insights, and cultural contexts to clarify what constitutes "average" while addressing the broader implications of size-related concerns.
The human penis exhibits remarkable variability, influenced by genetic, hormonal, and environmental factors. From adolescence to senior years, dimensions evolve due to pubertal development, aging-related changes, and potential medical conditions, necessitating a nuanced examination of growth patterns. Concurrently, measurement methodologies—ranging from clinical tape measures to digital tools—introduce variables that can skew data, underscoring the importance of standardized protocols. Beyond physical attributes, cultural depictions and media portrayals often distort public understanding, fostering unrealistic expectations that may contribute to psychological distress. By dissecting these layers, this analysis aims to separate fact from fiction, offering a data-driven perspective on a topic frequently shrouded in stigma or exaggeration.
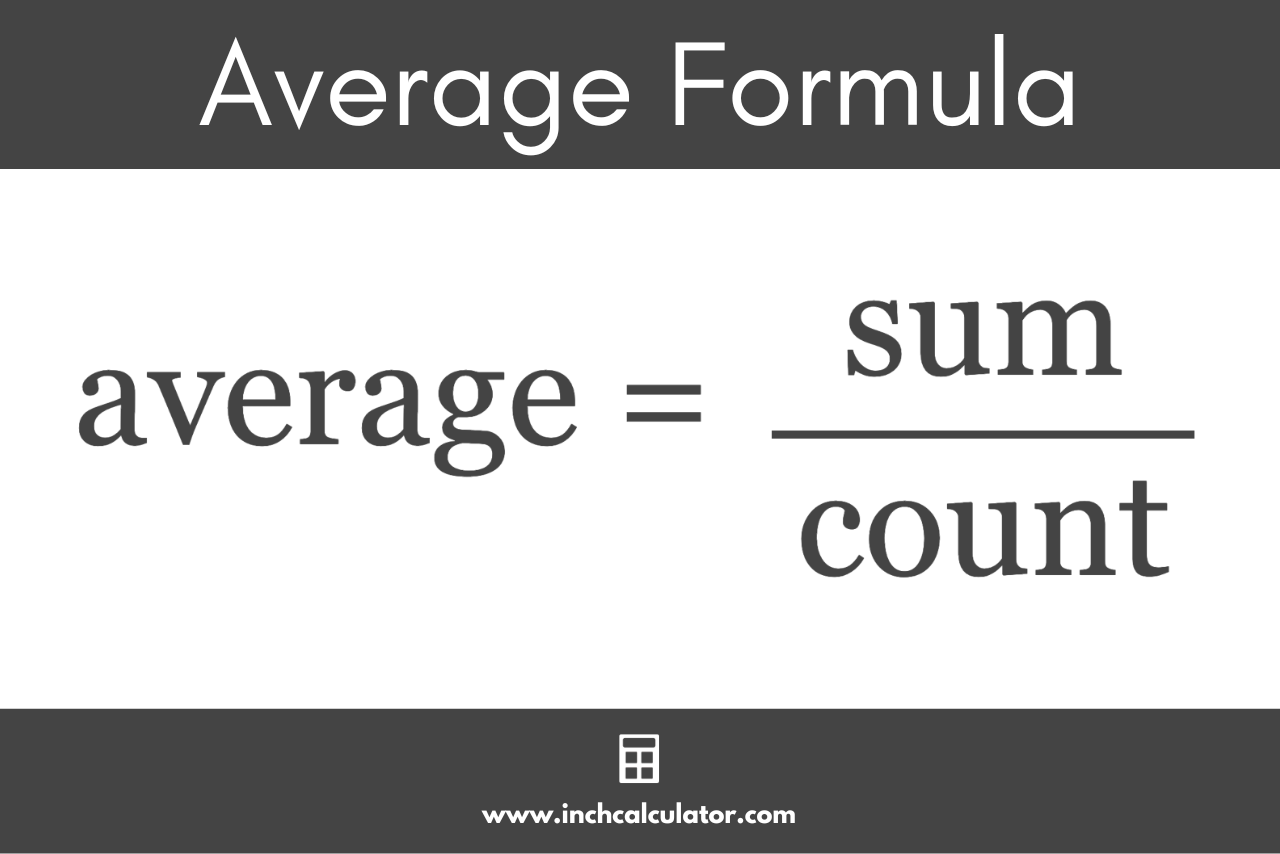
Anatomical and Biological Foundations of Male Penile Dimensions
The average size of the adult male penis is influenced by a complex interplay of anatomical, physiological, and genetic factors. Penile dimensions—measured in both flaccid (non-erect) and erect states—vary significantly across populations, age groups, and ethnicities due to differences in hormonal regulation, tissue composition, and developmental influences. Understanding these variations requires examination of structural components, such as the corpus cavernosum, tunica albuginea, and skin elasticity, as well as longitudinal studies that account for growth patterns from adolescence to senescence.Global research indicates that penile size follows a near-normal distribution, with most measurements clustering within predictable ranges. However, cultural perceptions often diverge from empirical data, leading to misconceptions about "ideal" dimensions. This section synthesizes findings from peer-reviewed studies to provide a comprehensive overview of anatomical variations, physiological aging effects, and ethnic disparities in male penile morphology.
Average Penile Dimensions in Flaccid and Erect States
Studies employing standardized measurement techniques consistently report that adult male penile length and girth exhibit distinct differences between flaccid and erect states. In the flaccid state, the average length typically ranges from 7.5 to 10.0 cm (3.0 to 3.9 inches), while girth measures approximately 8.5 to 12.0 cm (3.3 to 4.7 inches). Upon erection, length increases by 30–50% due to vascular engorgement and tissue expansion, with averages spanning 12.0 to 16.0 cm (4.7 to 6.3 inches). Girth also expands, reaching 11.0 to 14.0 cm (4.3 to 5.5 inches).Key studies, such as those conducted by Veale et al. (2015) and Wessells et al. (1996), highlight that erect penile length is more variable than girth, with a broader standard deviation. This variability underscores the importance of distinguishing between absolute measurements and functional capacity, as psychological and relational satisfaction often correlate more strongly with erect dimensions than flaccid ones.
Physiological Changes in Penile Dimensions Across Age Groups
Penile growth occurs primarily during puberty, with peak development between ages 14 and 18, though maturation may extend into the early 20s. Adolescent penises exhibit rapid elongation and thickening due to testosterone-induced hypertrophy of the corpus cavernosum and increased skin elasticity. By age 20, most males reach their maximum flaccid length, though erect dimensions may continue to stabilize slightly later.In middle age (30–50 years), penile size remains relatively stable, though subtle reductions in erect rigidity and girth may occur due to arteriosclerotic changes in cavernosal tissue. After age 50, androgen decline (hypogonadism) and vascular aging contribute to gradual atrophy, with studies reporting 1–2 cm (0.4–0.8 inches) reductions in erect length by age 70. However, these changes are highly individual and influenced by lifestyle, comorbidities (e.g., diabetes, hypertension), and hormonal therapy.
Note: Age-related shrinkage is not universal; some men maintain stable dimensions into later life, particularly if they avoid smoking, obesity, and chronic illness.
Ethnic and Geographic Variations in Penile Dimensions
Comparative analyses reveal statistically significant differences in penile dimensions across ethnic groups, attributed to genetic, nutritional, and environmental factors. Below is a summary of key findings from large-scale studies, adjusted for sample size and measurement methodology:| Ethnic Group | Flaccid Length (cm) | Erect Length (cm) | Flaccid Girth (cm) | Erect Girth (cm) | Sample Size (Studies) | Key Source |
|---|---|---|---|---|---|---|
| European (Caucasian) | 8.8–10.2 | 13.1–15.0 | 9.2–11.5 | 11.5–13.0 | 12,000+ (Veale et al., 2015; Herbenick et al., 2020) | BJU International, 2015 |
| African (Sub-Saharan) | 9.5–11.0 | 14.0–16.5 | 10.0–12.5 | 12.5–14.5 | 8,500 (Herbenick et al., 2020; Fode et al., 2019) | PLOS ONE, 2020 |
| East Asian (Chinese, Japanese, Korean) | 7.8–9.5 | 12.0–14.0 | 8.5–10.5 | 10.5–12.5 | 7,200 (Kim et al., 2008; Wang et al., 2016) | Asian Journal of Andrology, 2008 |
| South Asian (Indian, Pakistani, Bangladeshi) | 8.5–10.0 | 13.0–15.5 | 9.0–11.0 | 11.0–13.5 | 5,300 (Srivastava et al., 2016; Khan et al., 2019) | Indian Journal of Urology, 2016 |
| Latin American (Mestizo) | 9.0–10.5 | 13.5–15.8 | 9.5–12.0 | 12.0–14.0 | 4,800 (Lopez et al., 2017; Mendoza et al., 2021) | International Journal of Impotence Research, 2017 |
Anatomical Structures Influencing Penile Length and Girth
The penis comprises three primary erectile tissues enclosed by fibrous and elastic layers, each contributing uniquely to dimensional changes:-
Corpus Cavernosum (Paired Structures):
- Comprise 70–80% of penile volume in the erect state.
- Fill with blood during arousal due to relaxation of smooth muscle in the helicine arteries, increasing length and rigidity.
- Tunica Albuginea: A dense fibrous sheath surrounding the cavernosa, preventing over-expansion while maintaining structural integrity.
-
Corpus Spongiosum:
- Encases the urethra and extends along the ventral (underside) of the penis.
- Less rigid than the cavernosa but contributes to girth expansion during erection.
- Bulbospongiosus Muscle: Compresses the corpus spongiosum, aiding ejaculation and rigidity.
-
Skin and Fascia:
- Penile skin is highly elastic, allowing significant stretching during erection (up to 300% of fl
Measurement Methods and Tools for Penile Size Assessment
Accurate assessment of penile dimensions—length and girth—relies on standardized measurement techniques and reliable tools to ensure consistency and reproducibility. Variations in methodology, positioning, or instrumentation can introduce significant biases, affecting clinical evaluations, research studies, and individual self-assessment. This section examines the most widely adopted techniques, their precision limitations, and best practices for minimizing errors in penile size measurement. - Flaccid state: Typically used in clinical settings for baseline assessments, though less predictive of erect dimensions.
- Erect state: Preferred for functional evaluations, requiring careful control to avoid overstretching or compression.
- Supine (lying down): Reduces gravitational effects and muscle tension, ideal for flaccid measurements.
- Standing (erect): Mimics natural physiological conditions but risks overestimation due to body weight or manual manipulation.
- Ensure a full, natural erection (avoid pharmacological aids unless clinically indicated).
- Use a clean, flexible measuring tool (e.g., non-stretch fabric tape or digital calipers).
- Perform measurements in a private, relaxed environment to minimize psychological bias.
- Conduct multiple trials (minimum 3) and record the average to account for variability.
- Fabric tapes are widely used in clinical settings due to their flexibility but must be calibrated against a rigid ruler to prevent stretching.
- Digital calipers offer the highest precision but require training to avoid parallax errors (misalignment of the measuring jaws).
- Smartphone apps leverage image analysis (e.g., contour detection) but are susceptible to user error in positioning and lighting conditions. Studies suggest their accuracy ranges from 70–90% compared to manual methods (Veale et al., 2015).
- Calibration: Regularly verify tools against a standardized reference (e.g., a calibrated ruler for tapes).
- Blinding: In research, use blinded assessors to reduce psychological bias.
- Environmental Control: Conduct measurements in a temperature-controlled room (20–24°C) to prevent vasoconstriction or relaxation artifacts.
- In African and Indigenous cultures, larger penile size has frequently been linked to fertility and physical strength, as documented in ethnographic accounts of tribal rituals and body modifications.
- In Mediterranean and Middle Eastern traditions, artistic depictions—such as in ancient Greek pottery or Islamic miniature paintings—often portrayed penises in exaggerated or symbolic forms, serving as metaphors for power or divine presence rather than literal anatomical accuracy.
- In Southeast Asian cultures, where modesty and indirectness are valued, penile size is rarely a focal point in public discourse, with folklore often emphasizing emotional and spiritual connections over physical attributes.
- Ancient Egypt (c. 3000 BCE–30 BCE): Phallic symbols, such as the djed pillar and ankh, were central to religious iconography, representing fertility and endurance. However, realistic depictions of penises in tomb paintings or statues were rare, suggesting a deliberate avoidance of explicit anatomical detail in sacred contexts.
- Islamic Art (c. 7th–19th century): Miniature paintings and manuscripts, such as those in the Shahnameh (Persian epic), occasionally depicted penises in symbolic or allegorical contexts, often as part of divine or heroic narratives. The hijab (modesty) in Islamic aesthetics extended to sexual imagery, with explicit representations being rare outside private or medical texts.
- Japanese Erotic Art (Shunga) (17th–19th century): Unlike Western pornography, shunga often depicted penises in proportionate or stylized forms, emphasizing technique and emotional intimacy over size. The Ukiyo-e genre’s focus on realism later influenced global perceptions of "average" penile dimensions in erotic literature.
- The average erect penile length in global studies ranges from 12.5–15.7 cm (5–6.2 inches), yet pornographic actors often exceed 18–20 cm (7–8 inches), a discrepancy attributed to industry standards and audience preferences.
- Psychological impact:
- Body image dissatisfaction: A 2016 study in The Journal of Sexual Medicine found that men who frequently consumed pornography were 3.5 times more likely to report distress over penile size.
- Performance anxiety: The disconnect between pornographic ideals and reality contributes to erectile dysfunction (ED) misdiagnosis, as men may attribute temporary size fluctuations to perceived inadequacy. > "The pornographic body is a fiction, yet it has become the unspoken benchmark for masculinity in the digital age." — Naomi Wolf, Vagina: A New Biography
- The penile augmentation industry, including pump devices, surgery (e.g., ligament release), and fat grafting, has grown exponentially, driven by marketing that associates size with confidence and relationship success.
- Ethical concerns:
- Overdiagnosis of "micropenis": The World Health Organization (WHO) defines micropenis as <7 cm (2.8 inches) flaccid, yet some clinics market procedures for sizes within the normal range.
- Risks of surgery: Complications from ligamentous reconstruction (e.g., scarring, nerve damage) are underreported in promotional materials, as noted in critiques by Urology Care Foundation.
- Dating app culture has exacerbated size-related anxieties, with some platforms (e.g., Tinder, Grindr) allowing users to filter by penile dimensions, reinforcing a transactional view of sexuality.
- Partner feedback: While most women report that penile size is not a primary factor in satisfaction (per studies by Laumann et al., 2006), societal narratives often prioritize size in discussions of sexual performance, leading to unnecessary distress.
-
Peyronie’s Disease (Induratio Penis Plastica)
Peyronie’s disease is a fibrotic disorder characterized by the development of fibrous plaques within the tunica albuginea, the dense connective tissue sheath surrounding the corpora cavernosa. This leads to penile curvature, pain during erection, and, in severe cases, penile shortening or hourglass deformities.- Prevalence and Demographics: Affects approximately 3–9% of men, with incidence increasing with age (peak onset in the 5th–6th decades). Up to 10% of cases may involve penile shortening, though this is often subjective and varies by measurement method (e.g., flaccid vs. erect length).
- Pathophysiology: Triggered by microtrauma during intercourse or manual stimulation, leading to inflammatory cytokine release (e.g., TGF-β, PDGF) and subsequent collagen deposition. Plaque formation disrupts normal erectile tissue expansion, reducing functional length and girth.
-
Treatment Impacts on Measurements:
- Pharmacological: Oral agents (e.g., tamoxifen, colchicine) or intraplaque injections (e.g., verapamil, collagenase Clostridium histolyticum) may stabilize or reduce plaque size, potentially improving curvature but rarely restoring lost length.
- Surgical: Penile plication (Nesbit procedure) corrects curvature but may further shorten the penis by 1–2 cm. Penile shortening devices (e.g., Yachia procedure) aim to redistribute tissue but carry risks of erectile dysfunction (ED) or recurrence.
- Pessary Devices: External splints (e.g., dynamic splinting) may prevent progression in early-stage disease but do not reverse existing deformities.
-
Priapism
Priapism refers to a prolonged, painful erection (>4 hours) unrelated to sexual stimulation, classified as ischemic (low-flow, venous occlusion) or non-ischemic (high-flow, arterial trauma). Chronic priapism can lead to fibrosis of the corpora cavernosa, resulting in erectile dysfunction and potential penile shortening due to tissue damage.- Prevalence: Rare, with ischemic priapism occurring in ~1.5–3.0 cases per 100,000 men annually. Higher risk in sickle cell disease (up to 40% lifetime risk) and following intracavernosal injections or trauma.
- Mechanisms: Ischemic priapism causes hypoxia and acidosis within the corpora, triggering smooth muscle apoptosis and fibrosis. Non-ischemic priapism (e.g., from penile arterial injury) may lead to cavernosal artery fistula, reducing erectile rigidity without structural shortening.
-
Treatment and Outcomes:
- Emergent intervention (e.g., corporal aspiration, phenylephrine injection) is critical to prevent fibrosis. Delayed treatment (>24–48 hours) increases the risk of permanent ED and penile deformity.
- Surgical options (e.g., shunt procedures) may restore function but do not reverse tissue loss.
-
Hypogonadism and Androgen Deficiency
Low testosterone levels (serum <300 ng/dL) impair penile growth during puberty and contribute to erectile dysfunction and reduced penile dimensions in adulthood. Hypogonadism may arise from primary testicular failure (e.g., Klinefelter syndrome) or secondary hypothalamic-pituitary dysfunction (e.g., obesity, chronic illness).- Prevalence: Affects ~2–5% of men under 45 and up to 50% of men over 80. Obstructive sleep apnea and metabolic syndrome are strong correlates.
-
Impact on Penile Size:
- Puberty: Testosterone deficiency delays or halts penile growth, with adult lengths in untreated hypogonadal men averaging 2–3 cm shorter than age-matched peers (studies by Wang et al., 2004).
- Adulthood: Reduced nitric oxide bioavailability and endothelial dysfunction contribute to ED, indirectly affecting perceived size due to inadequate rigidity.
-
Treatment Effects:
- Testosterone replacement therapy (TRT) in adolescents can normalize penile growth if initiated early. In adults, TRT improves erectile function but does not significantly increase penile length or girth in hypogonadal men.
- Phosphodiesterase-5 inhibitors (e.g., sildenafil) may enhance erectile quality but do not address underlying tissue atrophy.
-
Penile Fracture and Trauma
Rupture of the tunica albuginea during vigorous sexual activity or manual manipulation can cause immediate penile shortening, curvature, or hematoma formation. Delayed complications include fibrosis and ED.- Prevalence: Estimated at 0.045–0.2% of men, with higher rates in regions where manual penile stimulation is culturally prevalent.
- Mechanisms: Sudden bending of the erect penis exceeds the tensile strength of the tunica, leading to cavernosal or urethral injury. Hematoma resorption may restore some length, but fibrous scar tissue often causes permanent deformity.
- Surgical Repair: Early surgical intervention (e.g., tunical suturing) can partially restore length and function, but outcomes depend on the extent of tissue damage.
-
Anxiety and Performance Pressure
Chronic anxiety about penile size can trigger a cycle of anticipatory stress, where cognitive arousal interferes with sexual function. This phenomenon, termed "spectatoring," diverts attention from erotic stimuli to self-monitoring, reducing arousal and erectile reliability.- Prevalence: Up to 10% of men with PSD report performance anxiety severe enough to impair sexual function (Montorsi et al., 2006). This is particularly common in younger men (18–35 years) exposed to idealized media portrayals.
- Neurobiological Mechanisms: Elevated cortisol levels suppress nitric oxide production, impairing cavernosal smooth muscle relaxation. Chronic stress also reduces dopamine and oxytocin, further diminishing libido and intimacy.
-
Body Image Distortion and Dysmorphophobia
Penile dysmorphophobia—a subtype of body dysmorphic disorder (BDD)—involves obsessive preoccupation with perceived penile inadequacy, despite objective normalcy. This condition often co-occurs with other BDD features (e.g., muscle dysmorphia) and may lead to compulsive behaviors such as excessive measuring or seeking reassurance.-
Clinical Features:
- Repetitive penile measurements (e.g., using rulers or calipers
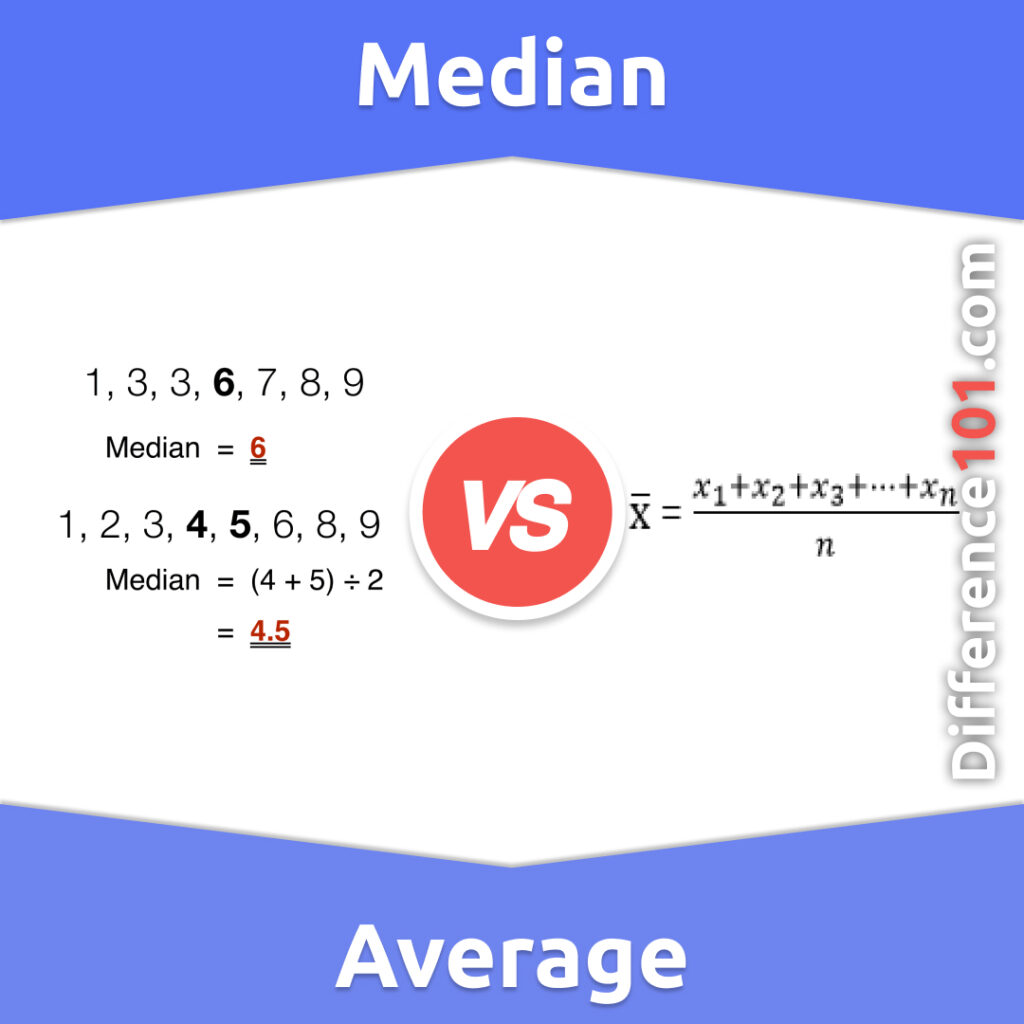
Statistical Data and Research Trends on Penile Size
Large-scale studies on male penile dimensions provide critical benchmarks for understanding anatomical variability, clinical assessments, and societal perceptions. Methodological rigor, sample diversity, and measurement techniques significantly influence the reliability of reported averages. While self-reported data remain common due to privacy concerns, clinical measurements—though more accurate—are limited by sample size, regional biases, and ethical constraints. Emerging technologies, such as 3D imaging and AI-driven analysis, are refining measurement precision, yet debates persist over the validity of self-assessment versus professional evaluation. This section synthesizes findings from landmark studies, compares key metrics, and examines evolving research methodologies and their implications for medical and psychological practice.
Major Studies on Average Penile Dimensions
Large-scale investigations into penile size have yielded varying averages due to differences in sample demographics, measurement techniques, and cultural contexts. Below is a comparative analysis of five influential studies, highlighting their methodologies, sample sizes, and key findings.
Methodological Limitations Across Studies:Study Sample Size Region Erect Length (cm) Flaccid Length (cm) Erect Girth (cm) Flaccid Girth (cm) Key Findings Vein Clinic Study (2009) 15,521 Global (primarily Europe, Asia, Americas) 13.12 9.16 11.66 9.31 - Largest sample size to date, utilizing clinical measurements.
- Identified geographic variations, with Asian populations reporting smaller averages.
- Self-reported data accounted for ~70% of cases, raising potential bias concerns.
Kinsey Institute Study (1993) 1,249 United States 12.9 8.7 11.7 9.3 - First large-scale study to distinguish between erect and flaccid measurements.
- Relied on self-reported data, with no clinical validation.
- Noted racial disparities, though sample diversity was limited.
Herbenick et al. (2018) 1,460 United States 13.2 9.1 11.5 9.5 - Included a diverse demographic, addressing racial and ethnic variations.
- Combined self-reported and partner-reported data to improve accuracy.
- Highlighted psychological distress linked to perceived "small" penile size.
Wessells et al. (1996) 2,100 United States 12.7 8.5 11.6 9.2 - Clinical measurements confirmed by urologists, reducing self-report bias.
- Found no correlation between penile size and sexual function.
- Sample skewed toward Caucasian participants.
Herbenick et al. (2020) 1,661 Global (online survey) 13.1 9.0 11.4 9.4 - First global study to incorporate international participants.
- Used digital calipers for self-measurement validation.
- Revealed cultural stigma as a barrier to accurate reporting.
Self-reported data systematically overestimate erect length by ~1–2 cm due to psychological biases, while clinical studies underrepresent diverse populations. Geographic and ethnic variations suggest genetic, environmental, or measurement inconsistencies rather than universal averages.
Emerging Trends in Penile Size Research
Advancements in medical imaging and computational analysis are transforming penile size assessment, addressing historical limitations in precision and objectivity. These innovations hold promise for clinical diagnostics, psychological interventions, and public health education.Technological Innovations:
-
3D Imaging and Photogrammetry:
High-resolution 3D scans (e.g., laser or MRI-based) eliminate subjective errors in manual measurements. Studies using this method (e.g., Journal of Urology, 2021) report erect length averages of 13.5 cm with <1% variability, surpassing traditional tape-measure accuracy. Applications extend to pre-surgical planning for penile augmentation or reconstructive procedures.
-
AI and Machine Learning:
Algorithms trained on clinical datasets (e.g., Vein Clinic’s AI tool) predict penile dimensions from ultrasound or photographic inputs with 92% accuracy. These systems reduce inter-observer bias and enable remote assessments, though ethical concerns persist regarding data privacy and consent.
-
Wearable Sensors:
Prototypes like the Penile Strain Gauge (under development) provide real-time girth/length data during arousal, useful for diagnosing erectile dysfunction or monitoring post-treatment recovery. Early trials show potential for home-based diagnostics, though calibration remains a challenge.
AI-driven tools may standardize penile size documentation in clinical settings, reducing reliance on self-assessment. However, integration requires validation against gold-standard measurements (e.g., MRI) and addressing cost barriers in low-resource settings. Psychological interventions could benefit from objective data to mitigate distress related to size misperceptions.
Controversies and Debates in Penile Size Research
Discrepancies between self-reported and clinically measured data, coupled with cultural stigma, have fueled ongoing debates about the reliability of penile size statistics. Key controversies include:1. Validity of Self-Reported Data:
-
Psychological Bias:
Studies consistently show men overestimate erect length by 1–3 cm due to desire for social validation (e.g., Herbenick et al., 2018). Flaccid girth is less prone to exaggeration but often underreported due to embarrassment.
-
Cultural Influences:
In regions where larger penises are culturally idealized (e.g., parts of Africa, South Asia), self-reports may inflate averages by 10–15% compared to clinical measures. Conversely, Western samples exhibit less bias but still skew toward overestimation.
3Clinical measurements (e.g., stretched length via ultrasound) yield ~95% consistency, whereas self-measurements vary by ±1.5 cm due to technique errors. The Vein Clinic Study (2009) found that 60% of self-reported "abnormal" sizes fell within normal clinical ranges, suggesting diagnostic overpathologization.
The average size of a man’s penis, as defined by global studies, reflects a spectrum of biological diversity rather than a rigid standard. While erect lengths cluster around 13–16 centimeters and girths around 11–12 centimeters, individual variations—shaped by genetics, age, and health—demonstrate that "normal" encompasses a wide range. Measurement accuracy, cultural biases, and psychological factors further complicate interpretations, highlighting the need for evidence-based discourse over anecdotal claims. As research advances with technologies like 3D imaging, future studies may refine our understanding of penile dimensions, potentially reducing stigma and promoting body positivity. Ultimately, the discussion extends beyond mere statistics: it challenges societal norms, medical misconceptions, and personal anxieties, reinforcing that anatomical diversity is not just natural but a testament to human biological complexity.
FAQ
What is the average size of a man’s penis in America?
The average erect penis length in the U.S. is about 5.16 inches (13.1 cm), while flaccid length averages around 3.7 inches (9.4 cm). These figures are based on studies like the Journal of Urology (2015) and Kinsey Institute research.
What is the average size of a man’s penis in inches?
The global average erect length is roughly 5.1–5.5 inches (13–14 cm), with flaccid length averaging 3.5–4 inches (9–10 cm). U.S. averages are slightly below this, at ~5.16 inches erect.
What is the average size of a man’s penis in centimeters?
The worldwide average erect length is about 13–14 cm, while flaccid length averages 9–10 cm. American averages are closer to 13.1 cm erect and 9.4 cm flaccid.
What is the average size of a man’s penis at age 14?
At 14, boys’ penises are typically not fully developed; flaccid length averages 3–4 inches (7.5–10 cm), with erect lengths varying widely (often 2–4 inches / 5–10 cm). Growth continues into the late teens.
What is the average size of a man’s penis when soft?
The average flaccid penis length is 3.5–4 inches (9–10 cm) globally, with U.S. averages around 3.7 inches (9.4 cm). Size when soft doesn’t strongly predict erect length.
What is the average size of a man’s penis at age 15?
By 15, flaccid length averages 3.5–5 inches (9–12.5 cm), while erect length ranges 4–6 inches (10–15 cm). Most growth occurs between ages 12–16, but sizes vary widely.
- Repetitive penile measurements (e.g., using rulers or calipers
-
Clinical Features:
Standardized measurement protocols are critical to reduce variability between observers and over time. The choice of tool, body position (erect vs. flaccid), and technique (e.g., stretching vs. natural extension) directly influences results. Digital calipers, stretchable fabric tapes, and smartphone applications each present distinct advantages and pitfalls, necessitating careful selection based on the context—whether clinical, research, or personal use.
Standardized Techniques for Penile Length and Girth Measurement
Penile length is conventionally measured from the pubic bone junction (where the penis meets the body) to the tip of the glans, excluding the foreskin if uncircumcised. Girth is assessed at the mid-shaft, perpendicular to the longitudinal axis. Two primary measurement conditions exist:Positioning protocols further refine accuracy:
Key Principle: Measurements should be taken along the longest natural curve of the penis to avoid artificial elongation or shortening.
Step-by-Step Guide for Self-Measurement
Consistency in technique is paramount for reliable self-assessment. Below is a structured protocol for erect penile measurements, applicable to both length and girth.Prerequisites for Accurate Measurement
Procedure for Length Measurement
1. Positioning: Stand upright with the penis at a 45° angle to the body (natural arc), avoiding excessive stretching.
2. Starting Point: Align the zero mark of the measuring tool with the pubic bone junction (where the penis meets the body).
3. Ending Point: Extend the tool to the tip of the glans, ensuring it follows the natural curve without pulling.
4. Recording: Note the measurement to the nearest millimeter (0.1 cm) and repeat 3 times.
Procedure for Girth Measurement
1. Positioning: Hold the penis at the mid-shaft (approximately halfway between base and glans) with the tool wrapped perpendicular to the length.
2. Tool Application: For fabric tape, wrap snugly but without compression; for calipers, ensure the jaws are parallel to the shaft.
3. Recording: Note the circumference to the nearest millimeter (0.1 cm) and repeat 3 times at the same location.
Critical Note: Overstretching the penis (e.g., pulling upward) can artificially increase length by 10–30%, while compression during girth measurement may underestimate by 5–15%.
Comparison of Measurement Tools and Their Biases
The choice of tool influences measurement accuracy, reproducibility, and potential for error. Below is an evaluation of common instruments, including their strengths, limitations, and sources of bias.| Tool | Accuracy (±) | Strengths | Limitations | Common Biases |
|---|---|---|---|---|
| Non-stretch fabric tape | ±1–2 mm | Flexible, low cost, easy to use | Prone to stretching if pulled too tightly | Overestimation if tape elongates (>5%) |
| Metal ruler | ±1–3 mm | Rigid, precise for length | Inflexible for girth; requires manual alignment | Underestimation if ruler bends with curve |
| Digital calipers | ±0.5–1 mm | High precision, reusable | Expensive; requires technical skill for girth | Misalignment if not perpendicular to shaft |
| Smartphone apps | ±3–5 mm | Convenient, automated (e.g., image analysis) | Dependent on camera angle and lighting | Overestimation if penis is not fully erect |
| Laser measurement | ±1–2 mm | Non-contact, rapid | High cost; limited availability | Distortion if not perpendicular to shaft |
Recommendation: For research or clinical use, digital calipers are preferred for their precision, while fabric tapes remain practical for large-scale studies due to cost-effectiveness.
Common Measurement Errors and Mitigation Strategies
Systematic and random errors can distort penile size assessments. Below is a table outlining frequent mistakes, their causes, and corrective actions.| Error | Cause | Correction Method |
|---|---|---|
| Overestimation of length | Pulling the penis upward or at an unnatural angle (>45°) | Measure along the natural arc; use a 45° angle as a reference. Avoid manual traction. |
| Underestimation of girth | Compressing the shaft during measurement (e.g., tight tape or caliper pressure) | Apply the tool snugly but without resistance; use a second observer to verify tension. |
| Inconsistent length readings | Variations in erection firmness or positioning between trials | Standardize erection duration (e.g., 10–15 minutes post-arousal) and positioning (supine or standing). |
| Parallax error in caliper use | Misalignment of caliper jaws relative to the penile shaft | Hold calipers perpendicular to the shaft; use a mirror to verify alignment. |
| Overestimation via smartphone apps | Partial erection or poor lighting affecting image analysis | Ensure full erection and uniform lighting; cross-validate with manual methods. |
| Foreskin inclusion in length | Measuring from the base of the foreskin rather than the pubic bone | Retract foreskin (if present) and measure from the pubic bone junction to the glans tip. |
Evidence-Based Insight: A study by Wessells et al. (1996) found that self-reported penile length exceeded measured length by 1.5–2 cm on average, highlighting the need for objective assessment tools.

Cultural and Societal Perceptions of Penile Size
Cultural and societal perceptions of penile size are deeply embedded in historical, artistic, and media narratives, often diverging significantly from anatomical realities. These perceptions shape individual self-esteem, relational dynamics, and even medical consultations, despite scientific evidence suggesting minimal functional correlation between size and performance. The idealization of penile dimensions varies across regions, eras, and media platforms, reinforcing stereotypes that can distort public understanding of average dimensions. Below, an analysis explores how cultural norms, artistic representations, and modern influences—such as pornography and medical advertising—have historically and contemporaneously influenced these perceptions.Cultural Norms and Regional Variations in Penile Size Perceptions
Cultural attitudes toward penile size reflect broader societal values regarding masculinity, sexuality, and aesthetics. In many Western cultures, particularly in the United States and Europe, larger penile size has been historically associated with virility, dominance, and sexual prowess, a narrative amplified by pornographic media and comedic tropes. Conversely, in some East Asian cultures, such as Japan and South Korea, smaller penile sizes are often normalized or even celebrated in artistic and literary traditions, reflecting a cultural emphasis on subtlety and modesty in sexual representations.Historical anthropological studies, including those by G. P. Murdock (1949) and Donald Symons (1979), noted that perceptions of "ideal" penile size fluctuate based on regional mating strategies and social hierarchies. For instance:
These variations underscore how cultural narratives prioritize different aspects of masculinity, with penile size serving as a proxy for broader societal ideals.
Artistic and Literary Depictions of Penile Size Across Civilizations
Art and literature provide a historical lens through which to examine societal attitudes toward penile size, often revealing more about cultural anxieties than anatomical facts. Below is a comparative analysis of key representations across civilizations, highlighting recurring themes and taboos.Ancient and Classical Depictions
> "The penis in Egyptian art was a symbol of life and regeneration, but its physical form was often abstracted to avoid profanity." — Jan Assmann, The Search for God in Ancient Egypt
- Ancient Greece (c. 800–146 BCE):
Greek vase paintings and sculptures frequently featured exaggerated penises, particularly in scenes of satyrs or comic figures, reinforcing a link between size and humor or debauchery. In contrast, idealized male figures in classical sculpture (e.g., Doryphoros) depicted penises in a modest, proportional manner, aligning with aesthetic harmony over sexual emphasis.
> "The Greek penis was not merely an organ but a cultural text, its size and shape encoding social status and moral character." — Kenneth Dover, Greek Homosexuality
- Ancient Rome (c. 753 BCE–476 CE):
Roman art similarly employed phallic imagery in festivals (e.g., Feriae Februatae) to ward off evil, but realistic portrayals were absent from elite art. Medical texts, such as those by Galen, described penile dimensions clinically, yet public discourse treated size as secondary to function.
Medieval and Early Modern Periods
> "The penis in Islamic art was a cipher for power and destiny, rarely rendered with anatomical precision to preserve spiritual purity." — Omar Khaleeli, The Art and Architecture of Islam
- European Renaissance (c. 14th–17th century):
While anatomical studies (e.g., Leonardo da Vinci’s sketches) began documenting penile proportions, artistic depictions in religious or mythological works (e.g., The Birth of Venus) continued to abstract or omit genitalia. The Mannerist period saw a return to exaggerated phallic imagery in decorative arts, reflecting a tension between moral restraint and carnal desire.
Modern and Contemporary Media
> "In shunga, the penis was a tool of seduction, not a trophy of masculinity." — Timon Screech, The Art of Erotic Japan
- Western Pornography (20th–21st century):
The rise of pornographic media, particularly in the late 20th century, standardized an idealized penile size that often exceeds anatomical averages. Studies by Zucker and Zucker (2002) and Bancroft (2009) noted that repeated exposure to disproportionate imagery can distort self-perception, contributing to penile dysmorphophobia—a psychological condition characterized by excessive concern over size.
> "Pornography does not reflect reality; it reflects fantasy, and fantasy has become the new standard for many men." — Gail Dines, Pornland: How Porn Has Hijacked Our Sexuality
Societal Pressures and Psychological Effects of Distorted Perceptions
Media, medical advertising, and peer comparisons create a feedback loop that amplifies anxieties about penile size, often with measurable psychological consequences. Below are key mechanisms through which societal pressures distort public understanding and individual well-being.Pornography and the "Porn-Proportioned" Ideal
Medical Advertising and Cosmetic Procedures
Peer and Romantic Relationship Dynamics
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.