| Underlying Mechanism |
Single reentrant circuit (e.g., CTI-dependent). |
Multiple reentrant wavelets or focal triggers (e.g

Symptoms, Triggers, and Patient Experiences in Heart Flutter
Heart flutter, a subtype of supraventricular tachycardia (SVT), manifests through a constellation of subjective and objective symptoms that vary widely among individuals. While some patients experience transient, benign episodes, others endure chronic or recurrent flutters that significantly impair daily functioning. Understanding these symptoms—ranging from physical sensations to emotional distress—and identifying their triggers is critical for accurate diagnosis, patient education, and tailored management strategies. This section explores the spectrum of patient-reported experiences, physiological mechanisms underlying common triggers, and the differential impact of acute versus chronic flutter episodes on quality of life.
Subjective Symptoms Reported by Patients
Patients describe heart flutter through a multifaceted lens, with symptoms often overlapping between physical discomfort, emotional distress, and cognitive impairment. The following categories encapsulate the most frequently reported experiences, though individual variability remains pronounced.
Physical Symptoms
Palpitations: A rapid, fluttering, or pounding sensation in the chest, often described as "heart racing" or "skipping beats."
Chest discomfort: Mild to moderate pressure, tightness, or unease, distinct from angina but potentially misinterpreted as cardiac ischemia.
Shortness of breath: Dyspnea on exertion or at rest, sometimes accompanied by a choking sensation.
Lightheadedness or syncope: Transient loss of consciousness or near-fainting, particularly in patients with compromised cardiac output.
Fatigue: Persistent exhaustion, even after minimal physical activity, linked to chronic oxygen desaturation or autonomic dysfunction.Emotional and Psychological Symptoms
Anxiety or panic: Heightened fear of imminent cardiac arrest or stroke, exacerbating sympathetic overactivity.
Irritability or restlessness: Difficulty concentrating due to autonomic arousal or sleep disruption from nocturnal flutters.
Depression: Long-term emotional burden from chronic symptoms, particularly in patients with undiagnosed or poorly managed flutter.
Fear of recurrence: Anticipatory anxiety before triggers (e.g., caffeine, stress), leading to avoidance behaviors.Cognitive Symptoms
Brain fog: Impaired memory, slowed processing speed, or difficulty focusing, attributed to reduced cerebral perfusion during episodes.
Vertigo or spatial disorientation: Misinterpretation of vestibular signals due to arrhythmia-induced hypotension.
Auditory or visual disturbances: Rare but reported, including tinnitus or tunnel vision during severe episodes.
Symptom severity correlates with flutter duration, ventricular rate, and underlying cardiac health. For instance, atrial flutter with rapid ventricular response (≥150 bpm) may provoke more pronounced hemodynamic instability than paroxysmal atrial flutter with preserved atrioventricular conduction.
Common Triggers and Physiological Pathways
Heart flutter episodes are often precipitated by modifiable and non-modifiable factors, each acting through distinct physiological pathways. Below is a structured overview of triggers, their mechanistic links to arrhythmogenesis, and evidence-based mitigation strategies.
Physiological Mechanisms Underlying Triggers
Autonomic imbalance: Sympathetic overactivity (e.g., stress, exercise) enhances atrial excitability via catecholamine release, while parasympathetic withdrawal (e.g., sleep apnea) reduces vagal tone, promoting reentrant circuits.
Electrolyte disturbances: Hypokalemia or hypomagnesemia prolong repolarization, increasing dispersion of refractoriness and triggering flutter waves.
Structural remodeling: Chronic conditions like hypertension or heart failure induce atrial fibrosis, creating substrates for macro-reentrant circuits.
Drug interactions: Proarrhythmic effects of medications (e.g., digoxin toxicity, sympathomimetics) or withdrawal (e.g., beta-blocker cessation) disrupt normal conduction.
| Trigger |
Mechanism |
Mitigation Strategies |
|---|
| Caffeine (coffee, tea, energy drinks) |
Stimulates β-adrenergic receptors, increasing automaticity and triggered activity in atrial foci or reentrant pathways. |
- Limit intake to ≤200 mg/day (e.g., 1–2 cups of coffee).
- Avoid consumption 4–6 hours before bedtime.
- Switch to decaffeinated alternatives if symptoms persist.
|
| Alcohol (binge drinking, excessive intake) |
Acute intoxication prolongs QT interval via ethanol metabolites, while chronic use induces atrial fibrosis and autonomic dysfunction. |
- Moderate consumption: ≤1 drink/day for women, ≤2 for men.
- Avoid alcohol 24 hours pre- and post-diagnostic procedures (e.g., ablation).
- Hydration and electrolyte monitoring during heavy use.
|
| Stress or anxiety |
Elevated cortisol and norepinephrine levels enhance atrial depolarization and reduce refractory periods, facilitating reentry. |
- Stress-reduction techniques: Deep breathing, mindfulness, or biofeedback.
- Pharmacological: Short-term beta-blockers (e.g., metoprolol 25–50 mg PRN) or anxiolytics (e.g., lorazepam 0.5–1 mg).
- Behavioral therapy (CBT) for chronic stress-related flutters.
|
| Dehydration or electrolyte imbalances |
Hypokalemia (<3.5 mEq/L) or hypomagnesemia (<1.5 mg/dL) increase action potential duration, promoting afterdepolarizations. |
- Oral rehydration with electrolyte-rich fluids (e.g., coconut water, sports drinks).
- Dietary supplementation: Bananas (potassium), nuts/seeds (magnesium), or IV replacement in severe cases.
- Regular monitoring in patients on diuretics or with renal dysfunction.
|
| Overexertion or hyperthyroidism |
Increased metabolic demand or thyroid hormone excess (e.g., elevated T3/T4) upregulate calcium currents, enhancing atrial excitability. |
- Gradual exercise progression with heart rate monitoring.
- Thyroid function testing (TSH, free T4) and treatment if hyperthyroidism is confirmed.
- Avoid intense workouts within 2 hours of meals.
|
| Sleep deprivation |
Reduced parasympathetic tone and elevated sympathetic activity during fragmented sleep lower the flutter threshold. |
- Maintain consistent sleep schedule (7–9 hours/night).
- Address obstructive sleep apnea with CPAP if diagnosed.
- Avoid screens or stimulating activities 1 hour before bedtime.
|
Real-World Patient Scenarios and Emotional Impact
The subjective experience of heart flutter often transcends physical symptoms, shaping patient behavior, social interactions, and mental health. Below are illustrative vignettes highlighting the urgency, fear, and adaptive strategies employed by individuals during episodes.
Scenario 1: Acute Flutter During a High-Stakes Presentation
A 32-year-old financial analyst notices a sudden "thumping" in her chest as she prepares to deliver a quarterly report to executives. Her palms sweat, her vision blurs briefly, and she grip the podium to steady herself. Though she completes the presentation, she later describes the episode as "like my heart was trying to escape my ribcage." Post-event, she avoids caffeine and practices diaphragmatic breathing before public speaking.Key Features:
Trigger: Stress-induced catecholamine surge.
Symptoms: Palpitations, lightheadedness, anxiety.
Outcome: Temporary avoidance of triggers; self-management with relaxation techniques.
Scenario 2: Chronic Flutter and Quality of Life Decline
*A 58-year-old retired teacher experiences daily flutters, waking 2–3 times nightly with a sensation of "drowning" in her chest. Over 6 months, she develops insomnia, avoids social gatherings, and requires frequent ER visits for IV diltiazem. Her primary care physician notes "palpable fear" during appointments, with the patient stating, "I don’t know if I
Accurate diagnosis of heart flutter requires a systematic approach integrating electrocardiographic analysis, imaging, and specialized testing to differentiate between atrial and ventricular forms while ruling out structural or metabolic confounders. The diagnostic pathway relies on high-sensitivity tools to capture transient arrhythmias, assess cardiac anatomy, and evaluate hemodynamic stability. Below is a structured guide outlining the stepwise evaluation, distinguishing ECG patterns, echocardiographic findings, and protocols for advanced testing, including decision points for further investigation.
Stepwise Diagnostic Evaluation for Heart Flutter
The diagnosis of heart flutter begins with a thorough clinical assessment, followed by targeted investigations to confirm the arrhythmia and exclude underlying cardiac pathology. The following steps outline the sequential diagnostic approach:- Clinical History and Physical Examination
A detailed patient history focuses on symptom triggers (e.g., caffeine, stress, or sleep deprivation), duration, and associated symptoms such as palpitations, syncope, or dyspnea. Physical examination assesses for signs of hemodynamic compromise (e.g., hypotension, irregular pulse) or structural heart disease (e.g., murmurs, peripheral edema). Blood pressure and pulse oximetry are recorded to evaluate acute instability. - Initial Electrocardiogram (ECG) Recording
A 12-lead ECG is the first-line diagnostic tool, capturing heart rhythm at rest. If flutter is suspected but not captured, rhythm strip monitoring or portable ECG devices (e.g., handheld monitors) may be employed during symptom episodes. Key considerations:
Rate and Regularity: Flutter typically presents with a regular, rapid ventricular response (often 150–250 bpm in atrial flutter, 120–200 bpm in ventricular flutter).
P-Wave Analysis: Absent or replaced by flutter waves (F-waves) in atrial flutter, or wide QRS complexes in ventricular flutter.- Ambulatory Monitoring (Holter or Event Monitor)
For intermittent symptoms, 24–48-hour Holter monitoring or external loop recorders (worn for weeks) are used to capture episodes. Implantable loop recorders (ILRs) are reserved for patients with infrequent or unexplained symptoms. Setup protocols:
Holter Monitor: Applied with electrodes placed in standard ECG positions; patients document symptoms in a diary.
Event Monitor: Triggered manually by the patient during symptoms or automatically via rate detection.- Transtelephonic or Mobile ECG Applications
Smartphone-based ECG apps (e.g., KardiaMobile) provide rapid rhythm assessment in outpatient settings, though they lack the precision of formal ECG analysis. Limitations:
False positives/negatives due to motion artifacts or lead misplacement.
Not a replacement for formal ECG but useful for triage in primary care.- Advanced Rhythm Monitoring (Telemetry or In-Hospital ECG)
Continuous telemetry in hospitalized patients detects flutter during acute episodes, particularly in high-risk groups (e.g., post-cardiac surgery, heart failure). Indications:
Unstable patients with suspected flutter requiring immediate intervention.
Post-procedural monitoring (e.g., after catheter ablation).
Differentiating Atrial vs. Ventricular Flutter on 12-Lead ECG
The 12-lead ECG is critical for distinguishing atrial from ventricular flutter, as treatment strategies differ significantly. Below is a comparative table of wave patterns, appearance, and diagnostic value:
| Wave Type |
Appearance |
Diagnostic Value |
|---|
| Atrial Flutter (F-Waves) |
- Regular, rapid atrial activity (250–350 bpm) with sawtooth pattern in inferior leads (II, III, aVF).
- Fixed atrial-ventricular (AV) conduction ratio (e.g., 2:1, 4:1 block), resulting in a regular ventricular response.
- P-waves absent; replaced by F-waves (best visualized in V1–V3).
- QRS complexes narrow (<120 ms) unless aberrant conduction is present.
|
- Confirms atrial origin of flutter.
- Helps determine AV block pattern (e.g., 2:1 block suggests underlying heart disease).
- Guides rate control (e.g., beta-blockers, calcium channel blockers).
|
| Ventricular Flutter |
- Extremely rapid ventricular rate (200–300 bpm) with monomorphic, wide QRS complexes (>140 ms).
- No discernible P-waves; QRS complexes may exhibit fusion beats or capture beats.
- Undulating baseline resembling "sine wave" morphology in some cases.
- Hemodynamic instability often present (hypotension, altered mental status).
|
- Indicates life-threatening arrhythmia requiring immediate cardioversion.
- Distinguishes from ventricular tachycardia (VT) by absence of discrete QRS complexes (flutters appear as continuous waves).
- Suggests structural heart disease (e.g., ischemic cardiomyopathy, channelopathies).
|
Key Differentiating Features:
Atrial flutter exhibits regular, rapid F-waves with a fixed AV conduction ratio, while ventricular flutter presents as wide, undulating QRS complexes without P-waves, often associated with immediate hemodynamic collapse.
Role of Echocardiography in Ruling Out Structural Heart Disease
Echocardiography is essential for assessing cardiac anatomy, function, and potential thromboembolic risks in patients with flutter. Key findings include:- Atrial Enlargement
Left Atrial Enlargement (LAE): Common in atrial flutter due to volume overload or chronic pressure effects (e.g., mitral valve disease).
Right Atrial Enlargement (RAE): Suggests pulmonary hypertension or pulmonary embolism as underlying triggers.
Measurement Criteria:
LAE: Left atrial diameter >4 cm in parasternal long-axis view.
RAE: Right atrial area >18 cm² in apical 4-chamber view.- Thrombus Detection
Atrial Appendage Thrombus: High-risk finding in atrial flutter, increasing stroke risk. Visual clues:
Echogenic mass within the left atrial appendage (LAA) with distinct borders.
Spontaneous echo contrast (SEC) or smoke-like echoes suggesting stasis.
Transesophageal Echocardiography (TEE): Preferred for high-resolution imaging of the LAA, especially before cardioversion.- Valvular and Ventricular Abnormalities
Mitral Valve Disease: Mitral regurgitation or stenosis may contribute to atrial flutter via volume/pressure overload.
Ventricular Dysfunction: Reduced ejection fraction (EF <40%) suggests ischemic or dilated cardiomyopathy as a substrate for ventricular flutter.
Hypertrophic Cardiomyopathy (HCM): Asymmetric septal hypertrophy may predispose to ventricular arrhythmias.- Diastolic Dysfunction
Impaired relaxation (e.g., E/A ratio reversal, e’ velocity <7 cm/s) indicates diastolic heart failure, a potential trigger for atrial flutter.Protocol for Echocardiographic Evaluation: -
Transthoracic Echocardiogram (TTE):
- Standard views: Parasternal long/short-axis, apical 4-chamber, subcostal.
- Doppler assessment: Mitral inflow pattern, pulmonary artery pressure estimation.
-
Transesophageal Echocardiogram (TEE) (if TTE is inconclusive or thrombus is suspected):
- High-frequency probe (7–10 MHz) for detailed LAA visualization.
- Contrast-enhanced TEE if thrombus remains unclear.
-
St
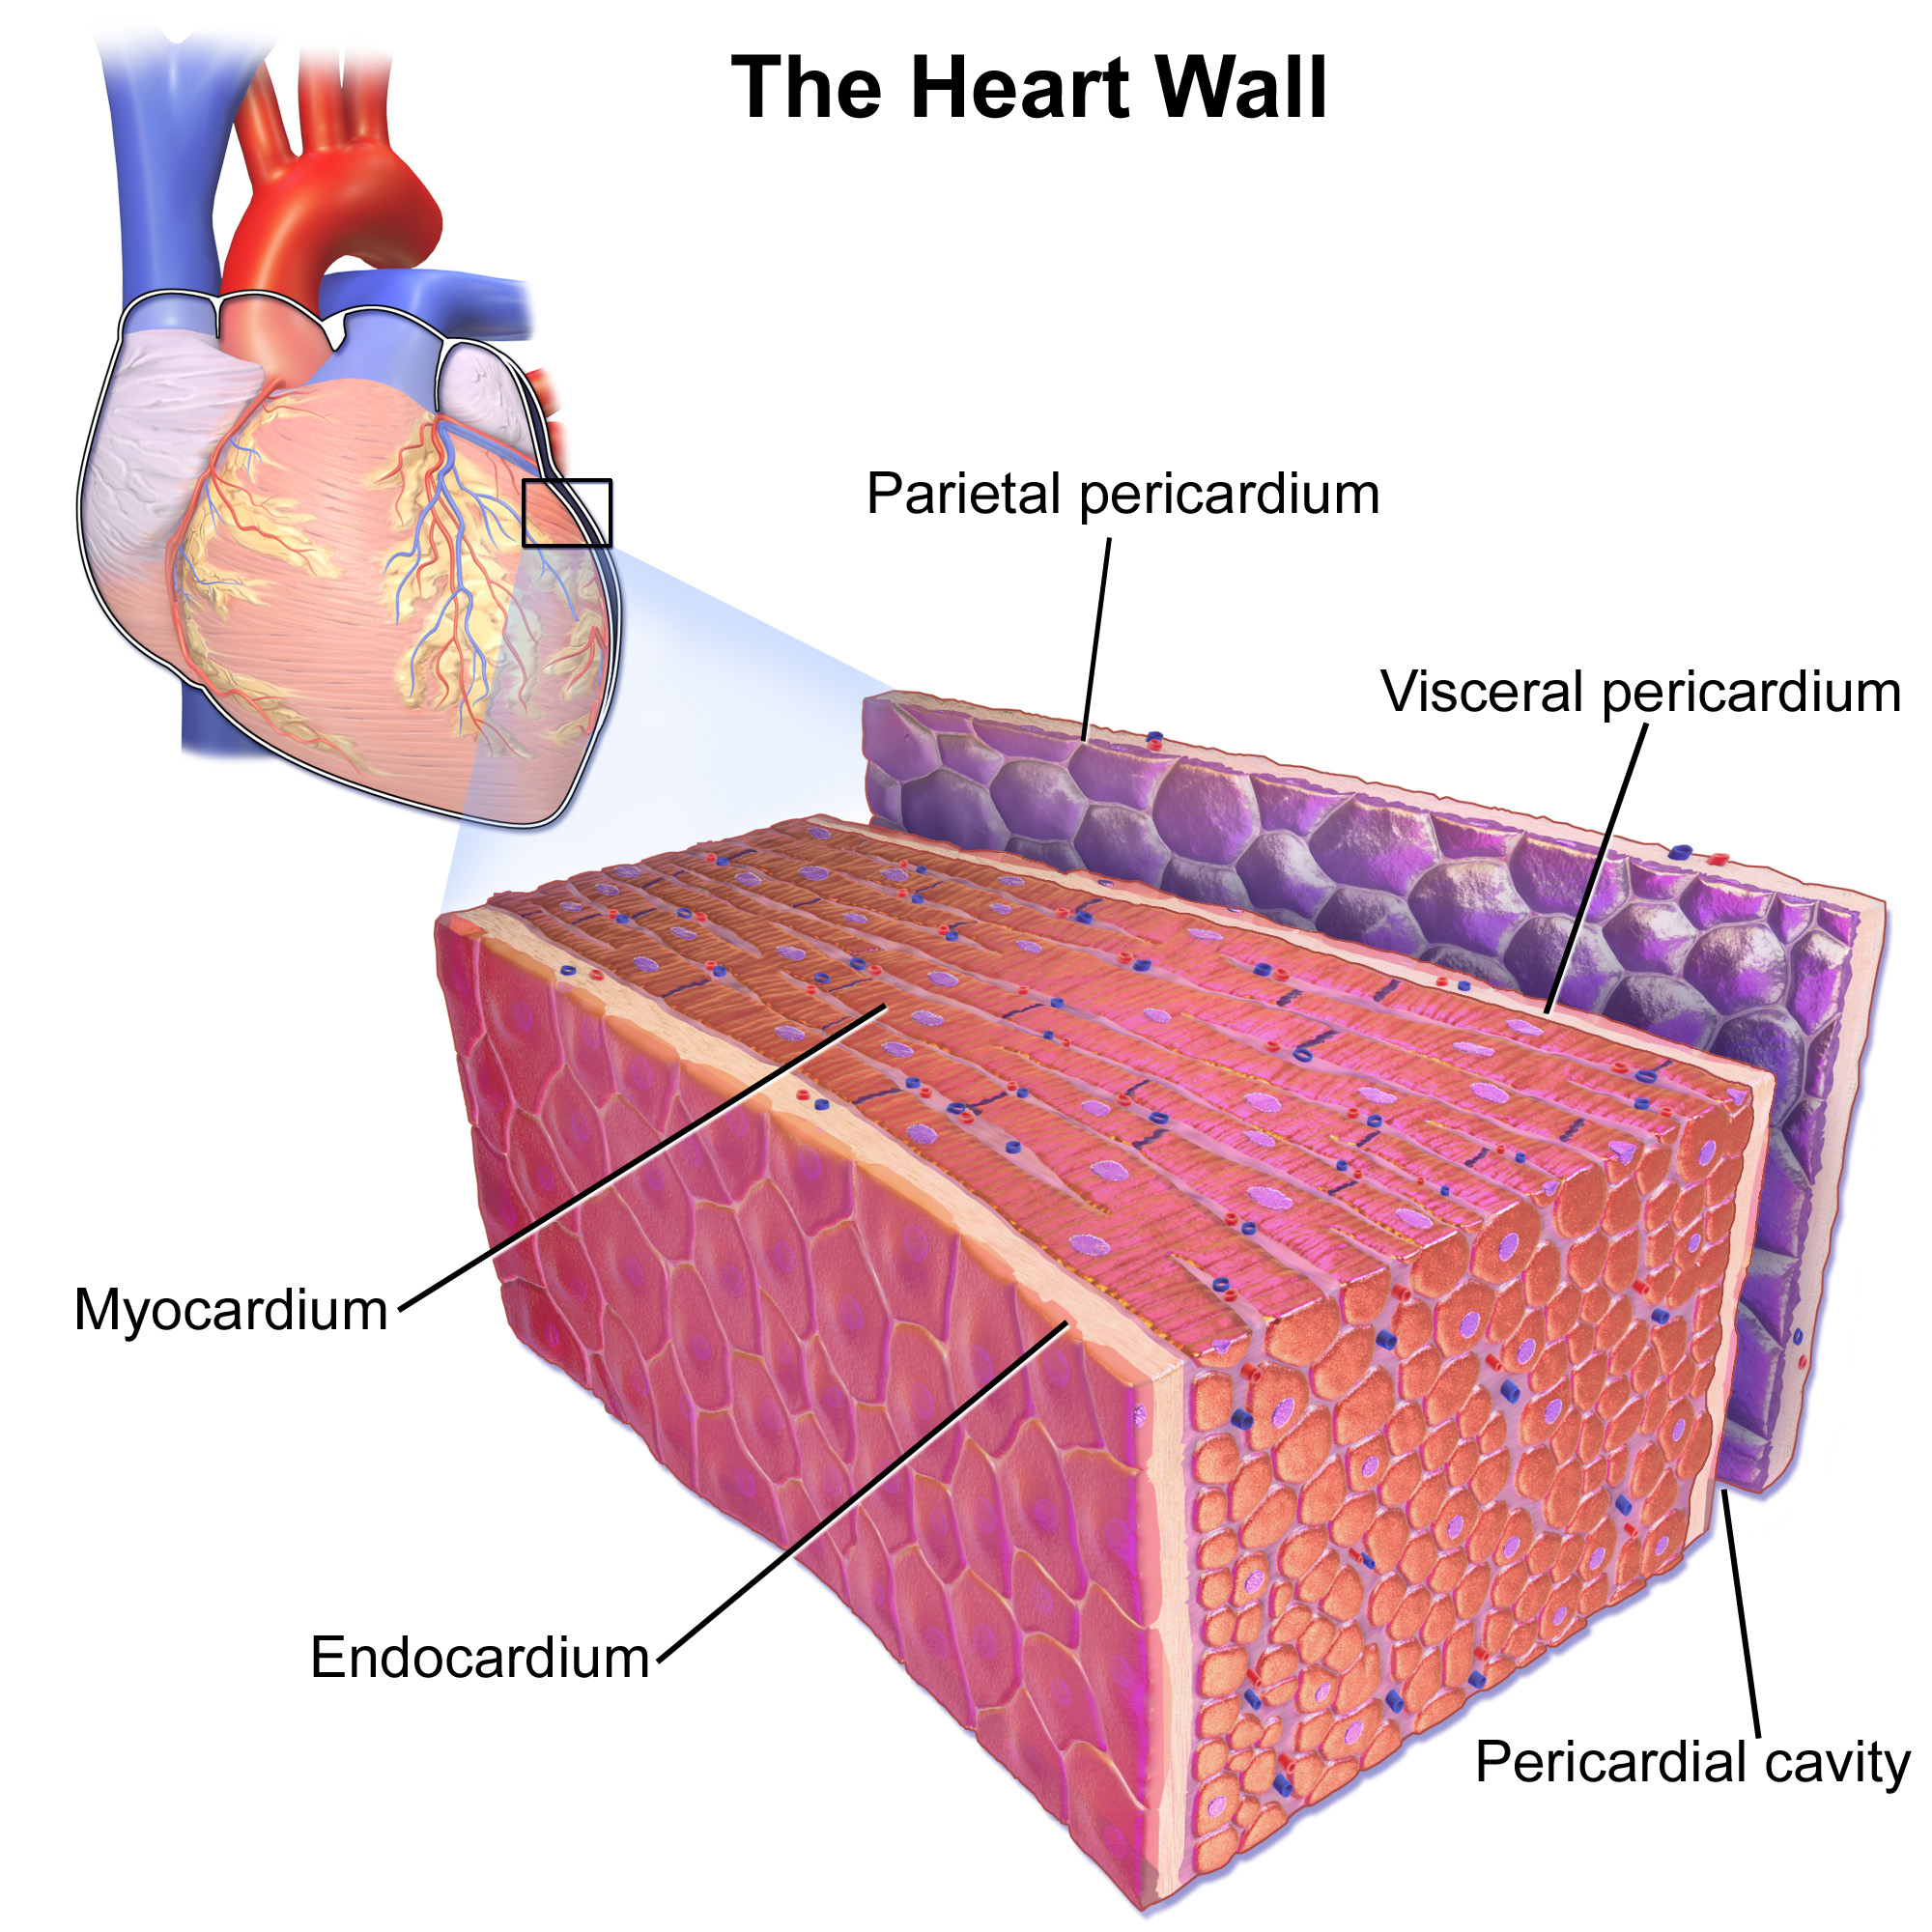
Treatment Approaches and Management Strategies for Heart Flutter
Heart flutter, particularly atrial flutter, requires a structured and individualized treatment approach that balances efficacy, safety, and patient quality of life. Management strategies range from conservative lifestyle modifications to advanced pharmacological and invasive interventions, selected based on symptom severity, flutter type, and patient comorbidities. The goal is to restore normal sinus rhythm, control ventricular rate, and prevent complications such as stroke or heart failure. Treatment escalation follows a tiered framework, progressing from non-invasive measures to more aggressive therapies when necessary.The selection of treatment modalities depends on factors including the presence of structural heart disease, patient age, and response to prior interventions. Below is a systematic overview of management strategies, including pharmacological options, procedural interventions, and post-treatment care protocols.
Tiered Treatment Framework for Heart Flutter
Treatment for heart flutter follows a stepped-care model, prioritizing the least invasive options first while reserving more aggressive interventions for refractory cases. The framework is organized into four tiers:1. Lifestyle and Non-Pharmacological Interventions
- Dietary modifications: Reduction of sodium, caffeine, and alcohol intake to minimize atrial stretch and autonomic triggers. Patients with hypertension or obesity may benefit from a heart-healthy diet (e.g., Mediterranean diet) to reduce cardiovascular risk.
- Regular physical activity: Moderate exercise (e.g., walking, swimming) improves cardiovascular fitness and may reduce arrhythmia recurrence. Avoidance of intense or competitive sports in high-risk patients (e.g., those with structural heart disease).
- Stress management: Techniques such as meditation, deep breathing, or cognitive behavioral therapy (CBT) to address autonomic nervous system imbalances contributing to flutter.
- Sleep optimization: Poor sleep quality exacerbates atrial electrical remodeling. Patients are advised to maintain a consistent sleep schedule and address sleep apnea if present.
2. Pharmacological Rate and Rhythm Control
- Rate control agents: Beta-blockers (e.g., metoprolol, bisoprolol) or calcium channel blockers (e.g., diltiazem, verapamil) are first-line for symptomatic rate control in patients with persistent flutter. Digoxin is less effective for flutter due to its limited negative chronotropic effect.
- Antiarrhythmic drugs: Used for rhythm control in patients with symptomatic flutter or those who prefer sinus rhythm restoration. Selection depends on flutter type (e.g., typical cavotricuspid isthmus-dependent flutter vs. atypical flutter).
- Anticoagulation: Oral anticoagulants (e.g., warfarin, direct oral anticoagulants [DOACs]) are prescribed for stroke prophylaxis in patients with flutter, particularly those with additional risk factors (e.g., CHA₂DS₂-VASc score ≥2).
3. Electrical Cardioversion
- Synchronized DC cardioversion: Used for acute termination of hemodynamically unstable flutter or symptomatic episodes refractory to pharmacological therapy. Success rates exceed 90% for typical flutter, with recurrence rates of 30–50% within 1 year without adjunctive therapy.
4. Invasive and Advanced Therapies
- Catheter ablation: The definitive treatment for drug-refractory or recurrent flutter, with high long-term success rates.
- Surgical ablation: Rarely employed, typically during concomitant cardiac surgery (e.g., valve repair or coronary artery bypass grafting).
- Implantable devices: Pacemakers or implantable cardioverter-defibrillators (ICDs) may be considered in patients with bradycardia-tachycardia syndrome or high-risk flutter.
Comparison of Antiarrhythmic Drugs for Heart Flutter
Antiarrhythmic drugs (AADs) are classified based on their electrophysiological effects (Vaughan Williams classification) and are selected based on flutter type, ventricular function, and patient comorbidities. Below is a comparative table of commonly used AADs for atrial flutter:
| Drug |
Mechanism |
Side Effects |
Typical Dose |
|---|
| Flecainide |
Class IC sodium channel blocker; slows conduction in accessory pathways and atrial tissue. |
Proarrhythmia (ventricular tachycardia), dizziness, blurred vision, worsening heart failure in structurally abnormal hearts. |
100–150 mg twice daily (oral). Avoid in patients with structural heart disease or ischemic cardiomyopathy. |
| Amiodarone |
Class III potassium channel blocker with additional sodium, calcium, and beta-blocking effects; prolongs action potential duration. |
Pulmonary fibrosis, thyroid dysfunction, hepatotoxicity, corneal deposits, photosensitivity, bradycardia. |
Initial: 600–800 mg/day for 1–2 weeks, then 200–400 mg/day maintenance. Loading dose may be required for acute flutter. |
| Propafenone |
Class IC sodium channel blocker with weak beta-blocking properties; similar to flecainide but with additional beta-adrenergic effects. |
Proarrhythmia, bronchospasm, metallic taste, dizziness. |
150–300 mg every 8 hours (oral). Contraindicated in severe heart failure or conduction abnormalities. |
| Sotalol |
Class III potassium channel blocker with non-selective beta-blocking effects; prolongs repolarization. |
Torsades de pointes (prolonged QT), bradycardia, fatigue, bronchospasm. |
80–160 mg twice daily (oral). Requires baseline and periodic ECG monitoring for QT prolongation. |
| Dronedarone |
Class III agent with multi-channel blocking effects (similar to amiodarone but without iodine-related toxicity). |
Heart failure exacerbation, bradycardia, liver toxicity, gastrointestinal upset. |
400 mg twice daily (oral). Contraindicated in permanent atrial fibrillation or NYHA class IV heart failure. |
Note: Drug selection must account for patient-specific factors, including renal/hepatic function, drug interactions, and prior responses. Flecainide and propafenone are preferred for typical flutter in patients without structural heart disease, while amiodarone is reserved for refractory cases or those with concomitant heart disease.
Catheter Ablation for Heart Flutter
Catheter ablation is the gold-standard curative therapy for drug-refractory or recurrent atrial flutter, particularly typical cavotricuspid isthmus-dependent flutter (CTI-dependent flutter). The procedure involves targeted radiofrequency or cryoablation of critical isthmus-dependent circuits to interrupt reentrant pathways.Anatomical Targets and Procedural Details:
- Typical (Type I) Flutter: The cavotricuspid isthmus (CTI) is the primary target, located between the tricuspid annulus and the inferior vena cava. Ablation lines are created to block the macroreentrant circuit.
- Atypical Flutter: Requires more complex mapping and ablation of non-CTI-dependent circuits, often involving the right atrium or left atrium in cases of prior ablation or structural remodeling.
Procedure Success and Complications:
- Success rates: Acute procedural success (achievement of bidirectional block) exceeds 95% for typical flutter. Long-term freedom from recurrence ranges from 70–90% at 1 year, depending on patient selection and flutter type.
- Complications: Rare but include pericardial tamponade (<1%), atrioventricular block (0.5–1%), thromboembolism (0.1–0.5%), and steam pop (with radiofrequency ablation).
Blockquote: Procedural Steps for CTI Ablation
> 1. Mapping: Electroanatomic mapping (e.g., CARTO, EnSite) identifies the CTI and confirms flutter circuit.
> 2. Ablation: Radiofrequency or cryoablation is applied along the CTI to create a linear lesion, typically 5–10 mm in width.
> 3. Verification: Bidirectional block is confirmed via pacing maneuvers to ensure circuit interruption.
> 4. Post-ablation monitoring: Patients are observed for 4–6 hours for arrhythmia recurrence or complications.
Post-Procedure Care and Follow-Up for Catheter Ablation
Patient recovery after catheter ablation requires structured monitoring and gradual resumption of activities to minimize complications and optimize outcomes. Below is a timeline-based guide for post-procedure care:First 24 Hours:
- Hospitalization: Patients are observed in a monitored
Heart flutters exemplify the delicate balance between cardiac physiology and patient experience, where rapid atrial or ventricular contractions demand both diagnostic precision and therapeutic adaptability. By understanding the distinct electrical circuits driving flutter—such as the cavotricuspid isthmus in atrial flutter—clinicians can differentiate it from fibrillation and tailor treatments from lifestyle adjustments to advanced ablation. Symptoms, though varied, often reflect the arrhythmia’s severity, underscoring the need for early intervention to preserve quality of life and prevent long-term complications. Ultimately, managing flutter requires collaboration between patients and providers, leveraging evidence-based strategies to restore rhythm, alleviate symptoms, and empower informed decision-making.
FAQ
What medical conditions or issues can heart flutters be a sign of?
Heart flutters can signal benign causes like stress, caffeine, or dehydration, but they may also indicate serious conditions such as arrhythmias (e.g., atrial fibrillation), thyroid disorders, heart valve problems, or electrolyte imbalances. If they occur frequently, are accompanied by dizziness, chest pain, or shortness of breath, seek medical evaluation promptly.
What are the common causes of heart flutters?
Heart flutters are often triggered by stress, anxiety, caffeine, nicotine, alcohol, or excessive exercise. They can also result from dehydration, electrolyte imbalances (low potassium/magnesium), hormonal changes, or underlying heart conditions like arrhythmias. Medications (e.g., decongestants, asthma drugs) or medical issues like thyroid disorders may also play a role.
What is the medical term for heart flutters?
Heart flutters are typically referred to as palpitations or arrhythmias (when irregular). If they involve rapid, chaotic contractions, they may be called atrial flutter (a specific type of arrhythmia) or premature beats (e.g., premature atrial contractions or PVCs).
What does it mean when you feel chest flutters?
Chest flutters usually describe a sensation of rapid, irregular, or "skipped" heartbeats in the chest, often due to temporary electrical misfires in the heart. While often harmless (caused by stress, diet, or lifestyle), they can sometimes reflect underlying heart rhythm disorders or other medical conditions requiring assessment.
What are heart palpitations, and how do they feel?
Heart palpitations are sensations of a racing, pounding, fluttering, or "out-of-sync" heartbeat, often felt in the chest or throat. They may feel like the heart is skipping beats, beating too hard, or fluttering like a "fluttering in the chest." The intensity can vary from mild to alarming, depending on the cause.
What are the most common causes of heart palpitations?
Common causes include stress, anxiety, caffeine, nicotine, alcohol, or excessive exercise. Medical triggers may involve thyroid disorders, anemia, low blood pressure, electrolyte imbalances, or heart conditions like arrhythmias. Certain medications (e.g., decongestants, asthma drugs) or hormonal changes can also provoke palpitations.
|
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.