What Will A Pediatrician Do During Child Care Visits
Table of Contents
- Initial Assessment & Medical History Review in Pediatric Care
- Step-by-Step Process of the Initial Pediatric Assessment
- Medical History Review and Cross-Referencing
- Red-Flag Symptoms Prioritized in Initial Visits
- Diagnostic Procedures & Testing in Pediatric Care
- Common Diagnostic Tests for Pediatric Conditions
- Interpretation of Lab Results in Pediatric Patients
- Ordering and Reviewing Imaging Studies in Children
- Non-Invasive Diagnostic Methods in Pediatrics
- Treatment Plans & Medication Management in Pediatric Care
- Principles of Pediatric Medication Prescription
- Side Effect Monitoring and Age-Specific Considerations
- Treatment Protocols for Acute Pediatric Conditions
- Treatment Protocols for Chronic Pediatric Illnesses
- Age-S Developmental & Behavioral Interventions in Pediatric Care Pediatricians play a critical role in identifying, monitoring, and intervening in developmental and behavioral challenges in children. Early detection of delays—whether in speech, motor skills, cognition, or socioemotional functioning—enables timely referrals to specialists and targeted interventions. Behavioral concerns, such as ADHD, anxiety, or disruptive behaviors, require a structured approach combining evidence-based strategies, parent education, and multidisciplinary collaboration. Pediatricians serve as the primary coordinators, ensuring continuity of care while documenting progress through standardized tools to guide clinical decisions and family support. Developmental and behavioral assessments are foundational to pediatric care, integrating screening, diagnosis, and intervention planning. Standardized tools, parent-reported milestones, and observational data form the basis for identifying deviations from normative trajectories. When delays or concerns are detected, pediatricians initiate referrals to early intervention programs, therapists, or psychologists, while also providing immediate guidance to families on age-appropriate expectations and behavioral management techniques. Screening Tools for Developmental Delays and Referral Processes
- Strategies for Addressing Behavioral Concerns
- Coordination of Care with Specialists and Multidisciplinary Teams
- Preventive Care & Parent Education in Pediatric Practice
- Age-Specific Preventive Services Checklist
- Parent Education on Child Safety: Evidence-Based Guidelines
- Emergency & Urgent Care Protocols in Pediatric Practice
- Triage Criteria for Pediatric Emergencies
- Stabilization Techniques in Pediatric Emergencies
- Communication with Emergency Services
- Comparison of Common Pediatric Emergencies and Immediate Interventions
- FAQ
- What can a pediatrician do to help a child with an ingrown toenail?
- What treatments or advice will a pediatrician give for a child with constipation?
- How does a pediatrician treat a child who has diarrhea?
- What does a pediatrician recommend for treating diaper rash in babies?
- What will a pediatrician do if a baby has reflux?
- What treatments does a pediatrician use for croup in children?
Pediatricians play a critical role in safeguarding children’s health from infancy through adolescence by integrating clinical expertise with preventive care and family-centered support. Their approach goes beyond symptom management, blending diagnostic precision with developmental monitoring to address acute illnesses, chronic conditions, and behavioral challenges. From the first well-baby check to adolescent health screenings, pediatricians employ evidence-based protocols to ensure timely interventions, educate caregivers, and foster long-term wellness.
The scope of a pediatrician’s responsibilities spans medical assessments, diagnostic testing, and tailored treatment plans, all while prioritizing age-specific safety and communication strategies. Their work extends into emergency protocols, developmental screenings, and proactive health education—positioning them as essential partners in a child’s growth. Understanding these processes clarifies how pediatricians balance clinical rigor with compassionate care to optimize outcomes for every patient.

Initial Assessment & Medical History Review in Pediatric Care
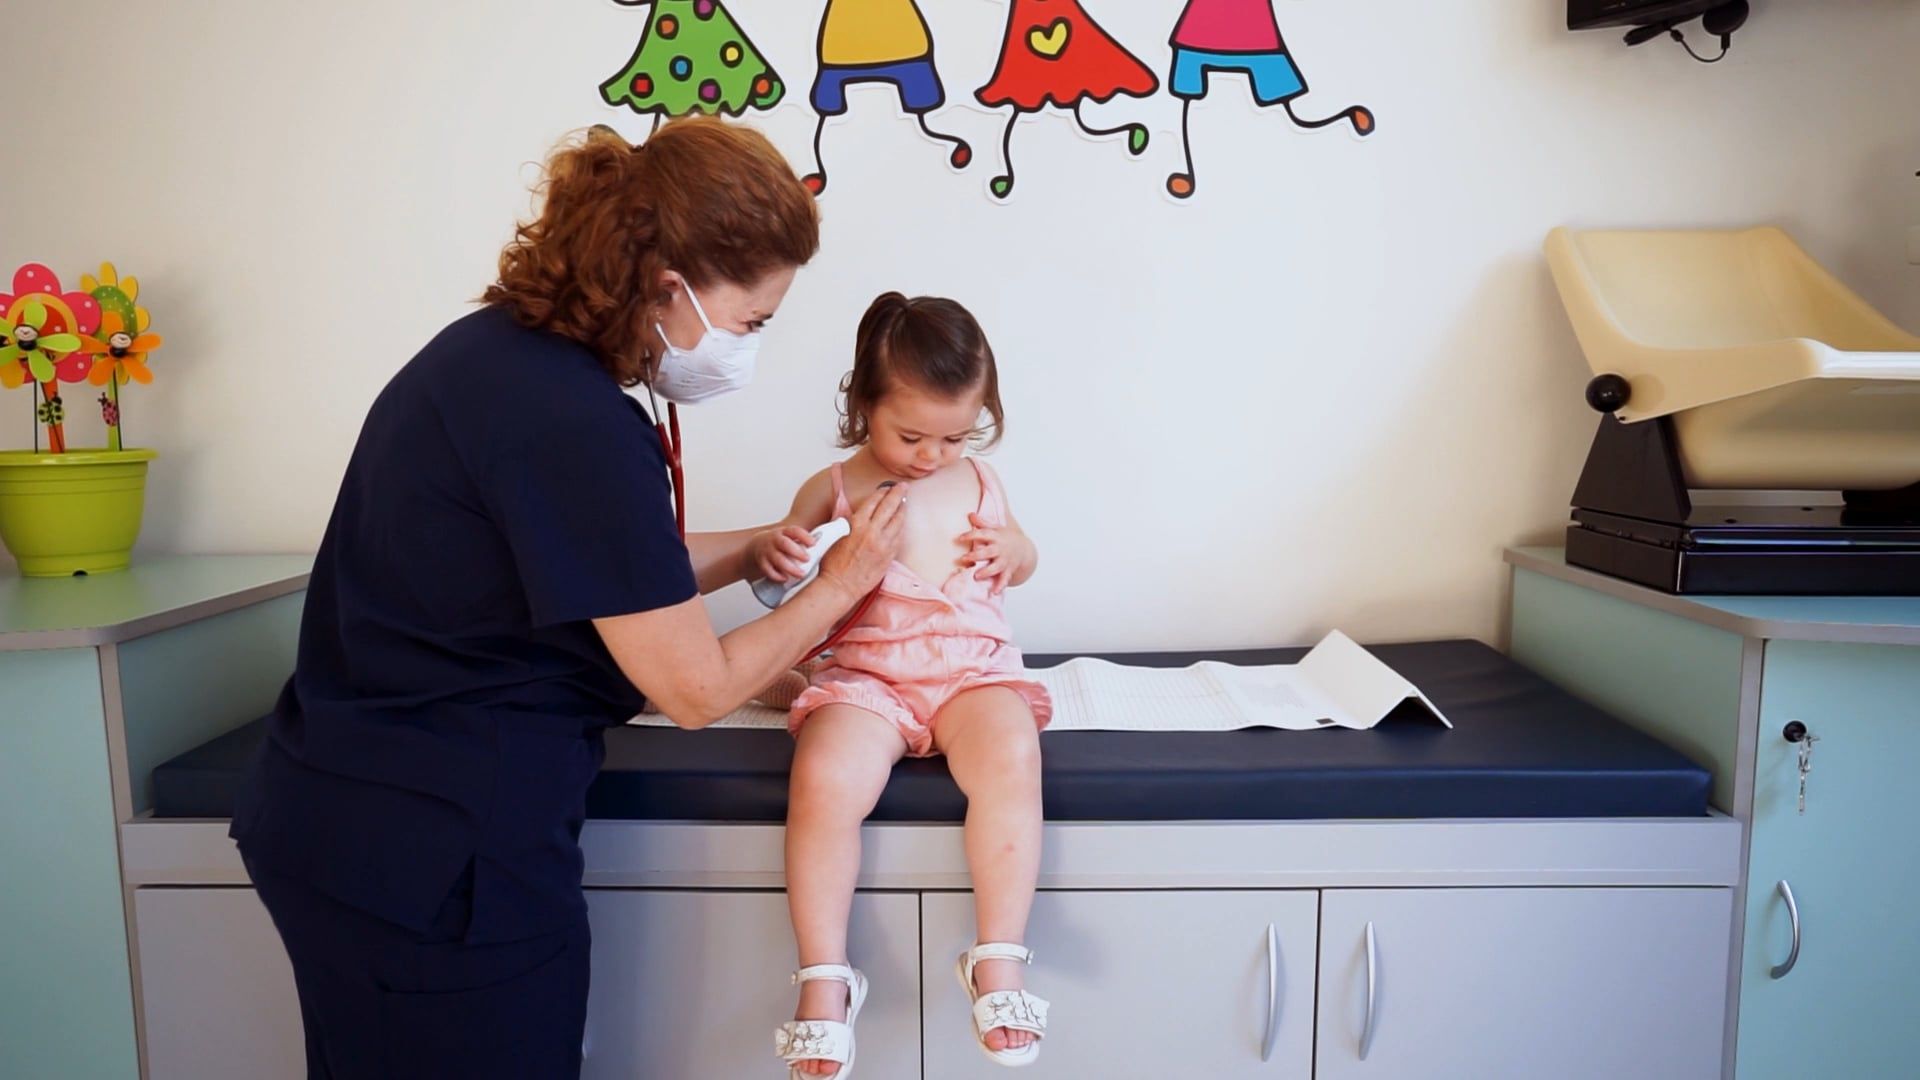
The first encounter between a pediatrician and a child establishes the foundation for ongoing medical care, emphasizing early detection of health concerns and tailored interventions. This process integrates a structured physical examination, developmental screening, and detailed medical history review, ensuring comprehensive assessment while prioritizing child-specific vulnerabilities. Pediatricians employ standardized tools—such as growth charts, developmental milestones, and clinical scoring systems—to cross-reference findings with established norms, enabling timely identification of deviations requiring intervention.Pediatric evaluations are designed to be child-centered, balancing clinical precision with age-appropriate communication to minimize distress. The assessment begins with a non-invasive observational phase, followed by systematic physical checks and parental history validation. Key components include growth parameter measurements, organ-specific examinations, and behavioral/developmental observations, all documented in a standardized format for continuity of care.
Step-by-Step Process of the Initial Pediatric Assessment
The pediatrician follows a chronological and systems-based approach, adapting techniques to the child’s age, developmental stage, and presenting symptoms. The process can be divided into three primary phases: pre-visit preparation, direct examination, and post-assessment documentation.Pre-visit Preparation
Before the physical assessment, the pediatrician reviews:
Direct Examination Techniques
The physical assessment follows a head-to-toe sequence, with modifications for infants (e.g., diaper checks, cry analysis) and older children (e.g., privacy during genital/breast exams). Common tools and methods include:
Post-Assessment Documentation
Findings are recorded in the electronic health record (EHR) or growth chart, with cross-referencing against:
Medical History Review and Cross-Referencing
A thorough medical history serves as the cornerstone of pediatric diagnostics, enabling pattern recognition and risk stratification. The pediatrician systematically collects data across five domains: personal history, family history, vaccination records, developmental milestones, and social determinants of health.Personal Medical History
Documentation includes:
Family Medical History
A three-generation pedigree is constructed to assess hereditary risks, with emphasis on:
Developmental Milestones and Screening Tools
Pediatricians use standardized screening tools to monitor progress against age-specific benchmarks. Common instruments include:
Cross-Referencing with Clinical Guidelines
Findings are aligned with:
Red-Flag Symptoms Prioritized in Initial Visits
Pediatricians employ a tiered triage system to identify time-sensitive symptoms requiring immediate intervention. Red flags are categorized by body system and severity, with escalation protocols for urgent referrals (e.g., to ER or specialist).Infectious Disease and Immunological Alerts
Neurological and Developmental Red Flags
Behavioral and Psychosocial Indicators
-
Diagnostic Procedures & Testing in Pediatric Care
Diagnostic procedures and testing form the cornerstone of accurate pediatric care, enabling pediatricians to identify, monitor, and manage childhood conditions with precision. The selection of diagnostic tools depends on clinical presentation, patient age, and suspected pathology, with an emphasis on minimizing discomfort, radiation exposure, and invasive interventions. Evidence-based criteria guide test ordering, ensuring efficiency while maintaining safety and diagnostic yield. Pediatric reference ranges for lab results differ significantly from adult values due to developmental physiology, necessitating specialized interpretation. Imaging and non-invasive modalities are tailored to pediatric anatomy and cognitive limitations, often requiring age-appropriate techniques to ensure cooperation and accuracy.
Pediatricians rely on a structured approach to diagnostic testing, balancing clinical suspicion with available resources. Common conditions such as respiratory infections, allergic disorders, and developmental delays trigger specific testing protocols, while advanced imaging and lab studies are reserved for complex or atypical presentations. Radiation safety protocols, including ALARA (As Low As Reasonably Achievable) principles, govern imaging practices to mitigate long-term risks in growing children. Non-invasive methods, such as screening tools and bedside assessments, complement lab and imaging studies to provide a comprehensive diagnostic framework.
Common Diagnostic Tests for Pediatric Conditions
Diagnostic tests are selected based on clinical guidelines, symptom specificity, and patient risk factors. For acute respiratory infections, rapid antigen tests (e.g., strep throat via rapid streptococcal antigen test) and viral panels (e.g., PCR for RSV or influenza) are first-line due to their high sensitivity and quick turnaround. Ear infections (otitis media) typically prompt pneumatic otoscopy to assess tympanic membrane mobility, followed by tympanocentesis in refractory cases for culture. Asthma diagnosis involves spirometry (with bronchodilator response testing) in children over 5–6 years, while younger patients may undergo peak expiratory flow (PEF) monitoring or bronchoprovocation testing (e.g., methacholine challenge) under specialist supervision.For urinary tract infections (UTIs), urinalysis with dipstick and urine culture are standard, with renal and bladder ultrasound indicated in infants or recurrent cases to rule out structural abnormalities. Gastrointestinal conditions such as celiac disease require serologic testing (tTG-IgA) and endoscopy with biopsy, while constipation may necessitate abdominal X-rays to assess fecal impaction. Developmental delays trigger hearing screens (audiometry), vision screening (Lea symbols or tumbling E chart), and neurodevelopmental assessments (e.g., Ages & Stages Questionnaires). Blockquote:
"Test selection in pediatrics prioritizes non-invasive, high-yield modalities first, with invasive or radiation-based tests reserved for confirmed indications to minimize harm."
Interpretation of Lab Results in Pediatric Patients
Pediatric lab reference ranges vary by age due to physiological changes, such as hemoglobin levels (higher in neonates, gradually declining to adult ranges by adolescence) and white blood cell counts (elevated in early infancy due to transient leukocytosis). Complete Blood Count (CBC) interpretations must account for:Urinalysis requires age-specific thresholds for proteinuria (nephrotic syndrome vs. orthostatic proteinuria in adolescents) and hematuria (glomerular vs. non-glomerular causes). C-reactive protein (CRP) and procalcitonin guide sepsis risk stratification, with CRP >20 mg/L suggesting bacterial infection in febrile infants. Blockquote:
"Pediatric reference ranges are dynamic; clinicians must cross-reference results with clinical context, as isolated lab abnormalities may reflect benign variations (e.g., neonatal polycythemia) or require immediate intervention (e.g., severe hypernatremia in dehydration)."
Ordering and Reviewing Imaging Studies in Children
Imaging in pediatrics adheres to ALARA principles, with X-rays limited to justified indications (e.g., pneumonia confirmation, foreign body localization, or fracture assessment). Radiation safety protocols include:Ultrasound is preferred for abdominal pain (appendicitis vs. ovarian torsion), scrotal swelling (testicular torsion), and neonatal hip dysplasia (ultrasound hip screening). CT scans are reserved for complex trauma, severe head injuries, or oncologic staging, with low-dose protocols and sedation guidelines for cooperative children. MRI is used for brain/spinal cord evaluations (e.g., suspicion of tumors or demyelinating diseases) and musculoskeletal injuries, often requiring general anesthesia for younger patients. Blockquote:
"The decision to image must balance diagnostic necessity with radiation risk; for example, a single abdominal X-ray for constipation may be justified, whereas serial imaging for abdominal pain without clear indications should be avoided."
Non-Invasive Diagnostic Methods in Pediatrics
Non-invasive techniques reduce patient stress, eliminate radiation exposure, and often provide immediate results. These methods are categorized by system and clinical application:Respiratory and Cardiovascular Screening
Audiology and Vision Assessment
Neurologic and Developmental Evaluations
Gastrointestinal and Metabolic Assessments
Musculoskeletal and Dermatologic Tools

Treatment Plans & Medication Management in Pediatric Care
Pediatricians design treatment plans and medication regimens tailored to children’s unique physiological, developmental, and psychological needs. Unlike adult care, pediatric treatment accounts for variations in body weight, organ maturation, metabolic rates, and cognitive abilities to ensure safety and efficacy. Dosage calculations, age-specific protocols, and continuous monitoring for adverse effects form the foundation of pediatric pharmacotherapy. This section explores the principles guiding medication management, compares treatment approaches across age groups, and outlines evidence-based protocols for acute and chronic conditions.Principles of Pediatric Medication Prescription
Pediatric medication dosing differs fundamentally from adult dosing due to children’s evolving organ function, particularly in the liver and kidneys, which metabolize and excrete drugs. The Clark’s Rule and Young’s Rule are historically used for dosage estimation, but modern guidelines emphasize weight-based dosing (mg/kg) or body surface area (BSA) for precision, especially in neonates and infants. Pharmacokinetics—how drugs are absorbed, distributed, metabolized, and excreted—varies by age, necessitating adjustments for:Key Dosage Formula:Pediatricians prioritize minimal effective doses to reduce toxicity risks, particularly in polypharmacy scenarios. Fixed-dose combinations (e.g., acetaminophen + dextromethorphan) are avoided unless specifically formulated for pediatrics. Extended-release formulations require caution, as children may crush tablets, altering pharmacokinetics. Intravenous (IV) therapies are preferred for critically ill infants due to unreliable oral absorption.
Weight-based dosing = (Child’s weight in kg × Adult dose per kg) = Pediatric dose.
Example: For amoxicillin (40 mg/kg/day for otitis media), a 10 kg child receives 400 mg/day divided into 2 doses.
Side Effect Monitoring and Age-Specific Considerations
Children exhibit unique adverse drug reactions (ADRs) due to developmental vulnerabilities. Infants are at higher risk for respiratory depression (e.g., opioids), electrolyte imbalances (e.g., diuretics), and neurological toxicity (e.g., antiepileptics). Adolescents may experience psychiatric side effects (e.g., stimulants for ADHD) or endocrine disruptions (e.g., corticosteroids). Monitoring strategies include:Red Flags for Pediatric ADRs:Cultural and socioeconomic factors influence adherence; pediatricians employ visual aids (e.g., pill charts) and parental education to mitigate non-compliance. Language barriers are addressed via interpreters or translated medication guides. Allergic histories are meticulously documented, as children are prone to cross-reactivity (e.g., penicillin-allergic patients may react to cephalosporins).
Infants: Jaundice (e.g., ceftriaxone-induced biliary sludging), seizures (e.g., theophylline toxicity). Toddlers: Diarrhea (e.g., antibiotics disrupting gut flora), rash (e.g., ampicillin-induced hypersensitivity). Adolescents: Mood swings (e.g., isotretinoin for acne), hyperglycemia (e.g., steroids).
Treatment Protocols for Acute Pediatric Conditions
Acute illnesses in children often require time-sensitive interventions to prevent complications. Protocols are standardized based on severity scores (e.g., dehydration classification via weight loss or capillary refill time).Dehydration Management:
Pediatric dehydration is classified as mild (3–5% weight loss), moderate (6–9%), or severe (≥10%). Oral rehydration therapy (ORT) with World Health Organization (WHO) solution (sodium 75 mmol/L, glucose 75 mmol/L) is first-line for mild cases. Moderate-to-severe dehydration necessitates IV fluids (e.g., 0.9% NaCl or Ringer’s lactate) at 20 mL/kg over 1–2 hours, followed by maintenance rates (4 mL/kg/h for infants, 1.5 mL/kg/h for older children). Potassium supplementation is added once urine output confirms renal function.
Dehydration Fluid Resuscitation Formula:Allergic Reactions:
Bolus = 20 mL/kg × % dehydration (e.g., 10% dehydration in a 10 kg child = 200 mL bolus).
First-line treatment for mild allergic reactions (e.g., hives) includes antihistamines (e.g., cetirizine 0.25 mg/kg/day). Moderate reactions (e.g., angioedema) require oral corticosteroids (e.g., prednisolone 1–2 mg/kg/day). Anaphylaxis (respiratory distress, hypotension) mandates epinephrine 0.01 mg/kg IM (max 0.5 mg), repeated every 5–15 minutes, with IV fluids and albuterol nebulization for bronchospasm.
Urinary Tract Infections (UTIs):
Empiric therapy for uncomplicated UTIs in infants <2 months uses IV cefotaxime or ampicillin + gentamicin due to sepsis risk. Older children receive oral antibiotics (e.g., trimethoprim-sulfamethoxazole 6–8 mg/kg/day or nitrofurantoin 5–7 mg/kg/day) for 7–14 days. Febrile UTIs in infants <6 months require renal ultrasound to rule out obstruction.
Treatment Protocols for Chronic Pediatric Illnesses
Chronic conditions demand multidisciplinary care and lifestyle integration to optimize outcomes. Pediatricians collaborate with specialists (e.g., endocrinologists, neurologists) to balance symptom control, growth development, and quality of life.Type 1 Diabetes Mellitus (T1DM):
Insulin therapy is weight-based, starting with 0.5–1 unit/kg/day divided into basal-bolus regimens (e.g., glargine + lispro). Carbohydrate counting and insulin-to-carb ratios (e.g., 1 unit insulin per 10–15 g carbs) are taught to families. Continuous glucose monitors (CGMs) are recommended for children ≥2 years, with target ranges of 70–180 mg/dL. DKA prophylaxis includes sick-day management (e.g., increased insulin, frequent glucose checks).
Attention-Deficit/Hyperactivity Disorder (ADHD):
Stimulant medications (e.g., methylphenidate, amphetamine salts) are titrated slowly (e.g., 0.125 mg/kg/day, max 1 mg/kg/day) to avoid growth suppression or appetite loss. Non-stimulants (e.g., guanfacine 0.05–0.08 mg/kg/day) are preferred for children with anxiety, tics, or substance use risk. Behavioral therapy (e.g., parent training) is integrated, with school accommodations (e.g., extended test time) coordinated via 504 Plans.
Asthma:
Stepwise therapy follows GINA guidelines, with inhaled corticosteroids (ICS) (e.g., fluticasone 50–100 mcg bid) as first-line for persistent symptoms. Combination ICS/LABA (e.g., budesonide/formoterol) is used for moderate-severe asthma. Spacer devices are mandatory for children <5 years to reduce oropharyngeal deposition. Peak flow monitoring educates families on green (80–100% personal best), yellow (50–80%), and red (<50%) zones for action plans.
Age-S
Developmental & Behavioral Interventions in Pediatric Care
Pediatricians play a critical role in identifying, monitoring, and intervening in developmental and behavioral challenges in children. Early detection of delays—whether in speech, motor skills, cognition, or socioemotional functioning—enables timely referrals to specialists and targeted interventions. Behavioral concerns, such as ADHD, anxiety, or disruptive behaviors, require a structured approach combining evidence-based strategies, parent education, and multidisciplinary collaboration. Pediatricians serve as the primary coordinators, ensuring continuity of care while documenting progress through standardized tools to guide clinical decisions and family support.Developmental and behavioral assessments are foundational to pediatric care, integrating screening, diagnosis, and intervention planning. Standardized tools, parent-reported milestones, and observational data form the basis for identifying deviations from normative trajectories. When delays or concerns are detected, pediatricians initiate referrals to early intervention programs, therapists, or psychologists, while also providing immediate guidance to families on age-appropriate expectations and behavioral management techniques.
Screening Tools for Developmental Delays and Referral Processes
Pediatricians employ a tiered approach to developmental screening, combining universal screening during well-child visits with targeted assessments for high-risk populations. Universal screening occurs at key developmental stages (e.g., 9, 18, and 24 months, and annually thereafter) using validated tools such as:
Ages & Stages Questionnaires (ASQ/ASQ:SE-2): A parent-completed checklist evaluating communication, gross/fine motor skills, problem-solving, personal-social, and adaptive behavior across ages 1 month to 8.5 years.
Denver II Developmental Screening Test: A clinician-administered tool assessing personal-social, fine/gross motor, language, and cognitive milestones in children aged 0–6 years.
Modified Checklist for Autism in Toddlers (M-CHAT): A 23-item parent questionnaire designed to identify early signs of autism spectrum disorder (ASD) in children aged 16–30 months, followed by a follow-up interview for false positives.
Early Language Milestone Scale (ELM-2): Focuses on receptive and expressive language delays in children aged 12–36 months. Targeted screening is indicated for children with risk factors (e.g., prematurity, genetic syndromes, family history of developmental disorders) or parental concerns. Tools such as the Bayley Scales of Infant and Toddler Development (Bayley-IV) provide comprehensive cognitive, motor, and socioemotional assessments for children aged 1–42 months. When delays are identified, pediatricians initiate referrals to:
Early Intervention (EI) Programs: Federally mandated under the Individuals with Disabilities Education Act (IDEA), EI provides services (speech therapy, occupational therapy, physical therapy) for children aged birth–3 years with developmental delays.
School-Based Evaluations: For children aged 3–21 years, referrals to school psychologists or special education teams ensure access to Individualized Education Programs (IEPs).
Specialist Consultations: Pediatric neurologists, developmental-behavioral pediatricians, or child psychologists conduct further evaluations for complex cases (e.g., global developmental delay, ASD, cerebral palsy). Documentation of referrals includes:
Reason for referral (e.g., "Delayed expressive language at 24 months per ASQ-3").
Recommended specialist and contact information.
Follow-up timeline (e.g., "Schedule occupational therapy evaluation within 4 weeks").
Parent education provided (e.g., "Discussed age-appropriate speech milestones and home strategies").
Standardized screening tools are not diagnostic but serve as early warning systems. False negatives may occur in children with subtle delays, necessitating clinical judgment and parental input.
Strategies for Addressing Behavioral Concerns
Behavioral challenges in childhood—ranging from typical temper tantrums to clinical disorders like ADHD or anxiety—require a biopsychosocial approach that addresses underlying causes while teaching adaptive coping strategies. Pediatricians employ a three-tiered framework for intervention:
1. Universal Prevention: Education and guidance for all families on normative behavioral development.
2. Selective Interventions: Targeted strategies for children exhibiting early signs of risk (e.g., excessive shyness, aggression).
3. Indicated Treatments: Evidence-based protocols for diagnosed disorders (e.g., behavioral therapy for ADHD, cognitive-behavioral therapy for anxiety).Common behavioral concerns and interventions include:
Tantrums and Oppositional Defiant Disorder (ODD):
Parent Training: Teaching consistent limit-setting, positive reinforcement, and time-in/out techniques (e.g., "When-Then" statements: "When you put your toys away, then we can read a book").
Environmental Modifications: Reducing triggers (e.g., hunger, fatigue) and structuring routines to minimize power struggles.
Developmental Context: Differentiating between typical frustration (e.g., toddler tantrums) and ODD, which requires referrals to child psychologists for parent-child interaction therapy (PCIT). - Attention-Deficit/Hyperactivity Disorder (ADHD):
Behavioral Therapy: First-line treatment for preschoolers, including Parent Training in Behavior Management (PTBM) and classroom-based interventions (e.g., token economies).
Medication Management: Stimulants (e.g., methylphenidate, amphetamines) or non-stimulants (e.g., atomoxetine) for moderate-severe cases, with pediatricians monitoring growth, sleep, and side effects.
Collaboration with Schools: Coordinating with teachers to implement 504 Plans or IEPs, including accommodations like preferential seating or extended test time. - Anxiety Disorders:
Cognitive-Behavioral Therapy (CBT): Pediatricians refer children to specialists for CBT for youth, which includes exposure therapy, cognitive restructuring, and relaxation techniques (e.g., diaphragmatic breathing).
Parent-Child Interaction: Techniques such as gradual exposure (e.g., for school refusal) or psychoeducation on anxiety triggers (e.g., social phobias).
Pharmacotherapy: Selective serotonin reuptake inhibitors (SSRIs) for severe cases, with pediatricians monitoring for emotional blunting or suicidal ideation. Parent counseling techniques emphasize:
Active Listening: Validating concerns without judgment (e.g., "It sounds like you’re feeling overwhelmed by his meltdowns").
Collaborative Goal-Setting: Involving parents in designing achievable behavioral targets (e.g., "Let’s track how often he completes chores without reminders").
Resource Provision: Directing families to evidence-based programs (e.g., Triple P Positive Parenting Program) or support groups (e.g., CHADD for ADHD families).
Behavioral interventions are most effective when delivered in a multimodal approach, combining parent training, child-focused strategies, and environmental adjustments.
Coordination of Care with Specialists and Multidisciplinary Teams
Complex developmental or behavioral cases often require interdisciplinary collaboration, with pediatricians serving as the case manager to ensure seamless communication and continuity of care. The multidisciplinary team may include:
Developmental Specialists: Occupational therapists (OT) for motor delays, speech-language pathologists (SLP) for communication disorders, and physical therapists (PT) for gross motor impairments.
Mental Health Professionals: Child psychologists or psychiatrists for ADHD, ASD, or mood disorders; social workers for family support.
Educational Partners: School psychologists, special education teachers, and IEPs teams to bridge clinical and academic needs.
Subspecialists: Pediatric neurologists for genetic or neurological conditions (e.g., tuberous sclerosis), geneticists for syndromic delays. Key roles of pediatricians in coordination:
Initial Referral and Triaging: Determining urgency (e.g., immediate referral for suspected autism vs. developmental monitoring for mild delays).
Shared Decision-Making: Presenting findings to specialists and discussing treatment options with families (e.g., "The OT recommends handwriting interventions, but we can also try pencil grips at home").
Progress Tracking: Attending team meetings (e.g., Individualized Family Service Plan (IFSP) for EI programs) to align clinical and therapeutic goals.
Conflict Resolution: Mediating discrepancies between specialist recommendations (e.g., balancing medication trials with behavioral therapy). Documentation of multidisciplinary care includes:
Shared Medical Records: Using interoperable electronic health records (EHRs) to track referrals, specialist notes, and progress (e.g., "OT report: Improved fine motor skills with adaptive utensils").
Standardized Assessments: Incorporating scores from tools like the Vineland Adaptive Behavior Scales or Conners Rating Scales into the medical record.
Care Plans: Collaboratively developed timelines (e.g., "Re-evaluate speech progress in 3 months; adjust therapy frequency if no improvement").
Effective coordination relies on clear communication
Preventive Care & Parent Education in Pediatric Practice
Preventive care forms the cornerstone of pediatric medicine, emphasizing early intervention, health promotion, and parental empowerment to mitigate risks and foster lifelong well-being. Pediatricians integrate structured screenings, evidence-based counseling, and safety education into routine visits to address physical, developmental, and psychosocial needs. This approach not only reduces acute and chronic disease burden but also builds trust and collaboration between healthcare providers and families. Parent education extends beyond clinical guidelines to practical, culturally sensitive strategies that align with a child’s age-specific vulnerabilities and developmental milestones.
"Preventive care in pediatrics is not just about treating illness—it’s about creating environments where children thrive by equipping parents with knowledge, tools, and confidence to navigate challenges proactively."
— American Academy of Pediatrics (AAP) Policy Statement on Periodicity Schedule
Age-Specific Preventive Services Checklist
Pediatric preventive care follows a standardized schedule aligned with the Bright Futures Guidelines and CDC’s Childhood Immunization Schedule, tailored to cognitive, physical, and emotional growth stages. Services include vaccinations, developmental screenings, and anticipatory guidance to address emerging needs. Below is a consolidated checklist by age group, incorporating recommendations from the AAP and World Health Organization (WHO).
-
Newborn to 12 Months
- Vaccinations: Hepatitis B (HepB), Rotavirus (RV), Diphtheria-Tetanus-Pertussis (DTaP), Haemophilus influenzae type b (Hib), Pneumococcal conjugate (PCV13), Inactivated Polio Virus (IPV), and seasonal influenza (6+ months).
- Screenings:
- Newborn metabolic screening (e.g., phenylketonuria, congenital hypothyroidism).
- Hearing test (universal screening by 1 month).
- Critical congenital heart disease (CCHD) pulse oximetry (before discharge).
- Developmental & Behavioral:
- Parenting support (e.g., safe sleep practices, SIDS prevention).
- Breastfeeding/lactation counseling (if applicable).
- Maternal mental health screening (e.g., postpartum depression).
- Safety:
- Car seat installation verification (rear-facing until 2 years).
- Home safety assessment (e.g., outlet covers, cabinet locks).
- Poison control number distribution (1-800-222-1222).
-
1–4 Years
- Vaccinations: MMR, Varicella, HepA, annual influenza.
- Screenings:
- Autism spectrum disorder (ASD) and developmental delays (18 and 24 months).
- Lead screening (high-risk areas).
- Vision (3–4 years) and hearing (4 years).
- Developmental & Behavioral:
- Language and social-emotional milestones (e.g., sharing, toileting).
- Behavior management (e.g., tantrums, sleep training).
- Introduction to nutrition (e.g., choking hazards, balanced meals).
- Safety:
- Water safety (e.g., pool barriers, drowning prevention).
- Bike helmet use and pedestrian safety.
- Firearm storage education (if applicable).
-
5–10 Years
- Vaccinations: Tdap (11–12 years), HPV (9–12 years), meningococcal (11–12 years).
- Screenings:
- Blood pressure (3+ years).
- Dyslexia/learning disability screening (school-age).
- Obesity and BMI assessment (annual).
- Developmental & Behavioral:
- Puberty education (e.g., body changes, hygiene).
- Screen time limits and digital literacy.
- Anxiety/depression screening (9+ years).
- Safety:
- Seat belt use and passenger safety laws.
- Stranger danger and online safety.
- Sports injury prevention (e.g., concussion protocols).
-
11–18 Years
- Vaccinations: MenACWY booster, HPV (if not initiated), annual influenza.
- Screenings:
- Sexual health (STI testing, contraception counseling).
- Substance use screening (e.g., vaping, alcohol).
- Depression and suicide risk assessment (annual).
- Developmental & Behavioral:
- Transition to adult healthcare planning.
- Mental health coping strategies (e.g., stress, self-esteem).
- College/university health preparedness (e.g., immunization records).
- Safety:
- Driving safety and graduated licensing laws.
- Consent and boundary-setting discussions.
- Emergency preparedness (e.g., natural disasters, first aid).
"Preventive visits are opportunities to normalize conversations about health that parents might otherwise avoid—turning stigma into support and uncertainty into actionable steps."
— Centers for Disease Control and Prevention (CDC), Bright Futures Toolkit
Parent Education on Child Safety: Evidence-Based Guidelines
Pediatricians employ a trauma-informed, layered approach to safety education, combining direct instruction with environmental assessments and behavioral reinforcement. Research from the National Safe Kids Campaign indicates that 70% of childhood injuries occur in the home, emphasizing the need for proactive, age-specific interventions. Below are structured protocols pediatricians use to address critical safety domains.#### Car Seat and Restraint Safety
Incorrect car seat use contributes to 30% of child passenger fatalities (Insurance Institute for Highway Safety, 2023). Pediatricians:
Demonstrate proper installation using the "Pinch Test" (seat should not move more than 1 inch side-to-side at the belt path).
Provide a car seat checklist by age:Age
Seat Type
Key Features
Birth–2 years
Rear-facing convertible seat
5-point harness, rear-facing until at least 2 years or max height/weight limit.
2–4 years
Forward-facing with harness
Top tether strap, harness straps at or above shoulders.
4–8 years
Booster seat
Seat belt fits snugly across hips/thighs (lap belt), shoulder belt at collarbone.
8–12 years
Seat belt (if fits properly)
Lap belt on hips, shoulder belt across chest; no slack.
Refer to certified technicians (e.g., Child Passenger Safety Technicians) for complex installations. #### Poison and Medication Safety
Unintentional poisoning is the leading cause of injury-related death in children under 5 (CDC, 2022). Pediatricians:
Teach the "4 D’s" for poison exposure:- Detect potential hazards (e.g., cleaning products, medications, carbon monoxide).
Distract children from accessing unsafe areas (e.g., childproof locks on cabinets).
Dispose of medications properly (e.g., Drug Enforcement Administration (DEA) Take-Back Days).
Demonstrate first aid (e.g., calling Poison Control immediately, not inducing vomiting).
Provide a home safety
Emergency & Urgent Care Protocols in Pediatric Practice
Pediatric emergencies require rapid assessment and intervention to mitigate life-threatening conditions. Pediatricians employ standardized triage criteria, stabilization techniques, and coordinated communication with emergency services to ensure optimal outcomes. These protocols prioritize age-specific physiological differences, such as smaller airway diameters, higher metabolic rates, and limited compensatory mechanisms in children. Effective emergency management relies on structured decision-making, adherence to evidence-based guidelines, and seamless transitions to higher levels of care when necessary.The assessment of pediatric emergencies begins with triage, a systematic evaluation to determine the severity of symptoms and allocate appropriate resources. Key factors include the duration and progression of symptoms, vital sign abnormalities, and clinical presentation. For example, a fever lasting over 48 hours in an infant may indicate a serious bacterial infection, while respiratory distress with nasal flaring, grunting, or retractions signals respiratory failure. Head trauma in children often requires immediate evaluation for intracranial hemorrhage or cerebral edema, particularly if accompanied by altered mental status or vomiting.
Triage Criteria for Pediatric Emergencies
Pediatric triage systems, such as the Pediatric Assessment Triangle (PAT) and Modified Early Warning Score (MEWS), guide initial evaluations. The PAT assesses three critical domains: appearance (work of breathing, circulation), work of breathing (respiratory effort), and circulation (skin perfusion). MEWS assigns numerical values to vital signs (e.g., heart rate, oxygen saturation) to quantify clinical deterioration.Common triage indicators for urgency:
Respiratory Distress: Tachypnea (>60 breaths/min in infants, >40 in older children), cyanosis, or apnea.
Hypotension: Systolic blood pressure <70 mmHg (infants) or <80 mmHg (older children) indicates shock.
Neurological Deterioration: Lethargy, seizures, or focal deficits suggest intracranial pathology.
Severe Dehydration: Sunken fontanelles (infants), dry mucous membranes, or absent urine output.
Trauma-Related Instability: Altered consciousness, signs of bleeding, or suspected fractures with neurovascular compromise. Pediatricians use color-coded systems (e.g., Emergency Severity Index (ESI)) to prioritize care:
ESI Level 1 (Immediate): Resuscitation required (e.g., cardiac arrest, severe anaphylaxis).
ESI Level 2 (Emergent): High-risk conditions (e.g., status epilepticus, diabetic ketoacidosis).
ESI Level 3–5: Urgent or non-urgent cases managed in outpatient settings.
Stabilization Techniques in Pediatric Emergencies
Stabilization follows the ABCs of pediatric resuscitation: Airway, Breathing, Circulation, with Disability (neurological status) and Exposure (environmental control) integrated into the assessment.Airway Management:
Children are prone to upper airway obstruction due to larger tonsils, smaller nares, and softer tracheal cartilage. Techniques include:
Positioning: Head tilt-chin lift (unless trauma suspected) or jaw thrust for unconscious patients.
Suctioning: Bulb or wall suction to clear secretions or foreign bodies.
Oropharyngeal/Nasopharyngeal Airway: Sized appropriately (e.g., Guedel airway length = distance from mouth to angle of mandible).
Endotracheal Intubation: Performed by trained personnel with pediatric-sized equipment (e.g., ET tube size = (age/4) + 4 for uncuffed tubes). Breathing Support:
Oxygen Therapy: High-flow nasal cannula (HFNC) or non-rebreather mask for hypoxia.
Positive Pressure Ventilation: Bag-valve-mask (BVM) with pediatric-sized bags (e.g., 240 mL for infants, 500–750 mL for children).
Chest Decompression: Needle thoracostomy for tension pneumothorax (2nd intercostal space, midclavicular line). Circulation and Shock Treatment:
Pediatric shock presents as compensated (tachycardia, delayed cap refill) or decompensated (hypotension, mottling). Management includes:
IV/IO Access: Peripheral IV (scalp veins in infants) or intraosseous (IO) needle (tibia or humerus) for rapid fluid administration.
Fluid Resuscitation: Boltus of 20 mL/kg NS or LR over 5–10 minutes for hypovolemic shock.
Vasopressors: Dopamine or epinephrine for refractory shock (titrated based on blood pressure).
Blood Transfusion: For hemorrhagic shock (e.g., trauma, sickle cell crisis). Disability and Exposure:
Neurological Assessment: AVPU scale (Alert, Verbal, Pain, Unresponsive) or Glasgow Coma Scale (GCS) adapted for age.
Environmental Control: Remove wet clothing, warm with blankets, and monitor for hypothermia (critical in neonates).
Communication with Emergency Services
Effective communication ensures seamless transitions for critically ill children. Pediatricians follow structured protocols when contacting emergency services (e.g., 911, EMS, or pediatric ER transfer):911 Protocols:
SBAR Framework (Situation, Background, Assessment, Recommendation):
Situation: "3-month-old infant with apnea and cyanosis post-feeding."
Background: "Premature, history of bronchiolitis; last fed 1 hour ago."
Assessment: "Respiratory distress, oxygen saturation 82% on room air."
Recommendation: "Immediate transport to pediatric ER with BVM support."
EMS Activation: Request pediatric-trained EMS or pediatric life support (PLS) teams when available. Transfer to Pediatric ERs:
Stabilization Before Transfer: Ensure ABCs secured, IV fluids running, and continuous monitoring (e.g., pulse oximetry, cardiac telemetry).
Transport Documentation: Provide pre-transfer checklist (e.g., PediTRANSFER guidelines) including:
Vital signs, weight, allergies, and current medications.
ABC status, fluid balance, and response to interventions.
Family contact information and consent for transfer.
Destination Selection: Direct to pediatric ERs or trauma centers with pediatric capabilities (e.g., American College of Surgeons (ACS) verified levels). Critical Communication Tools:
Pediatric Advanced Life Support (PALS) Algorithms: Standardized for bradycardia, tachycardia, and shock.
Electronic Health Record (EHR) Integration: Real-time transfer of labs, imaging, and notes to receiving facilities.
Telemedicine Consults: For rural areas, pediatric telehealth bridges gaps in specialized care.
Comparison of Common Pediatric Emergencies and Immediate Interventions
The following table outlines high-acuity pediatric emergencies, their clinical presentations, and immediate interventions based on American Academy of Pediatrics (AAP) and Emergency Nurses Association (ENA) guidelines.
Emergency Condition
Clinical Presentation
Immediate Interventions
Disposition
Anaphylaxis
- Urticaria, angioedema, stridor, or wheezing.
- Hypotension or tachycardia (bradycardia in late stages).
- Gastrointestinal symptoms (vomiting, diarrhea).
- Epinephrine 0.01 mg/kg IM (max 0.5 mg) every 5–15 minutes if no response.
- IV fluids (20 mL/kg NS bolus) for hypotension.
- Oxygen, albuterol nebulization, and H1/H2 blockers (diphenhydramine, ranitidine).
- Consider glucocorticoids (methylprednisolone) for refractory cases.
Observation in ICU for 24 hours post-treatment; discharge with epinephrine auto-injector and actionA pediatrician’s impact on a child’s health transcends immediate medical needs, shaping lifelong habits and resilience. Through systematic assessments, early interventions, and continuous parent engagement, they mitigate risks, manage chronic conditions, and promote developmental milestones. Their role as both medical guardian and educator ensures children receive holistic care—addressing physical, emotional, and preventive health with equal importance. By leveraging specialized tools, collaborative networks, and clear communication, pediatricians not only treat illnesses but empower families to nurture thriving, healthy futures.
FAQ
What can a pediatrician do to help a child with an ingrown toenail?
A pediatrician may assess the ingrown toenail for infection (redness, swelling, or pus) and recommend soaking the foot in warm water, gently lifting the nail edge, or using antibiotic ointment. If infected, they might prescribe oral antibiotics or, in severe cases, refer to a podiatrist for proper nail trimming or drainage. They can also advise on proper nail care to prevent recurrence.
What treatments or advice will a pediatrician give for a child with constipation?
A pediatrician will first evaluate the child’s diet, hydration, and bowel habits, then recommend dietary changes like more fiber (fruits, veggies, whole grains) and fluids. They may suggest over-the-counter laxatives (e.g., polyethylene glycol) or stool softeners if needed, and teach parents gentle toilet-training techniques or abdominal massage. Chronic cases might require further testing or referral to a specialist.
How does a pediatrician treat a child who has diarrhea?
A pediatrician will assess dehydration risks (sunken eyes, dry mouth, few wet diapers) and recommend oral rehydration solutions (ORS) like Pedialyte. They may suggest a bland diet (rice, bananas, applesauce) and avoid dairy or sugary drinks. For severe or persistent diarrhea, they might prescribe probiotics, anti-diarrheal meds (rarely in young kids), or test for infections like rotavirus or parasites.
What does a pediatrician recommend for treating diaper rash in babies?
A pediatrician will first check for yeast infections (red, satellite lesions) or irritation from stool/urine, then advise frequent diaper changes, barrier creams (zinc oxide), and air-drying. For yeast rashes, they may prescribe antifungal creams (e.g., clotrimazole). Severe or persistent rashes could signal allergies or other conditions needing further evaluation.
What will a pediatrician do if a baby has reflux?
A pediatrician will confirm reflux (spitting up, arching back) and rule out GERD or complications like poor weight gain. They may recommend feeding adjustments (smaller, more frequent meals; thickening formula), keeping the baby upright after feeds, and avoiding overstimulation. Severe cases (with vomiting, pain, or failure to thrive) might require acid-reducing meds or referral to a gastroenterologist.
What treatments does a pediatrician use for croup in children?
A pediatrician will assess the child’s breathing (stridor, barking cough) and recommend cool mist, steam, or humidified air to ease symptoms. For moderate-severe croup, they may prescribe a single dose of oral dexamethasone (a steroid) to reduce swelling. Severe cases with respiratory distress require immediate ER care, possibly with nebulized epinephrine or hospitalization.
Developmental & Behavioral Interventions in Pediatric Care
Pediatricians play a critical role in identifying, monitoring, and intervening in developmental and behavioral challenges in children. Early detection of delays—whether in speech, motor skills, cognition, or socioemotional functioning—enables timely referrals to specialists and targeted interventions. Behavioral concerns, such as ADHD, anxiety, or disruptive behaviors, require a structured approach combining evidence-based strategies, parent education, and multidisciplinary collaboration. Pediatricians serve as the primary coordinators, ensuring continuity of care while documenting progress through standardized tools to guide clinical decisions and family support.Developmental and behavioral assessments are foundational to pediatric care, integrating screening, diagnosis, and intervention planning. Standardized tools, parent-reported milestones, and observational data form the basis for identifying deviations from normative trajectories. When delays or concerns are detected, pediatricians initiate referrals to early intervention programs, therapists, or psychologists, while also providing immediate guidance to families on age-appropriate expectations and behavioral management techniques.
Screening Tools for Developmental Delays and Referral Processes
Pediatricians employ a tiered approach to developmental screening, combining universal screening during well-child visits with targeted assessments for high-risk populations. Universal screening occurs at key developmental stages (e.g., 9, 18, and 24 months, and annually thereafter) using validated tools such as:Targeted screening is indicated for children with risk factors (e.g., prematurity, genetic syndromes, family history of developmental disorders) or parental concerns. Tools such as the Bayley Scales of Infant and Toddler Development (Bayley-IV) provide comprehensive cognitive, motor, and socioemotional assessments for children aged 1–42 months. When delays are identified, pediatricians initiate referrals to:
Documentation of referrals includes:
Standardized screening tools are not diagnostic but serve as early warning systems. False negatives may occur in children with subtle delays, necessitating clinical judgment and parental input.
Strategies for Addressing Behavioral Concerns
Behavioral challenges in childhood—ranging from typical temper tantrums to clinical disorders like ADHD or anxiety—require a biopsychosocial approach that addresses underlying causes while teaching adaptive coping strategies. Pediatricians employ a three-tiered framework for intervention:1. Universal Prevention: Education and guidance for all families on normative behavioral development.
2. Selective Interventions: Targeted strategies for children exhibiting early signs of risk (e.g., excessive shyness, aggression).
3. Indicated Treatments: Evidence-based protocols for diagnosed disorders (e.g., behavioral therapy for ADHD, cognitive-behavioral therapy for anxiety).
Common behavioral concerns and interventions include:
- Attention-Deficit/Hyperactivity Disorder (ADHD):
- Anxiety Disorders:
Parent counseling techniques emphasize:
Behavioral interventions are most effective when delivered in a multimodal approach, combining parent training, child-focused strategies, and environmental adjustments.
Coordination of Care with Specialists and Multidisciplinary Teams
Complex developmental or behavioral cases often require interdisciplinary collaboration, with pediatricians serving as the case manager to ensure seamless communication and continuity of care. The multidisciplinary team may include:Key roles of pediatricians in coordination:
Documentation of multidisciplinary care includes:
Effective coordination relies on clear communication
Preventive Care & Parent Education in Pediatric Practice
Preventive care forms the cornerstone of pediatric medicine, emphasizing early intervention, health promotion, and parental empowerment to mitigate risks and foster lifelong well-being. Pediatricians integrate structured screenings, evidence-based counseling, and safety education into routine visits to address physical, developmental, and psychosocial needs. This approach not only reduces acute and chronic disease burden but also builds trust and collaboration between healthcare providers and families. Parent education extends beyond clinical guidelines to practical, culturally sensitive strategies that align with a child’s age-specific vulnerabilities and developmental milestones.
"Preventive care in pediatrics is not just about treating illness—it’s about creating environments where children thrive by equipping parents with knowledge, tools, and confidence to navigate challenges proactively." — American Academy of Pediatrics (AAP) Policy Statement on Periodicity ScheduleAge-Specific Preventive Services Checklist
Pediatric preventive care follows a standardized schedule aligned with the Bright Futures Guidelines and CDC’s Childhood Immunization Schedule, tailored to cognitive, physical, and emotional growth stages. Services include vaccinations, developmental screenings, and anticipatory guidance to address emerging needs. Below is a consolidated checklist by age group, incorporating recommendations from the AAP and World Health Organization (WHO).
- Newborn to 12 Months
- Vaccinations: Hepatitis B (HepB), Rotavirus (RV), Diphtheria-Tetanus-Pertussis (DTaP), Haemophilus influenzae type b (Hib), Pneumococcal conjugate (PCV13), Inactivated Polio Virus (IPV), and seasonal influenza (6+ months).
- Screenings:
- Newborn metabolic screening (e.g., phenylketonuria, congenital hypothyroidism).
- Hearing test (universal screening by 1 month).
- Critical congenital heart disease (CCHD) pulse oximetry (before discharge).
- Developmental & Behavioral:
- Parenting support (e.g., safe sleep practices, SIDS prevention).
- Breastfeeding/lactation counseling (if applicable).
- Maternal mental health screening (e.g., postpartum depression).
- Safety:
- Car seat installation verification (rear-facing until 2 years).
- Home safety assessment (e.g., outlet covers, cabinet locks).
- Poison control number distribution (1-800-222-1222).
- 1–4 Years
- Vaccinations: MMR, Varicella, HepA, annual influenza.
- Screenings:
- Autism spectrum disorder (ASD) and developmental delays (18 and 24 months).
- Lead screening (high-risk areas).
- Vision (3–4 years) and hearing (4 years).
- Developmental & Behavioral:
- Language and social-emotional milestones (e.g., sharing, toileting).
- Behavior management (e.g., tantrums, sleep training).
- Introduction to nutrition (e.g., choking hazards, balanced meals).
- Safety:
- Water safety (e.g., pool barriers, drowning prevention).
- Bike helmet use and pedestrian safety.
- Firearm storage education (if applicable).
- 5–10 Years
- Vaccinations: Tdap (11–12 years), HPV (9–12 years), meningococcal (11–12 years).
- Screenings:
- Blood pressure (3+ years).
- Dyslexia/learning disability screening (school-age).
- Obesity and BMI assessment (annual).
- Developmental & Behavioral:
- Puberty education (e.g., body changes, hygiene).
- Screen time limits and digital literacy.
- Anxiety/depression screening (9+ years).
- Safety:
- Seat belt use and passenger safety laws.
- Stranger danger and online safety.
- Sports injury prevention (e.g., concussion protocols).
- 11–18 Years
- Vaccinations: MenACWY booster, HPV (if not initiated), annual influenza.
- Screenings:
- Sexual health (STI testing, contraception counseling).
- Substance use screening (e.g., vaping, alcohol).
- Depression and suicide risk assessment (annual).
- Developmental & Behavioral:
- Transition to adult healthcare planning.
- Mental health coping strategies (e.g., stress, self-esteem).
- College/university health preparedness (e.g., immunization records).
- Safety:
- Driving safety and graduated licensing laws.
- Consent and boundary-setting discussions.
- Emergency preparedness (e.g., natural disasters, first aid).
"Preventive visits are opportunities to normalize conversations about health that parents might otherwise avoid—turning stigma into support and uncertainty into actionable steps." — Centers for Disease Control and Prevention (CDC), Bright Futures ToolkitParent Education on Child Safety: Evidence-Based Guidelines
Pediatricians employ a trauma-informed, layered approach to safety education, combining direct instruction with environmental assessments and behavioral reinforcement. Research from the National Safe Kids Campaign indicates that 70% of childhood injuries occur in the home, emphasizing the need for proactive, age-specific interventions. Below are structured protocols pediatricians use to address critical safety domains.#### Car Seat and Restraint Safety
Incorrect car seat use contributes to 30% of child passenger fatalities (Insurance Institute for Highway Safety, 2023). Pediatricians:
Demonstrate proper installation using the "Pinch Test" (seat should not move more than 1 inch side-to-side at the belt path). Provide a car seat checklist by age:
Age Seat Type Key Features Birth–2 years Rear-facing convertible seat 5-point harness, rear-facing until at least 2 years or max height/weight limit. 2–4 years Forward-facing with harness Top tether strap, harness straps at or above shoulders. 4–8 years Booster seat Seat belt fits snugly across hips/thighs (lap belt), shoulder belt at collarbone. 8–12 years Seat belt (if fits properly) Lap belt on hips, shoulder belt across chest; no slack. Refer to certified technicians (e.g., Child Passenger Safety Technicians) for complex installations. #### Poison and Medication Safety
Unintentional poisoning is the leading cause of injury-related death in children under 5 (CDC, 2022). Pediatricians:
Teach the "4 D’s" for poison exposure:
- Detect potential hazards (e.g., cleaning products, medications, carbon monoxide).
Distract children from accessing unsafe areas (e.g., childproof locks on cabinets). Dispose of medications properly (e.g., Drug Enforcement Administration (DEA) Take-Back Days). Demonstrate first aid (e.g., calling Poison Control immediately, not inducing vomiting). Provide a home safety Emergency & Urgent Care Protocols in Pediatric Practice
Pediatric emergencies require rapid assessment and intervention to mitigate life-threatening conditions. Pediatricians employ standardized triage criteria, stabilization techniques, and coordinated communication with emergency services to ensure optimal outcomes. These protocols prioritize age-specific physiological differences, such as smaller airway diameters, higher metabolic rates, and limited compensatory mechanisms in children. Effective emergency management relies on structured decision-making, adherence to evidence-based guidelines, and seamless transitions to higher levels of care when necessary.The assessment of pediatric emergencies begins with triage, a systematic evaluation to determine the severity of symptoms and allocate appropriate resources. Key factors include the duration and progression of symptoms, vital sign abnormalities, and clinical presentation. For example, a fever lasting over 48 hours in an infant may indicate a serious bacterial infection, while respiratory distress with nasal flaring, grunting, or retractions signals respiratory failure. Head trauma in children often requires immediate evaluation for intracranial hemorrhage or cerebral edema, particularly if accompanied by altered mental status or vomiting.
Triage Criteria for Pediatric Emergencies
Pediatric triage systems, such as the Pediatric Assessment Triangle (PAT) and Modified Early Warning Score (MEWS), guide initial evaluations. The PAT assesses three critical domains: appearance (work of breathing, circulation), work of breathing (respiratory effort), and circulation (skin perfusion). MEWS assigns numerical values to vital signs (e.g., heart rate, oxygen saturation) to quantify clinical deterioration.Common triage indicators for urgency:
Respiratory Distress: Tachypnea (>60 breaths/min in infants, >40 in older children), cyanosis, or apnea. Hypotension: Systolic blood pressure <70 mmHg (infants) or <80 mmHg (older children) indicates shock. Neurological Deterioration: Lethargy, seizures, or focal deficits suggest intracranial pathology. Severe Dehydration: Sunken fontanelles (infants), dry mucous membranes, or absent urine output. Trauma-Related Instability: Altered consciousness, signs of bleeding, or suspected fractures with neurovascular compromise. Pediatricians use color-coded systems (e.g., Emergency Severity Index (ESI)) to prioritize care:
ESI Level 1 (Immediate): Resuscitation required (e.g., cardiac arrest, severe anaphylaxis). ESI Level 2 (Emergent): High-risk conditions (e.g., status epilepticus, diabetic ketoacidosis). ESI Level 3–5: Urgent or non-urgent cases managed in outpatient settings. Stabilization Techniques in Pediatric Emergencies
Stabilization follows the ABCs of pediatric resuscitation: Airway, Breathing, Circulation, with Disability (neurological status) and Exposure (environmental control) integrated into the assessment.Airway Management:
Children are prone to upper airway obstruction due to larger tonsils, smaller nares, and softer tracheal cartilage. Techniques include:
Positioning: Head tilt-chin lift (unless trauma suspected) or jaw thrust for unconscious patients. Suctioning: Bulb or wall suction to clear secretions or foreign bodies. Oropharyngeal/Nasopharyngeal Airway: Sized appropriately (e.g., Guedel airway length = distance from mouth to angle of mandible). Endotracheal Intubation: Performed by trained personnel with pediatric-sized equipment (e.g., ET tube size = (age/4) + 4 for uncuffed tubes). Breathing Support:
Oxygen Therapy: High-flow nasal cannula (HFNC) or non-rebreather mask for hypoxia. Positive Pressure Ventilation: Bag-valve-mask (BVM) with pediatric-sized bags (e.g., 240 mL for infants, 500–750 mL for children). Chest Decompression: Needle thoracostomy for tension pneumothorax (2nd intercostal space, midclavicular line). Circulation and Shock Treatment:
Pediatric shock presents as compensated (tachycardia, delayed cap refill) or decompensated (hypotension, mottling). Management includes:
IV/IO Access: Peripheral IV (scalp veins in infants) or intraosseous (IO) needle (tibia or humerus) for rapid fluid administration. Fluid Resuscitation: Boltus of 20 mL/kg NS or LR over 5–10 minutes for hypovolemic shock. Vasopressors: Dopamine or epinephrine for refractory shock (titrated based on blood pressure). Blood Transfusion: For hemorrhagic shock (e.g., trauma, sickle cell crisis). Disability and Exposure:
Neurological Assessment: AVPU scale (Alert, Verbal, Pain, Unresponsive) or Glasgow Coma Scale (GCS) adapted for age. Environmental Control: Remove wet clothing, warm with blankets, and monitor for hypothermia (critical in neonates). Communication with Emergency Services
Effective communication ensures seamless transitions for critically ill children. Pediatricians follow structured protocols when contacting emergency services (e.g., 911, EMS, or pediatric ER transfer):911 Protocols:
SBAR Framework (Situation, Background, Assessment, Recommendation): Situation: "3-month-old infant with apnea and cyanosis post-feeding." Background: "Premature, history of bronchiolitis; last fed 1 hour ago." Assessment: "Respiratory distress, oxygen saturation 82% on room air." Recommendation: "Immediate transport to pediatric ER with BVM support." EMS Activation: Request pediatric-trained EMS or pediatric life support (PLS) teams when available. Transfer to Pediatric ERs:
Stabilization Before Transfer: Ensure ABCs secured, IV fluids running, and continuous monitoring (e.g., pulse oximetry, cardiac telemetry). Transport Documentation: Provide pre-transfer checklist (e.g., PediTRANSFER guidelines) including: Vital signs, weight, allergies, and current medications. ABC status, fluid balance, and response to interventions. Family contact information and consent for transfer. Destination Selection: Direct to pediatric ERs or trauma centers with pediatric capabilities (e.g., American College of Surgeons (ACS) verified levels). Critical Communication Tools:
Pediatric Advanced Life Support (PALS) Algorithms: Standardized for bradycardia, tachycardia, and shock. Electronic Health Record (EHR) Integration: Real-time transfer of labs, imaging, and notes to receiving facilities. Telemedicine Consults: For rural areas, pediatric telehealth bridges gaps in specialized care. Comparison of Common Pediatric Emergencies and Immediate Interventions
The following table outlines high-acuity pediatric emergencies, their clinical presentations, and immediate interventions based on American Academy of Pediatrics (AAP) and Emergency Nurses Association (ENA) guidelines.
Emergency Condition Clinical Presentation Immediate Interventions Disposition Anaphylaxis
- Urticaria, angioedema, stridor, or wheezing.
- Hypotension or tachycardia (bradycardia in late stages).
- Gastrointestinal symptoms (vomiting, diarrhea).
- Epinephrine 0.01 mg/kg IM (max 0.5 mg) every 5–15 minutes if no response.
- IV fluids (20 mL/kg NS bolus) for hypotension.
- Oxygen, albuterol nebulization, and H1/H2 blockers (diphenhydramine, ranitidine).
- Consider glucocorticoids (methylprednisolone) for refractory cases.
Observation in ICU for 24 hours post-treatment; discharge with epinephrine auto-injector and action A pediatrician’s impact on a child’s health transcends immediate medical needs, shaping lifelong habits and resilience. Through systematic assessments, early interventions, and continuous parent engagement, they mitigate risks, manage chronic conditions, and promote developmental milestones. Their role as both medical guardian and educator ensures children receive holistic care—addressing physical, emotional, and preventive health with equal importance. By leveraging specialized tools, collaborative networks, and clear communication, pediatricians not only treat illnesses but empower families to nurture thriving, healthy futures.
FAQ
What can a pediatrician do to help a child with an ingrown toenail?
A pediatrician may assess the ingrown toenail for infection (redness, swelling, or pus) and recommend soaking the foot in warm water, gently lifting the nail edge, or using antibiotic ointment. If infected, they might prescribe oral antibiotics or, in severe cases, refer to a podiatrist for proper nail trimming or drainage. They can also advise on proper nail care to prevent recurrence.
What treatments or advice will a pediatrician give for a child with constipation?
A pediatrician will first evaluate the child’s diet, hydration, and bowel habits, then recommend dietary changes like more fiber (fruits, veggies, whole grains) and fluids. They may suggest over-the-counter laxatives (e.g., polyethylene glycol) or stool softeners if needed, and teach parents gentle toilet-training techniques or abdominal massage. Chronic cases might require further testing or referral to a specialist.
How does a pediatrician treat a child who has diarrhea?
A pediatrician will assess dehydration risks (sunken eyes, dry mouth, few wet diapers) and recommend oral rehydration solutions (ORS) like Pedialyte. They may suggest a bland diet (rice, bananas, applesauce) and avoid dairy or sugary drinks. For severe or persistent diarrhea, they might prescribe probiotics, anti-diarrheal meds (rarely in young kids), or test for infections like rotavirus or parasites.
What does a pediatrician recommend for treating diaper rash in babies?
A pediatrician will first check for yeast infections (red, satellite lesions) or irritation from stool/urine, then advise frequent diaper changes, barrier creams (zinc oxide), and air-drying. For yeast rashes, they may prescribe antifungal creams (e.g., clotrimazole). Severe or persistent rashes could signal allergies or other conditions needing further evaluation.
What will a pediatrician do if a baby has reflux?
A pediatrician will confirm reflux (spitting up, arching back) and rule out GERD or complications like poor weight gain. They may recommend feeding adjustments (smaller, more frequent meals; thickening formula), keeping the baby upright after feeds, and avoiding overstimulation. Severe cases (with vomiting, pain, or failure to thrive) might require acid-reducing meds or referral to a gastroenterologist.
What treatments does a pediatrician use for croup in children?
A pediatrician will assess the child’s breathing (stridor, barking cough) and recommend cool mist, steam, or humidified air to ease symptoms. For moderate-severe croup, they may prescribe a single dose of oral dexamethasone (a steroid) to reduce swelling. Severe cases with respiratory distress require immediate ER care, possibly with nebulized epinephrine or hospitalization.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.