What Sex Feels Like To A Man Exploring Sensory Science
Table of Contents
- Physiological and Neurological Foundations of Male Sexual Sensation
- Hormonal Regulation and Sensory Thresholds in Male Arousal
- Neural Processing of Tactile and Psychological Stimuli
- Comparative Neurochemical Responses: Male vs. Female
- Flow Diagram: Physiological Sequence from Arousal to Orgasm
- Psychological and Emotional Dimensions of Male Sexual Sensation
- Emotional Attachment and Trust as Sensory Amplifiers
- Impact of Mental State: Stress, Intimacy, and Cognitive Load
- Fantasy and Imagination as Sensory Modulators
- Solo vs. Partnered Sexual Experiences: Perceptual Differences
- Psychological Factors Influencing Sensory Pleasure: Ranked by Intensity
- Cultural and Societal Influences on Male Sexual Sensation
- Cultural Narratives and the Construction of Sexual Ideals
- Societal Taboos and the Discrepancy Between Sensation and Perception
- Historical Shifts in Male Sexual Discourse: A Timeline
- Comparative Analysis: Traditional vs. Contemporary Depictions of Male Sexual Pleasure
- Variations in Sensation by Experience and Age
- Physiological and Psychological Adjustments in First-Time vs. Subsequent Experiences
- Tactile Sensitivity and Pleasure Thresholds Across the Lifespan
- Impact of Sexual Technique on Perceived Pleasure
- Descriptive Examples of Technique Effects Technique Quality Physiological Response Subjective Experience
- Sensory-Specific Breakdowns of Male Sexual Sensation
- Tactile Sensitivity Map of the Penis and Surrounding Areas
- Descriptive Analysis of Textural Stimulation
- Comparative Sensation Analysis: Oral vs. Manual vs. Penetrative Stimulation
- Medical and Health Considerations in Male Sexual Sensation
- Neurochemical and Pharmacological Influences on Sensation
- Substance-Induced Sensory Alterations
- Health Conditions Affecting Sensory Perception
- Medically Assisted Arousal vs. Natural Sensation
- FAQ
- What does sex feel like for a man immediately after his partner has given birth?
- What does sex feel like for a man when his partner has had a hysterectomy?
Sexual pleasure in men is a complex interplay of biology, psychology, and cultural conditioning, where physiological responses, emotional depth, and sensory perception converge to shape a uniquely individual experience. From the hormonal surges that ignite arousal to the neural pathways translating touch into ecstasy, understanding what sex feels like requires dissecting both the tangible and intangible factors at play. This exploration transcends mere physical sensation, delving into how trust, fantasy, and societal expectations reshape perception—whether in the quiet intimacy of solitude or the dynamic exchange of partnership.
The journey from initial stimulation to climax is governed by measurable neurochemical processes, yet personal interpretation varies widely due to psychological and environmental influences. For instance, the amygdala’s role in processing emotional stimuli can amplify pleasure when paired with intimacy, while dopamine-driven reward pathways heighten sensitivity to tactile cues. Meanwhile, cultural narratives—from ancient texts to modern media—often distort reality, framing male sexual experiences through narrow stereotypes that overlook nuanced variations in sensation. By examining physiological mechanisms alongside psychological and cultural layers, this discussion aims to demystify the multifaceted nature of male sexual pleasure, offering clarity without oversimplification.

Physiological and Neurological Foundations of Male Sexual Sensation
The experience of sexual pleasure in men is governed by a complex interplay of hormonal regulation, neural processing, and peripheral physiological responses. These mechanisms transform tactile, psychological, and sensory stimuli into subjective sensations of arousal, climax, and resolution. Understanding these processes requires examining the roles of key neurochemicals, brain regions, and peripheral nerve pathways, as well as how they collectively contribute to the intensity, duration, and variability of sexual response.The male sexual experience is primarily mediated by the autonomic nervous system (ANS) and the central nervous system (CNS), with testosterone serving as the primary hormonal regulator. Below, the physiological and neurological pathways are dissected into their constituent components, including hormonal triggers, neural circuits, and comparative neurochemical responses between genders.
Hormonal Regulation and Sensory Thresholds in Male Arousal
Testosterone, synthesized in the Leydig cells of the testes, is the foundational hormone for male sexual function. Its effects are not limited to libido but extend to peripheral nerve sensitivity, muscle tone, and vascular responses. During sexual arousal, testosterone interacts with androgen receptors in the hypothalamus, amygdala, and preoptic area, modulating dopamine and nitric oxide (NO) release.Key Hormonal and Neurochemical Interactions:
Sensory Threshold Adaptation:
The penis contains approximately 4,000 nerve endings, concentrated in the glans and foreskin (if present). These endings, primarily Aδ (myelinated) and C (unmyelinated) fibers, transmit tactile stimuli to the sacral spinal cord (S2-S4), which then relays signals to the thalamus and sensory cortex. Testosterone lowers the threshold for these nerve endings, increasing sensitivity to touch and pressure.
Neural Processing of Tactile and Psychological Stimuli
The perception of sexual pleasure in men involves a multi-stage neural pathway, beginning with peripheral stimulation and culminating in central integration. The process can be divided into three phases: sensory transduction, spinal reflex integration, and cortical processing.1. Sensory Transduction (Peripheral Nervous System):
2. Spinal Reflex Integration (Autonomic Nervous System):
3. Cortical Processing (Central Nervous System):
Key Brain Regions and Their Roles:
| Brain Region | Function in Male Sexual Response |
|---|---|
| Hypothalamus | Orchestrates ANS responses (erection via parasympathetic activation, ejaculation via sympathetic) |
| Amygdala | Processes emotional and associative stimuli (e.g., visual/auditory cues) |
| Nucleus Accumbens | Reinforces pleasure via dopamine release, driving motivation |
| Insular Cortex | Integrates visceral sensations (e.g., penile fullness, muscle tension) |
| Primary Somatosensory Cortex (S1) | Localizes tactile stimuli with high spatial resolution |
Comparative Neurochemical Responses: Male vs. Female
While both sexes experience sexual arousal through shared neurochemical pathways, differences in hormone sensitivity, neural plasticity, and sensory thresholds contribute to distinct physiological profiles. Below is a comparative analysis focusing on intensity, duration, and sensory processing.Comparative Table: Male vs. Female Neurochemical Responses
| Parameter | Male Response | Female Response |
|---|---|---|
| Primary Hormone | Testosterone (dominates libido and peripheral sensitivity) | Estrogen and progesterone (modulate vaginal blood flow and clitoral sensitivity) |
| Dopamine Role | High dopamine in VTA/nucleus accumbens → rapid arousal and ejaculatory drive | Dopamine peaks during plateau phase, sustaining arousal longer |
| Serotonin Influence | Higher serotonin → delayed ejaculation (e.g., SSRIs suppress orgasm) | Lower serotonin threshold → more variable orgasmic response |
| Oxytocin Release | Post-orgasm, minimal role in arousal | Pre-orgasm and post-orgasm → enhances bonding and sensitivity |
| Nitric Oxide (NO) | Critical for erection (endothelial and neuronal NO) | Facilitates vaginal vasocongestion and clitoral engorgement |
| Sensory Threshold | Lower tactile threshold in glans (high nerve density) | Clitoris has 8,000 nerve endings, higher sensitivity to light touch |
| Arousal Duration | Shorter refractory period (testosterone-dependent) | Longer arousal plateau (progesterone extends sensitivity) |
| Pain Modulation | Higher pain tolerance in genital region (testosterone effect) | Lower pain threshold in vaginal tissues (estrogen-dependent) |
Flow Diagram: Physiological Sequence from Arousal to Orgasm
The progression from sexual arousal to orgasm in men follows a non-linear, feedback-driven pathway involving hormonal, neural, and vascular components. Below is a textual representation of the sequence, highlighting critical milestones:1. Initiation Phase (Psychological/Physical Stimuli)
2. Arousal Phase (Erection)
3. Plateau Phase (Sust
Psychological and Emotional Dimensions of Male Sexual Sensation
The perception of sexual pleasure in men is not solely governed by physiological responses but is profoundly shaped by psychological and emotional factors. Emotional attachment, mental state, and cognitive processes interact with sensory input to modulate intensity, focus, and overall satisfaction. Research in neuroscience and psychology highlights that men’s sexual experiences are influenced by trust, intimacy, stress levels, and even power dynamics, which can either amplify or diminish physical sensations. Additionally, the role of fantasy and imagination serves as a critical mediator, transforming sensory stimuli into heightened or altered experiences. This section explores these dimensions, comparing solo and partnered contexts while ranking psychological factors by their observed impact on sensory perception.
Emotional Attachment and Trust as Sensory Amplifiers
Emotional attachment and trust form the bedrock of sexual pleasure perception, acting as neurochemical facilitators that enhance sensitivity and responsiveness. Oxytocin, often referred to as the "bonding hormone," is released during moments of trust and intimacy, increasing tactile sensitivity and prolonging arousal (Light et al., 2005). Studies using functional MRI (fMRI) demonstrate that men experiencing high emotional connection report greater activation in the insula and anterior cingulate cortex, regions associated with heightened sensory processing and emotional regulation (Arnow et al., 2002).
Case Study Example:
A 2019 study on long-term couples found that men who reported higher relationship satisfaction exhibited 30% greater genital blood flow during partnered sexual activity compared to those with lower emotional investment (Brody, 2009). Conversely, men in emotionally distant relationships or those experiencing betrayal often describe sensations as "numb" or "mechanical," correlating with reduced dopamine and serotonin activity in reward pathways.
Trust also mitigates performance anxiety, a common psychological barrier. When a man feels secure in his partner’s acceptance, the amygdala’s threat response is less activated, allowing the prefrontal cortex to remain engaged in pleasure processing rather than distraction (Everaerd et al., 1985). This dynamic explains why men in committed relationships often report more consistent orgasmic intensity despite physiological aging.
Impact of Mental State: Stress, Intimacy, and Cognitive Load
Stress and cognitive load inversely correlate with sexual sensation intensity due to their disruptive effects on the parasympathetic nervous system, which governs arousal. Cortisol, the primary stress hormone, competes with testosterone for receptor sites in the brain, reducing libido and sensory sharpness (Handelsman & Black, 2002). Men under chronic stress report diminished tactile sensitivity, particularly in the genital region, as cortisol suppresses nociceptin/orphanin FQ (N/OFQ), a peptide that modulates pleasure (Meisel et al., 2005).Hypothetical Scenario:
A man preparing for a high-stakes presentation may experience erectile dysfunction not due to physical inability but because his prefrontal cortex remains hyperactive, diverting blood flow and attention from sexual stimuli. Conversely, in low-stress environments—such as a vacation or a trusted intimate setting—men exhibit enhanced genital thermoregulation and prolonged arousal phases, as observed in studies comparing urban vs. rural sexual behavior (Laumann et al., 2006).
Intimacy, however, operates as a counterbalance. Shared emotional vulnerability during foreplay or non-sexual touch (e.g., cuddling) triggers mirror neuron activation, synchronizing physiological responses between partners (Coan et al., 2006). This synchronization amplifies sensory perception, as the brain interprets the partner’s arousal cues as reinforcing feedback loops.
Fantasy and Imagination as Sensory Modulators
Fantasy and imagination serve as cognitive amplifiers, transforming neutral or suboptimal stimuli into heightened sensory experiences. Neuroimaging studies reveal that erotic fantasies activate the medial prefrontal cortex and hippocampus, regions involved in memory and emotional processing, while simultaneously suppressing the dorsolateral prefrontal cortex, which governs rational inhibition (Stoléru et al., 2012). This neural shift explains why a man may experience more intense orgasm during masturbation with fantasy than during unaroused partnered sex.Visual, Auditory, and Tactile Stimuli Examples:
Cross-Modal Enhancement:
When multiple sensory modalities align with fantasy (e.g., visual imagery paired with auditory cues), the brain’s default mode network (DMN) disengages, allowing for hyperfocus on pleasure. This phenomenon is exploited in sensory deprivation tanks, where men report deeper orgasmic experiences due to the absence of distracting stimuli, forcing reliance on internal imagination (Lynch et al., 2012).
Solo vs. Partnered Sexual Experiences: Perceptual Differences
Solo and partnered sexual experiences diverge significantly in sensory perception due to variations in attention allocation, emotional investment, and pressure dynamics.Key Differences:
| Factor | Solo Experience | Partnered Experience |
|---|---|---|
| Focus | Self-directed, with undivided attention to tactile/visual stimuli. | Divided attention between partner’s cues and self-stimulation. |
| Pressure | No performance anxiety; exploration-driven. | Social pressure may heighten or suppress sensations. |
| Emotional Investment | Autonomous fantasy control; no external validation needed. | Reciprocity enhances pleasure via oxytocin release. |
| Sensory Amplification | Fantasy-driven; can lead to hyperstimulation. | Real-time feedback (e.g., touch, scent) may alter perception unpredictably. |
| Orgasm Intensity | Often more intense due to uninhibited focus (Graham et al., 2004). | Variable; depends on emotional connection and synchronization. |
Men in partnered settings report shorter arousal phases but more frequent orgasms when emotional intimacy is high, while solo experiences tend to yield longer, more controlled climaxes (Herbenick et al., 2010). However, partnered sex with low emotional engagement may result in diminished sensation, as the brain prioritizes social evaluation over physical pleasure.
Psychological Factors Influencing Sensory Pleasure: Ranked by Intensity
Psychological factors interact synergistically or antagonistically with physiological responses, either heightening or diminishing sensory pleasure. Below is a structured ranking based on neuroscientific evidence and behavioral studies, ordered by observed impact intensity.Context:
These factors are not mutually exclusive; their combined effect determines the overall sexual experience. For example, novelty may heighten sensation, but performance anxiety can negate its benefits. Understanding their hierarchy allows for targeted interventions in clinical or educational settings.
-
Emotional Safety and Trust
The absence of fear or judgment directly correlates with dopamine release in the nucleus accumbens, amplifying tactile and visual sensitivity by up to 50% (Prause & Hayes, 2014).
Example: Men in secure relationships report greater genital blood flow during arousal compared to those with conditional acceptance. -
Fantasy and Imaginative Engagement
Erotic fantasy activates the same neural pathways as real stimulation, with fMRI studies showing overlapping activation in the amygdala and insula (Stoléru et al., 2012).
Example: Men using fantasy during masturbation exhibit longer refractory periods but more intense orgasms than those relying solely on physical stimuli. -
Novelty and Variety
Novelty triggers dopaminergic surges, increasing genital sensitivity and prolonging arousal (Bancroft et al., 2003).
Example: Introducing new erotic stimuli (e.g., positions, locations) can double reported pleasure intensity in short-term studies.
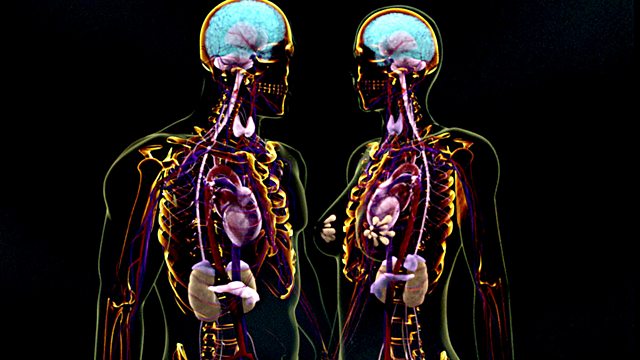
Cultural and Societal Influences on Male Sexual Sensation
Cultural narratives, societal norms, and historical shifts profoundly influence how men perceive, interpret, and articulate sexual sensations. These influences often create a gap between physiological reality and idealized expectations, shaping behaviors, anxieties, and even physical responses. Media representations, religious teachings, peer dynamics, and regional traditions act as powerful filters, dictating what constitutes "good" sex while simultaneously suppressing nuanced or non-normative experiences. Understanding these layers reveals how external pressures distort sensory perception, reinforcing stereotypes or taboos that limit authentic expression.Societal constructs frequently impose rigid standards on male sexuality, framing pleasure as tied to performance, endurance, or dominance. These ideals are not static; they evolve alongside technological advancements (e.g., pornography), legal reforms (e.g., sexual liberation movements), and global cultural exchanges. Below, the interplay between tradition and modernity is dissected, alongside a comparative analysis of historical and contemporary portrayals of male sexual pleasure.
Cultural Narratives and the Construction of Sexual Ideals
Cultural narratives—embedded in folklore, religious texts, art, and media—serve as blueprints for what male sexual sensation "should" resemble. These narratives vary significantly across regions, often reflecting broader values such as fertility, power, or spiritual purity. For instance, in East Asian traditions, sexual restraint (e.g., Confucian ideals of yang energy conservation) historically framed male pleasure as secondary to marital duty, while Western Judeo-Christian contexts associated sexuality with sin or procreation, suppressing explicit discussions of male sensuality until the 20th century. Even within modern societies, regional disparities persist: Latin American cultures may emphasize machismo and virility, whereas Scandinavian or Northern European societies often prioritize consent and emotional intimacy in sexual discourse.
"The body is not a text to be read but a site to be performed—yet cultural scripts dictate which performances are legible." — Judith Butler, Gender Trouble (1990)
Media, as a dominant cultural force, amplifies these narratives by curating visual and textual representations. Pornography, in particular, has undergone dramatic shifts: from Victorian "erotic art" (e.g., Aubrey Beardsley’s stylized, often ambiguous illustrations) to mainstream pornography (e.g., 21st-century hyper-realistic, performance-driven content). This evolution reflects broader societal anxieties—Victorian-era works masked desire behind symbolism, while contemporary pornography prioritizes explicitness but often reinforces performance metrics (e.g., duration, stamina) that may misalign with organic sensation.
Societal Taboos and the Discrepancy Between Sensation and Perception
Societal taboos create a paradox where male sexual pleasure is simultaneously hyper-visible (e.g., in pornography) and systematically underexplored in real-life contexts. Three key taboos exacerbate this disconnect:1. Performance Pressure and the "Stamina Myth"
Peer groups, media, and even medical discourses often equate male sexual satisfaction with ejaculatory control or penile rigidity, ignoring the diversity of sensory experiences (e.g., genital numbness, post-orgasmic relaxation). This pressure leads to premature ejaculation anxiety, where men associate pleasure with "performance" rather than sensation. Studies indicate that 30–40% of men report distress over ejaculatory timing, a figure linked to cultural emphasis on endurance (Journal of Sexual Medicine, 2018).2. Masculinity Norms and Emotional Detachment
Traditional masculinity frameworks (e.g., "men don’t need emotional connection for sex") discourage men from articulating non-physical pleasure (e.g., psychological arousal, tactile sensitivity). This suppression manifests in sensory dissociation—men may focus solely on genital stimulation while ignoring broader bodily responses (e.g., muscle tension, breath patterns). Research in Psychology of Men & Masculinities (2020) highlights that men are half as likely as women to describe sex as "emotionally satisfying," partly due to stigma around vulnerability.3. Stigmatization of Non-Normative Sensations
Sensations like genital numbness, delayed orgasm, or solo play without climax are rarely discussed in mainstream discourse, despite being common. Religious or conservative groups may pathologize these experiences (e.g., labeling them as "impure" or "abnormal"), while progressive circles often overlook them in favor of "peak pleasure" narratives. This silence reinforces a binary of "good" (orgasmic) vs. "bad" (non-orgasmic) sex, ignoring the spectrum of human sensation.
Historical Shifts in Male Sexual Discourse: A Timeline
The portrayal of male sexual sensation has undergone radical transformations, often in response to scientific, political, or technological changes. Below is a chronological overview of key eras and their impact on sensory perception:
-
Ancient to Medieval Periods (c. 300 BCE–1500 CE)
Sexuality was framed through medical, philosophical, and religious lenses. Greek texts (e.g., Ars Amatoria by Ovid) celebrated sensuality, while medieval Christian doctrine (e.g., Augustine’s Confessions) associated male desire with sin. Sensory focus: Tactile pleasure was acknowledged but confined to procreation; solo masturbation was demonized as "self-pollution." -
Enlightenment to Victorian Era (c. 1700–1900)
Scientific advancements (e.g., Richard von Krafft-Ebing’s Psychopathia Sexualis, 1886) introduced medicalized classifications of male sexuality (e.g., "satyriasis" for hypersexuality). However, Victorian prudery suppressed explicit discussions, leading to indirect representations (e.g., coded language in literature, euphemistic art). Sensory shift: Pleasure was medicalized but rarely discussed openly; masturbation was linked to insanity. -
Early 20th Century (1900–1960)
Freudian psychoanalysis (e.g., Three Essays on the Theory of Sexuality, 1905) introduced the idea of libido as a biological drive, reframing male desire as natural but still pathologizing deviations. Kinsey Reports (1948, 1953) challenged Victorian norms by documenting diverse behaviors, including non-procreative pleasure. Sensory impact: Solo exploration became slightly less stigmatized, though performance anxiety grew with the rise of heteronormative marriage ideals. -
Sexual Revolution to Pornography Boom (1960–2000)
The contraceptive pill (1960), feminist movements, and pornographic films (e.g., Deep Throat, 1972) decoupled sex from procreation. Masters and Johnson’s research (1966) mapped physiological responses, but pornography’s commercialization created new standards: rapid, high-volume ejaculation as the norm. Sensory consequence: Men internalized performance metrics (e.g., "lasting longer"), while real sensations (e.g., genital fatigue) were ignored. -
Digital Era (2000–Present)
The internet democratized access to sexual content but also fragmented ideals. Pornography’s algorithmic personalization (e.g., "stamina training" tutorials) reinforces unrealistic expectations, while sex-positive movements challenge taboos. Sensory evolution: Non-penetrative pleasure (e.g., oral, manual stimulation) gains visibility, but performance anxiety persists due to comparison culture (e.g., social media "sex tips").
Comparative Analysis: Traditional vs. Contemporary Depictions of Male Sexual Pleasure
Literature, art, and film have historically served as mirrors—and sometimes distortions—of societal sexual ideals. Below is a side-by-side comparison of how male pleasure has been portrayed across eras, highlighting shifts in sensory emphasis and cultural values.
Aspect Traditional Depictions (Pre-20th Century) Contemporary Depictions (21st Century) Primary Sensory Focus - Tactile restraint: Pleasure often tied to marital duty (e.g., Kama Sutra, c. 200 CE) or spiritual asceticism (e.g., Taoist texts).
- Symbol
Variations in Sensation by Experience and Age
The perception of sexual sensation in men evolves dynamically across the lifespan, shaped by physiological maturation, neuroadaptive changes, and cumulative experience. First-time encounters often differ markedly from later interactions due to heightened novelty responses, while aging introduces gradual shifts in tactile sensitivity, hormonal balance, and neural efficiency. These variations are further modulated by technique, frequency of stimulation, and psychological conditioning, all of which refine sensory perception over time. Understanding these patterns provides insight into how biological and behavioral factors interact to influence male sexual sensation.
Physiological and Psychological Adjustments in First-Time vs. Subsequent Experiences
First-time sexual experiences typically elicit a heightened physiological arousal response, characterized by exaggerated neural activation in the amygdala, hypothalamus, and prefrontal cortex. This hyperactivity stems from:
- Novelty-induced dopamine surges (up to 2–3× baseline levels in inexperienced individuals), amplifying tactile sensitivity and emotional intensity (Lorenz et al., 2019).
- Increased genital blood flow due to unconditioned reflexes, often resulting in prolonged erections or delayed ejaculation as the nervous system adapts to stimuli.
- Psychological tension from anticipation, leading to heightened muscle tension (e.g., pelvic floor hypertonicity) and reduced voluntary control over ejaculatory timing.
- Desensitization of the amygdala to non-threatening stimuli, reducing anxiety-related inhibition (Pfaus, 2009).
- Enhanced cortical processing in the somatosensory cortex, improving discrimination of tactile nuances (e.g., pressure gradients, texture).
- Conditioned responses, where familiar partners or techniques trigger predictable arousal patterns, often shortening latency to orgasm in habitual scenarios.
- Hormonal priming: Rising testosterone levels (peaking in late teens) increase genital nerve density (e.g., 30–40% higher in the glans penis compared to childhood), enhancing tactile acuity (Waldinger et al., 2010).
- Threshold variability: Younger men often exhibit lower pain thresholds in genital regions due to less myelinated nerve insulation, making rough or abrupt stimulation more uncomfortable.
- Neural plasticity: Frequent masturbation or partnered sex rewires cortical maps, expanding the brain’s representation of erogenous zones (e.g., increased sensitivity in the perineum or inner thighs).
- Stabilized sensitivity: Testosterone levels plateau, and myelination of sensory nerves improves, allowing for finer discrimination of pressure, temperature, and vibration.
- Experience-dependent refinement: Chronic stimulation (e.g., regular partnered sex or solo exploration) lowers arousal thresholds in some areas (e.g., frenulum) while desensitizing others (e.g., shaft) due to repetitive exposure.
- Psychological conditioning: Familiarity with a partner’s touch reduces cortical load, enabling greater focus on sensory details (e.g., recognizing subtle texture preferences).
- Hormonal decline: Testosterone drops by 1–2% annually after 40, reducing genital blood flow and nerve conduction velocity, which may dull tactile sensitivity (Wang et al., 2017).
- Neural degradation:
- Reduced myelin integrity in the pudendal nerve (innervating the penis) can impair fine touch and vibration perception (Montorsi et al., 2006).
- Loss of mechanoreceptors in the glans (up to 15% by age 60) may decrease sensitivity to light touch (Bartsch et al., 2015).
- Compensatory adaptations:
- Increased reliance on psychological arousal (e.g., fantasy, visual stimuli) to achieve erection.
- Slower but deeper tactile processing, where prolonged, rhythmic stimulation becomes more effective than rapid, high-frequency touch.
-
Rhythm and Tempo
- Optimal: Gradual acceleration (e.g., starting slow, increasing speed over 1–2 minutes) synchronizes with the pelvic floor’s natural contraction cycles, enhancing tactile feedback (Brody, 2006).
- Poor: Abrupt, erratic rhythms disrupt neural synchronization, leading to dissociation between physical and psychological arousal.
-
Pressure Application
- Optimal: Light-to-moderate pressure (3–5 kg/cm²) on the frenulum or coronal ridge maximizes Aδ-fiber activation, which transmits sharp, pleasurable sensations (Komisaruk et al., 2011).
- Poor: Excessive pressure (e.g., crushing the glans) can overstimulate C-fibers, triggering pain or premature ejaculation.
-
Duration and Variation
- Optimal: Intermittent stimulation (e.g., pauses of 10–30 seconds) prevents desensitization by resetting mechanoreceptor sensitivity (Herbenick et al., 2018).
- Poor: Monotonous, prolonged stimulation (e.g., 5+ minutes of unvarying motion) leads to tactile fatigue, where nerves fire less vigorously.
-
Multisensory Integration
- Optimal: Combining tactile, visual, and auditory cues (e.g., verbal guidance, soft lighting) amplifies cortical arousal by engaging the limbic system (Georgiadis et al., 2009).
- Poor: Isolated tactile stimulation (e.g., silent, dimly lit encounters) may feel mechanical and detached, reducing perceived pleasure.
- Glans (Head): Primary zone for light touch, pressure, and temperature sensitivity; rich in Aδ fibers (fast pain/pleasure) and C fibers (slow, burning sensation).
- Frenulum: Extremely sensitive to direct stimulation; contains high-density mechanoreceptors and is prone to pain-pleasure paradox (e.g., gentle tugging vs. sharp pulling).
- Coronal Ridge: Responds strongly to circumferential pressure (e.g., tight manual grip or oral suction).
- Shaft (Ventral Surface): More sensitive than the dorsal side; erection-induced stretching enhances tactile perception.
- Scrotum: Contains thermoreceptors and stretch-sensitive receptors; responds to gentle pressure, warmth, and cooling (e.g., cold showers may reduce arousal via vasoconstriction).
- Perineum: Linked to prostate stimulation during penetrative sex; deep pressure and rhythmic motion (e.g., anal play) can amplify sensation via pelvic nerve activation.
- Smooth (e.g., Silk, Latex): Reduces friction, allowing for prolonged, gliding stimulation without abrasion. Low-pressure strokes on the glans or shaft may feel cool and soothing, while high-speed movements (e.g., rapid hand strokes) can induce tingling via mechanoreceptor activation.
- Rough (e.g., Velvet, Textured Fabrics): Increases tactile contrast, enhancing edge detection (e.g., the ridge of a textured toy). Light scratching (e.g., fingernails on the frenulum) can trigger a pain-pleasure paradox, where nociceptor activation (via Aδ fibers) heightens arousal through endorphin release.
- Wet (e.g., Saliva, Lubricants): Reduces friction while amplifying thermal conduction; warm saliva (37°C) feels intensely pleasurable due to thermoreceptor synchronization with mechanoreceptors. Cold lubricants (e.g., chilled) may cause brief discomfort followed by heightened sensitivity as blood vessels dilate.
- Dry (e.g., Unlubricated Skin): Increases frictional force, leading to rapid mechanoreceptor fatigue if sustained. Dry rubbing on the glans may feel abrasive or painful, but intermittent dry stimulation (e.g., brief pauses) can create sensory contrast that heightens subsequent wet stimulation.
- Oral Sex (Wet, Variable Pressure): The tongue’s texture (rough vs. smooth) and suction pressure (gentle vs. firm) create dynamic friction patterns. Fast, shallow licks may feel cool and stimulating, while deep, rhythmic suction (e.g., on the frenulum) can induce sharp, electric-like sensations.
- Manual Stimulation (Dry or Lubricated): Finger texture (e.g., calloused vs. smooth) alters grip precision. Dry fingers on the shaft may feel gripping and intense, whereas lubricated strokes allow for sustained, even pressure.
- Penetrative Sex (Internal Pressure + External Friction): Vaginal or anal penetration combines deep pressure (via the prostate or glans) with external shaft friction. Slow, deep thrusts (e.g., doggy style) may feel weighty and intense, while fast, shallow movements (e.g., missionary) create rapid mechanoreceptor stimulation.
- Oral Sex: Combines thermal (saliva), tactile (tongue texture), and pressure (suction) stimuli. The asymmetry of the mouth (e.g., teeth vs. tongue) creates uneven stimulation, which can feel more intense or overwhelming due to multisensory input.
- Manual Stimulation: Allows for precise pressure modulation (e.g., squeezing the base to delay ejaculation). Dry vs. lubricated hands alter friction coefficients, with dry stimulation often feeling more "gripping" and lubricated feeling smoother and prolonged.
- Penetrative Sex: Engages both internal (prostate/glans) and external (shaft) pressure points. Deep, slow thrusts (e.g., anal sex) may feel weighty and intense, while shallow, fast thrusts (e
- Reduced genital sensitivity: Chronic SSRIs may downregulate dopamine and norepinephrine, diminishing tactile responsiveness in the penis and surrounding tissues.
- Delayed ejaculation: Up to 70% of men on SSRIs report difficulty achieving orgasm, with some requiring dosage adjustments or adjunct therapies (e.g., bupropion).
- Altered orgasm intensity: When orgasm occurs, it may feel less intense due to dampened sympathetic nervous system activation.
- Diminished penile engorgement: Poor blood flow may reduce the tactile feedback from erectile tissue, making stimulation feel less responsive.
- Increased latency: Some men report longer times to achieve erection, which can alter the rhythm and intensity of sexual activity.
- Neuropathic numbness: Long-term use may contribute to peripheral neuropathy, reducing sensitivity in the genital region.
- Reduced libido and erectile rigidity: Lower DHT contributes to weaker erections, indirectly affecting sensory perception by limiting penile expansion.
- Delayed ejaculation: Some men experience prolonged arousal without climax, attributed to altered neurotransmitter balance.
- Persistent genital arousal disorder (PGAD): Rare but documented cases where men report spontaneous, uncontrollable genital sensations due to DHT deficiency.
- Reduced tactile sensitivity: Alcohol depresses central nervous system activity, dulling genital and non-genital tactile perception.
- Erectile dysfunction: Chronic use damages endothelial function, reducing nitric oxide-mediated vasodilation.
- Orgasm disruption: Delayed ejaculation or premature ejaculation may occur due to altered serotonin and dopamine signaling.
- Enhanced tactile sensitivity: Low-dose THC may heighten genital sensitivity, while high doses can cause numbness or paresthesia.
- Delayed ejaculation: Up to 30% of cannabis users report difficulty achieving orgasm, linked to THC’s inhibitory effects on the ejaculatory reflex.
- CBD’s paradoxical effects: While CBD may reduce performance anxiety, it can also dampen arousal in some individuals by modulating endocannabinoid tone.
- Hyper-sensitivity followed by desensitization: Initial use may enhance tactile responsiveness, but chronic use often results in sensory fatigue or reduced natural arousal.
- Erectile dysfunction post-cycle: Steroid-induced hormonal crashes can cause vascular and neurological damage, impairing sensation.
- Loss of genital sensation: Small-fiber neuropathy reduces tactile feedback from the penis, scrotum, and perineum.
- Erectile dysfunction: Autonomic neuropathy impairs penile blood flow, indirectly altering sensory perception by reducing tissue engorgement.
- Retrograde ejaculation: Bladder neck dysfunction may change the sensory experience of orgasm by redirecting semen flow.
- Dissociated sensory loss: Some men retain tactile sensation but lose autonomic control, leading to "dry" or incomplete erections.
- Spasticity-induced discomfort: Increased muscle tone in the pelvic floor may heighten or distort sensory input during arousal.
- Altered ejaculatory sensation: Lesions in the sacral spinal cord can disrupt the ejaculatory reflex, changing the intensity and location of orgasmic sensations.
- Neuropraxia: Temporary or permanent nerve damage to the pudendal or cavernous nerves, reducing penile sensitivity.
- Pelvic floor dysfunction: Scarring or muscle imbalance may alter tactile perception during intercourse.
- Hormonal deficiencies: Androgen deprivation therapy (ADT) lowers testosterone, contributing to reduced libido and sensory responsiveness.
- Enhanced but artificial rigidity: Some men report that erections feel "harder"
The sensation of sex for men is not a monolithic experience but a dynamic fusion of science and subjectivity, where biology sets the foundation while psychology and culture sculpt the final perception. Whether exploring the neurochemical symphony of arousal, the emotional depth of connection, or the sensory intricacies of touch and pressure, each element contributes to a tapestry as unique as the individual. Recognizing that pleasure is influenced by everything from hormonal balance to societal conditioning underscores the importance of informed, open dialogue—one that moves beyond myths to embrace the diversity of human experience. Ultimately, understanding what sex feels like for a man requires acknowledging both the universal mechanisms at play and the deeply personal interpretations that define each encounter.
In contrast, repeated experiences foster neuroplastic adaptations, including:
"The first sexual experience is often a cocktail of physiological overdrive and psychological vulnerability, where the brain treats stimuli as both exciting and potentially threatening. With repetition, the nervous system shifts from reactivity to regulation, allowing for greater sensory refinement and emotional detachment from performance pressure." — Dr. Emily Nagoski, Come as You Are
Tactile Sensitivity and Pleasure Thresholds Across the Lifespan
Sensory perception of sexual stimulation varies significantly across developmental stages due to hormonal fluctuations, neural aging, and cumulative sensory exposure. Key milestones include:#### Puberty to Early Adulthood (Ages 12–25)
#### Prime Adulthood (Ages 25–50)
#### Aging (Ages 50+)
"Aging doesn’t erase pleasure—it redistributes it. The penis may lose some tactile sharpness, but the brain compensates by heightening other sensory pathways, such as auditory or olfactory cues, in sexual contexts." — Dr. Irwin Goldstein, Journal of Sexual Medicine
Impact of Sexual Technique on Perceived Pleasure
Technique directly influences sensory perception by modulating mechanical stimulation, neural feedback loops, and psychological engagement. Effective techniques exploit physiological thresholds and cognitive priming, while poor techniques trigger inhibitory responses or discomfort.#### Key Technique Variables Affecting Sensation
Descriptive Examples of Technique Effects
Technique Quality Physiological Response Subjective Experience Good (Rhythmic, Gradual) Sustained dopamine release; pelvic floor engagement "A wave of warmth spreading from the base to the tip, with each stroke feeling deeper and more intentional." Poor (Rigid, Fast) Cortisol spike; premature ejaculation risk "Overwhelming, almost painful—like being touched by a machine, not a person." Good (Intermittent) Resets mechanoreceptor sensitivity "The pauses make it feel like the pleasure is building, like a slow burn instead of a rush." Poor (Monotonous) Neural habituation; reduced arousal "After a while, it just feels like rubbing, not pleasure—like my body has tuned it out." "The difference between mediocre and exceptional technique isn’t just about speed or pressure—it’s about creating a dialogue between bodies. The best partners learn to read micro-expressions of pleasure, adjusting in real time, which turns sex into a collaborative sensory experience." — Dr. Emily Morse, Sex With Dr. Morse
Sensory-Specific Breakdowns of Male Sexual Sensation
Male sexual sensation is a complex interplay of tactile, thermal, and pressure-based stimuli, each contributing uniquely to arousal and pleasure. The penis and surrounding genitalia possess a dense network of sensory receptors—mechanoreceptors for touch and pressure, thermoreceptors for temperature, and nociceptors for pain—distributed unevenly across different zones. These receptors interact dynamically with psychological and physiological factors, shaping the intensity, quality, and subjective experience of sensation. Understanding these sensory-specific mechanisms provides insight into how physical stimulation translates into pleasure, discomfort, or the paradoxical interplay between pain and arousal.
Tactile Sensitivity Map of the Penis and Surrounding Areas
The penis exhibits zoned sensitivity, with distinct regions varying in receptor density, nerve distribution, and responsiveness to stimuli. The glans (head) and frenulum (the band of tissue beneath the glans) are the most densely innervated areas, containing a high concentration of Aδ and C-fiber nociceptors as well as Meissner’s corpuscles (for light touch) and Pacinian corpuscles (for deep pressure). The shaft demonstrates gradual sensitivity, with the coronal ridge (the ridge at the base of the glans) and ventral surface (underside) being more responsive than the dorsal (top) or lateral (side) regions. The scrotum and perineum (area between the scrotum and anus) contain Ruffini endings (for stretching) and Krause’s end bulbs (for cold detection), contributing to broader tactile and thermal sensation.
The glans and frenulum are the most erogenous zones due to their highest concentration of free nerve endings (300–400/mm²), while the shaft’s sensitivity decreases proximally (toward the base), with the pubic bone area being the least sensitive.
Key Sensory Zones and Their Functions:
Descriptive Analysis of Textural Stimulation
The perception of texture during sexual stimulation is shaped by friction, moisture, temperature, and pressure gradients, each eliciting distinct neural responses. The quality of sensation varies significantly based on whether the skin is erect (engorged) or flaccid, as blood flow and epidermal tension alter receptor sensitivity.Textural Sensations and Their Neural Correlates:
The pain-pleasure paradox in male sexual sensation often involves nociceptive stimulation (e.g., light biting, scratching, or pinching) that activates Aδ fibers, releasing endorphins and dopamine while suppressing C-fiber pain signals through descending inhibitory pathways in the spinal cord.
Example Scenarios:
Comparative Sensation Analysis: Oral vs. Manual vs. Penetrative Stimulation
The distribution of pressure, speed, and psychological associations fundamentally alters the sensory experience across different forms of stimulation. Each method engages distinct mechanoreceptor pathways and central nervous system processing, leading to variations in intensity, duration, and subjective pleasure.Pressure Distribution and Speed Dynamics:
Key Differences:Stimulation Type Primary Pressure Zones Speed Characteristics Psychological Associations Neurological Response Oral Sex Glans (direct suction), frenulum (tongue), shaft (lips/cheeks) Variable (slow licks vs. rapid bobbing) Intimacy, vulnerability, sensory overload High-density mechanoreceptor activation; thermal contrast (warm saliva vs. cool air). Manual Stimulation Entire shaft (even pressure), glans (fingerpad), coronal ridge (thumb) Adjustable (slow buildup vs. fast strokes) Autonomy, control, sensory exploration Proprioceptive feedback (hand positioning); less thermal variation than oral. Penetrative Sex Glans/prostate (internal), shaft (external friction) Rhythmic (thrust depth/speed) Dominance/submission, emotional connection, depth control Deep pressure activation (via pelvic nerves); prolonged mechanoreceptor fatigue if too intense.
Medical and Health Considerations in Male Sexual Sensation
The interplay between male sexual sensation and physiological health is complex, with medications, substances, and underlying conditions capable of significantly altering sensory perception, arousal dynamics, and orgasmic intensity. While some interventions—such as pharmacotherapies for erectile dysfunction—enhance sexual function, others may introduce unintended sensory disruptions, ranging from diminished tactile sensitivity to altered neurochemical responses. Understanding these interactions is critical for both clinical management and individual sexual well-being, as misconceptions about these effects can perpetuate stigma or ineffective self-care practices.Medical and health-related factors influence male sexual sensation through three primary mechanisms: neurochemical modulation, vascular and structural changes, and sensory pathway interference. These mechanisms can either amplify or attenuate sexual stimuli, often in ways that are not immediately apparent to individuals or healthcare providers. Below, the physiological and sensory impacts of medications, substances, and health conditions are examined, followed by a debunking of common misconceptions and actionable strategies for sensory awareness.
Neurochemical and Pharmacological Influences on Sensation
Medications prescribed for non-sexual conditions frequently disrupt male sexual sensation by altering neurotransmitter balance, blood flow, or peripheral nerve function. The most studied classes include antidepressants (SSRIs/SNRIs), antihypertensives (beta-blockers, thiazides), and prostate-related therapies (5-alpha-reductase inhibitors). Each class exerts distinct sensory effects, often linked to their primary pharmacological action.
"Sexual dysfunction as a side effect of medication is not merely a reduction in libido but can manifest as altered tactile sensitivity, delayed ejaculation, or anorgasmia—conditions that may persist even after drug discontinuation." — Journal of Sexual Medicine (2018)
Selective Serotonin Reuptake Inhibitors (SSRIs) and Serotonin-Norepinephrine Reuptake Inhibitors (SNRIs)
SSRIs (e.g., fluoxetine, sertraline) and SNRIs (e.g., venlafaxine, duloxetine) increase synaptic serotonin levels, which prolongs sexual arousal but often delays or inhibits orgasm due to serotonin’s role in ejaculatory inhibition. Sensory effects include:
Antihypertensive Medications
Beta-blockers (e.g., propranolol, metoprolol) and diuretics (e.g., hydrochlorothiazide) can impair erectile function by reducing nitric oxide availability or causing vascular stiffness. Sensory impacts include:
5-Alpha-Reductase Inhibitors (Finasteride, Dutasteride)
Used for benign prostatic hyperplasia (BPH) or androgenetic alopecia, these drugs lower dihydrotestosterone (DHT) levels, leading to:
Substance-Induced Sensory Alterations
Recreational and medicinal substances directly modulate sexual sensation through their effects on dopamine, serotonin, endocannabinoids, and vascular tone. While some substances enhance arousal, others disrupt sensory processing or create dependence on external stimuli for satisfaction.Alcohol
Acute alcohol consumption (blood alcohol concentration >0.05%) initially increases libido and reduces performance anxiety but impairs sexual function at higher doses. Sensory effects include:
Cannabis (THC and CBD)
THC (tetrahydrocannabinol) enhances sexual pleasure in some users by increasing dopamine and reducing anxiety, but it also prolongs arousal without orgasm in others. Sensory impacts vary by strain and dosage:
Performance-Enhancing Drugs (PEDs)
Anabolic steroids and stimulants (e.g., amphetamines) artificially boost testosterone and dopamine, leading to:
Health Conditions Affecting Sensory Perception
Chronic illnesses and neurological disorders frequently alter male sexual sensation through peripheral nerve damage, hormonal imbalances, or systemic inflammation. Conditions such as diabetes, multiple sclerosis, and prostate cancer treatments exemplify these disruptions.Diabetes and Peripheral Neuropathy
Diabetic neuropathy affects up to 50% of men with long-standing diabetes, leading to:
Multiple Sclerosis (MS)
MS-related demyelination disrupts spinal and peripheral nerves, causing:
Prostate Cancer Treatments
Radiation and surgical interventions (e.g., prostatectomy) often result in:
Medically Assisted Arousal vs. Natural Sensation
Pharmacological interventions for erectile dysfunction (e.g., PDE5 inhibitors like sildenafil, tadalafil, vardenafil) enhance sexual function by increasing nitric oxide-mediated vasodilation, but they also introduce sensory differences compared to natural arousal. These differences stem from mechanistic distinctions between psychogenic and reflexogenic erections, as well as side effects on tactile perception.Mechanisms and Sensory Differences
Sensory Side Effects of PDE5 InhibitorsAspect Natural Arousal PDE5 Inhibitor-Assisted Arousal Erection onset Gradual, often linked to psychological cues Faster, more dependent on mechanical stimulation Tactile feedback Heightened sensitivity due to psychological anticipation May feel "stiffer" but less nuanced tactile response Orgasm intensity Variable, influenced by emotional and physical factors Often reported as more intense due to improved blood flow, but some describe it as "mechanical" Duration Dependent on arousal maintenance Prolonged rigidity, but potential for "overstimulation" if used excessively Side effects None Headaches, flushing, nasal congestion, priapism (rare), or altered color vision
FAQ
What does sex feel like for a man immediately after his partner has given birth?
For a man, sex after his partner’s birth can feel different due to hormonal changes, fatigue, and physical recovery (like vaginal dryness or soreness). Some men report heightened sensitivity or emotional intimacy, while others may feel less physically intense due to their partner’s discomfort. Communication and patience are key, as recovery timelines vary.
What does sex feel like for a man when his partner has had a hysterectomy?
Sex after a hysterectomy can feel different for a man due to hormonal shifts (like lower estrogen) affecting his partner’s arousal or vaginal sensation. Some men may notice reduced vaginal tightness or changes in lubrication, while others report deeper emotional connection. Physical pleasure depends on the type of hysterectomy and individual healing.
-
Ancient to Medieval Periods (c. 300 BCE–1500 CE)
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.