What Stress Tests Reveal About Resilience Across Fields
Table of Contents
- Medical and Financial Stress Test Fundamentals
- Core Purpose and Methodological Parallels
- Side-by-Side Comparison of Stress Tests
- Differences Between Stress Tests and Routine Assessments
- Cardiovascular Stress Test Insights
- Electrocardiographic Stress Testing and Coronary Artery Disease Detection
- Imaging Modalities in Stress Testing: Nuclear and Echocardiographic Techniques
- Warning Signs Detected via Stress Tests and Clinical Implications
- Step-by-Step Interpretation of Stress Test Results
- Financial Stress Test Applications in Banking Resilience
- Stress Test Scenarios and Their Financial System Impact
- Critical Financial Ratios Evaluated in Stress Tests
- Stress Test Framework: Scenarios, Impacts, and Regulatory Responses
- Case Study: Hypothetical Bank’s Stress Test Under Extreme Conditions
- Psychological and Cognitive Stress Test Revelations
- Cognitive Performance Under Stress: Task-Based Assessments
- Physiological Markers of Psychological Resilience
- Comparative Analysis: Lab-Based vs. Real-World Stress Test Methods
- Interventions Informed by Stress Test Findings
- Stress Test Limitations and Ethical Considerations
- Trade-offs Between Stress Test Accuracy and Risk Exposure
- Ethical Dilemmas in Stress Testing Vulnerable Populations
- Controversial Cases of Stress Test Failures
- Framework for Validating Stress Test Results
- Innovative Stress Test Technologies and Future Directions
- AI-Driven Stress Test Analysis and Predictive Modeling
- Non-Invasive Stress Test Techniques
- Personalized and Decentralized Stress Testing
- Comparative Analysis: Technologies, Fields, Advantages, and Challenges
- FAQ
- What can a stress test show about my heart or health?
- What can a stress test show you about your cardiovascular system?
- What does a stress test show in terms of medical results?
- What problems can a stress test show in a patient?
- What will a stress test show if my symptoms are unexplained?
- What can a nuclear stress test show that a regular stress test can’t?
Stress tests serve as critical diagnostic tools across disciplines, exposing hidden vulnerabilities in systems as diverse as human physiology and global financial markets. By simulating extreme conditions—whether physical exertion in a cardiology lab or economic crises in banking simulations—these assessments reveal weaknesses that routine evaluations often overlook. From identifying coronary artery disease through exercise-induced ECG changes to forecasting bank failures under recessionary pressures, stress tests bridge theory and real-world risk, offering actionable insights for prevention and adaptation.
Their applications extend beyond traditional domains, now encompassing psychological resilience, cognitive performance, and even emerging technologies like AI-driven financial audits. Yet, despite their transformative potential, stress tests are not without limitations, raising ethical questions about false positives, patient safety, and the unintended consequences of exposing systems to controlled adversity. Understanding what a stress test can show requires examining both its precision and its broader implications for decision-making in high-stakes environments.

Medical and Financial Stress Test Fundamentals
Stress tests serve as critical diagnostic tools across disciplines, designed to expose systemic vulnerabilities under extreme or simulated conditions. In both medicine and finance, their purpose is to identify latent risks—whether cardiac ischemia or solvency gaps—before they manifest as crises. These assessments diverge from routine evaluations by deliberately introducing controlled adversity, thereby revealing thresholds of resilience that standard operations may obscure. The methodology ensures that organizations or individuals can preemptively address weaknesses, optimizing performance under pressure.The core principle underlying stress tests is the deliberate exposure to conditions exceeding normal operational or physiological ranges. In cardiology, this translates to monitoring heart function during exertion (e.g., treadmill exercise), while in banking, it involves simulating economic downturns to assess capital buffers. Both fields rely on quantifiable metrics to gauge performance, though the variables differ significantly due to their distinct domains. Below, a comparative analysis highlights the structural and functional parallels, followed by a detailed breakdown of how stress tests distinguish themselves from conventional assessments.
Core Purpose and Methodological Parallels
The primary objective of stress tests in both medical and financial contexts is to identify vulnerabilities under extreme conditions, ensuring that systems—whether biological or institutional—can withstand unforeseen challenges. In cardiology, the test evaluates the heart’s ability to sustain increased oxygen demand, while in finance, it assesses an entity’s capacity to absorb losses during economic stress. The controlled adversity factor is essential: routine assessments (e.g., resting ECG or quarterly financial statements) may not uncover latent risks until they escalate into crises. Stress tests introduce artificial but realistic stressors to probe these limits proactively.Key methodological similarities include:
Differences arise in the nature of stressors and the variables evaluated. For example, a cardiac stress test may involve pharmacological agents (e.g., adenosine) or physical exertion, whereas a financial stress test might model scenarios like a 2008-like recession or a sudden interest rate spike. Both, however, share the goal of revealing hidden fragilities before they become systemic failures.
Side-by-Side Comparison of Stress Tests
The following table contrasts stress tests in cardiology and banking, emphasizing their key variables, methodologies, and use cases. The alignment underscores how both fields leverage controlled adversity to enhance resilience, albeit in distinct operational frameworks.| Type of Stress Test | Industry/Field | Key Variables Measured | Example Use Case |
|---|---|---|---|
| Exercise ECG (Treadmill Test) | Cardiology |
|
Diagnosing coronary artery disease (CAD) in patients with chest pain or suspected ischemia. Used to determine if symptoms warrant further invasive testing (e.g., angiography). |
| Pharmacological Stress Test (e.g., Dobutamine or Adenosine) | Cardiology |
|
Evaluating patients unable to exercise (e.g., due to mobility issues or severe COPD). Often used preoperatively to assess surgical risk. |
| Capital Adequacy Ratio (CAR) Stress Test | Banking/Finance |
|
Regulatory requirement (e.g., Basel III) for banks to demonstrate solvency during hypothetical crises. Example: The 2022 UK stress test for banks modeled a 30% house price crash. |
| Liquidity Stress Test (e.g., Dodd-Frank Act) | Banking/Finance |
|
Assessing systemic risk during events like the 2007–2008 financial crisis. Used by central banks to enforce minimum liquidity buffers. |
| Macroeconomic Scenario Analysis | Corporate Finance |
|
Mergers and acquisitions (M&A) due diligence or bond issuance approvals. Example: A tech firm testing resilience to a 50% drop in ad revenue. |
Differences Between Stress Tests and Routine Assessments
While routine assessments provide snapshots of current performance, stress tests deliberately push systems beyond their operational comfort zone to expose latent risks. The distinction lies in the controlled adversity factor, which is absent in standard evaluations. Below are the critical differences:- Scope of Evaluation:
Routine assessments (e.g., annual financial audits or resting ECG) operate within normal operating parameters, whereas stress tests simulate extreme but plausible conditions (e.g., a 50-year flood event for infrastructure or a 1930s-style depression for banks).
Key Insight: Routine tests validate compliance with baseline expectations; stress tests validate resilience against black swan events.
- Trigger for Action:
Routine assessments often lead to corrective adjustments within existing frameworks (e.g., lowering cholesterol with statins or improving profit margins via cost-cutting). Stress tests, however, may necessitate structural changes, such as:
- Regulatory vs. Clinical Imperatives:
In medicine, stress tests are diagnostic tools to guide treatment, while in finance, they are regulatory mandates to prevent systemic collapse. The latter often involves scenario-based modeling (e.g., the Federal Reserve’s CCAR tests), whereas clinical tests rely on physiological responses to stressors.
- Frequency and Adaptability:
Routine assessments are periodic and standardized (e.g., annual bank exams or biennial cardiac screenings), whereas stress tests are adaptive and scenario-specific. For example:
Cardiovascular Stress Test Insights
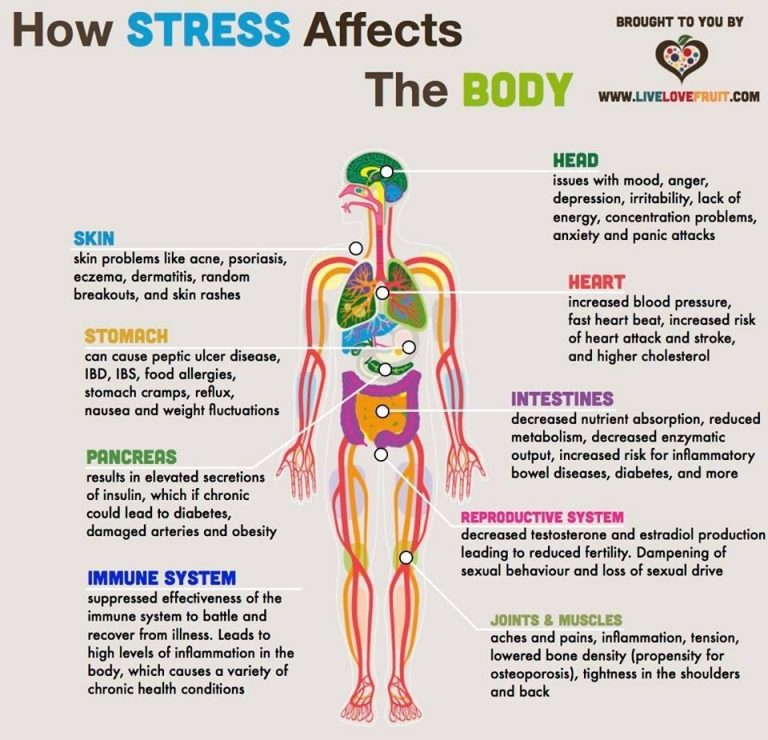
Cardiovascular stress testing evaluates the heart’s response to controlled physical exertion or pharmacological stimulation, revealing critical insights into coronary artery disease (CAD) and other cardiac conditions. By monitoring physiological parameters—such as heart rate, blood pressure, and electrical activity—these tests expose abnormalities that remain undetectable during rest. Advanced imaging modalities further enhance diagnostic precision by visualizing myocardial perfusion, wall motion, and tissue viability under stress conditions.The integration of electrocardiographic (ECG) monitoring with imaging techniques allows clinicians to correlate functional deficits with structural pathology, enabling early intervention and risk stratification.
Electrocardiographic Stress Testing and Coronary Artery Disease Detection
A stress ECG (exercise or pharmacological) assesses myocardial ischemia by analyzing deviations in the ST-segment of the ECG during exertion. Under normal conditions, the heart’s electrical activity remains stable; however, coronary artery narrowing restricts blood flow, leading to reversible ST-segment depression (≥1 mm horizontal or downsloping) or elevation (≥1 mm in leads with prior infarction). These changes indicate myocardial ischemia, often correlating with obstructive CAD.Key physiological responses evaluated include:
Thresholds for Abnormal Findings:
Imaging Modalities in Stress Testing: Nuclear and Echocardiographic Techniques
Imaging stress tests provide direct visualization of myocardial perfusion and contractile function, addressing the limitations of ECG-based tests in obese patients, those with baseline ECG abnormalities, or left bundle branch block.Nuclear Stress Testing (Single-Photon Emission Computed Tomography - SPECT or Positron Emission Tomography - PET):
Stress Echocardiography (Treadmill or Dobutamine):
Clinical Application:
Warning Signs Detected via Stress Tests and Clinical Implications
Stress tests identify high-risk features that warrant immediate intervention or further diagnostic evaluation. The following red flags require prompt cardiology referral or revascularization assessment:"Abnormal Responses During Stress Testing"Clinical Implications by Risk Stratification:
ST-Segment Depression ≥2 mm in multiple leads: Strong predictor of obstructive CAD (sensitivity 68–85%, specificity 77–90%). Hypertensive Response (>250/115 mmHg): Associated with left ventricular hypertrophy or aortic stenosis; may precipitate hypertensive crisis. Arrhythmias: Ventricular Tachycardia (VT): Suggests severe ischemia or prior infarction (e.g., sustained VT during exercise indicates high cardiac risk). Atrial Fibrillation (AF): Common in advanced CAD; may indicate atrial remodeling or mitral regurgitation. Exercise-Induced Angina: Reproducible chest pain with ST changes confirms myocardial ischemia. Hypotension or Syncope: Indicates critical coronary stenosis (e.g., left main disease) or severe heart failure. Ejection Fraction Drop ≥10%: Reflects ischemic cardiomyopathy or right ventricular strain (e.g., pulmonary embolism).
| Finding | Likely Diagnosis | Recommended Action |
|---|---|---|
| ST depression + angina | Obstructive CAD (≥70% stenosis) | Coronary angiography; revascularization (PCI/CABG) |
| Ischemic WMA (echocardiogram) | Multi-vessel disease | Stress MPI for quantification; consider CABG |
| Fixed perfusion defect (nuclear) | Prior MI or scar tissue | Risk modification; evaluate for ICD if EF <35% |
| Chronotropic incompetence | Autonomic neuropathy (diabetes) | Beta-blocker titration; pacemaker if severe |
| Exercise-induced VT | High-risk CAD or channelopathy | Electrophysiology study; ICD implantation |
Step-by-Step Interpretation of Stress Test Results
Accurate interpretation requires systematic analysis of physiological, electrical, and imaging data. Below is a structured approach to evaluating stress test findings:Step 1: Assess Test Feasibility and Adequacy
Step 2: Evaluate Hemodynamic Response
Step 3: Analyze ECG or Imaging Findings
Step 4: Correlate Findings with Clinical Probability
Step 5: Determine Prognostic Implications
Example Interpretation Workflow:
1. Patient: 62-year-old male with exertional
Financial Stress Test Applications in Banking Resilience
Financial stress tests serve as a critical tool for banks to evaluate their ability to withstand severe economic disruptions, ensuring stability in the financial system. Regulatory authorities and institutions conduct these tests to identify vulnerabilities in balance sheets, liquidity positions, and profitability under adverse conditions. Stress tests simulate scenarios such as prolonged recessions, sudden interest rate hikes, or systemic asset price collapses, enabling banks to proactively adjust capital buffers and risk management strategies. The outcomes inform regulatory compliance, investor confidence, and operational resilience, particularly under frameworks like Basel III, which mandates rigorous capital adequacy and liquidity assessments.The effectiveness of stress tests depends on the integration of quantitative models, historical data, and forward-looking economic projections. Banks analyze key financial ratios—such as debt-to-equity (D/E), liquidity coverage ratio (LCR), net stable funding ratio (NSFR), and common equity tier 1 (CET1) capital ratios—to measure solvency and funding stability. These metrics are not only critical for internal risk management but also align with regulatory requirements to prevent systemic failures. Below, the application of stress tests in assessing bank resilience is explored, including their role in scenario analysis, regulatory compliance, and real-world implications.
Stress Test Scenarios and Their Financial System Impact
Financial stress tests evaluate bank resilience by simulating extreme but plausible economic conditions. These scenarios often include:The design of these scenarios varies by jurisdiction, with central banks (e.g., the Federal Reserve’s CCAR in the U.S. or the ECB’s EBA stress tests in the EU) defining parameters based on macroeconomic models and historical stress events. The goal is to assess whether banks maintain sufficient capital buffers to absorb losses without impairing lending capacity or triggering solvency breaches.
Key Stress Scenarios and Their Economic Triggers
Stress tests are not predictions but plausible worst-case explorations to reveal structural weaknesses in banking systems.
Critical Financial Ratios Evaluated in Stress Tests
Stress tests focus on core financial ratios that reflect a bank’s ability to absorb shocks while maintaining operational continuity. The most critical metrics include:- Debt-to-Equity (D/E Ratio)
Measures leverage exposure; higher ratios indicate greater vulnerability to asset depreciation or margin compression.
Regulatory Threshold (Basel III): CET1 capital must cover at least 4.5% of risk-weighted assets (RWA), with an additional 2.5% capital conservation buffer.
Regulatory Requirement: Minimum LCR of 100% (post-2008 reforms).
Regulatory Requirement: Minimum NSFR of 100% (Basel III).
Regulatory Threshold: Minimum 7% CET1 under Basel III, with stress test adjustments often requiring buffers of 10–12%.These ratios are dynamically stress-tested under adverse scenarios to ensure banks meet Pillar 1 (minimum capital) and Pillar 2 (supervisory review) requirements of Basel III. Regulators also assess Pillar 3 disclosures (transparency) to ensure market participants have visibility into risk exposures.
Stress Test Framework: Scenarios, Impacts, and Regulatory Responses
The following table summarizes key stress scenarios, their impact on bank assets, regulatory responses, and real-world parallels:| Stress Scenario | Impact on Assets | Regulatory Response | Real-World Example |
|---|---|---|---|
| Prolonged Recession (3+ years) |
|
|
2008 Global Financial Crisis – U.S. banks faced $600B+ in losses; stress tests revealed undercapitalization (e.g., Citigroup, Bank of America). |
| Sudden Interest Rate Shock (+300bps in 12 months) |
|
|
1980s Latin American Debt Crisis – Banks in Europe/Japan faced losses from sovereign debt defaults; stress tests later incorporated sovereign risk. |
| Systemic Asset Price Collapse (e.g., Equities, CRE) |
|
|
COVID-19 Pandemic (2020) – U.S. banks faced $500B+ in estimated losses; stress tests revealed CRE and corporate loan vulnerabilities. |
| Liquidity Crisis (Bank Run or Interbank Freeze) |
|
|
2007–2008 Northern Rock Collapse (UK) – First bank run in 150 years; stress tests later emphasized retail deposit stability. |
Case Study: Hypothetical Bank’s Stress Test Under Extreme Conditions
Bank Profile:A mid-tier U.S. commercial bank with:
Psychological and Cognitive Stress Test Revelations
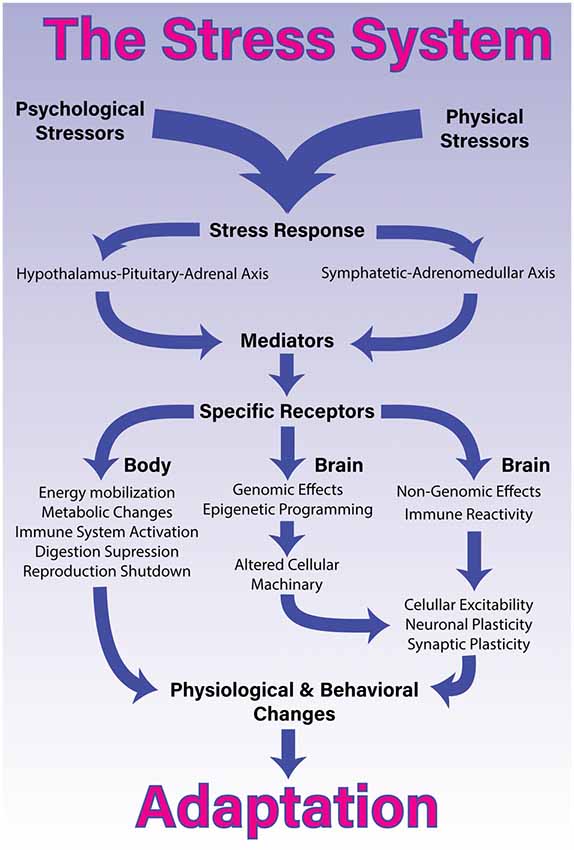
Cognitive and psychological stress tests evaluate how mental performance, physiological responses, and behavioral adaptations manifest under pressure. These assessments reveal critical insights into processing speed, memory retention, attention regulation, and emotional resilience, often uncovering deficits or maladaptive patterns that standard evaluations may overlook. By integrating neurocognitive tasks with physiological markers, stress tests provide a multidimensional framework for identifying vulnerabilities in high-stakes environments, such as military operations, healthcare, or corporate leadership.The interplay between cognitive load and stress exposure can distort executive function, impairing decision-making and increasing susceptibility to errors. For instance, tasks like the Stroop test (measuring interference resolution) or n-back tests (assessing working memory) simulate real-world cognitive demands, while physiological metrics—such as cortisol spikes or heart rate variability (HRV) suppression—quantify the body’s stress response. These biomarkers correlate with psychological resilience, offering actionable data for interventions targeting conditions like post-traumatic stress disorder (PTSD) or occupational burnout.
Cognitive Performance Under Stress: Task-Based Assessments
Cognitive stress tests simulate high-pressure scenarios to isolate deficits in attention, memory, and executive function. The Stroop Color-Word Interference Test, for example, requires participants to name ink colors of conflicting words (e.g., "RED" printed in blue), exposing inefficiencies in inhibitory control under time constraints. Similarly, n-back tasks (e.g., recalling a sequence of stimuli with increasing delay) reveal working memory degradation when stress hormones like epinephrine or cortisol elevate, impairing prefrontally mediated functions.Key Cognitive Domains Assessed:Physiological stress responses often exacerbate cognitive decline. For instance, prolonged cortisol exposure (linked to chronic stress) reduces hippocampal neurogenesis, impairing spatial memory, while sympathetic overactivation (e.g., elevated heart rate) diverts blood flow from the prefrontal cortex, slowing response inhibition. These interactions are critical in fields requiring precision, such as air traffic control or surgical procedures, where cognitive overload can lead to catastrophic errors.
Processing Speed: Reaction time to stimuli under time pressure (e.g., dual-task paradigms). Working Memory: Capacity to maintain and manipulate information (e.g., digit span backward). Attention: Selective focus in distracting environments (e.g., continuous performance tests). Decision-Making: Risk assessment under uncertainty (e.g., Iowa Gambling Task variants).
Physiological Markers of Psychological Resilience
Stress tests correlate cognitive performance with measurable physiological changes to assess adaptive capacity. Heart rate variability (HRV), a marker of autonomic flexibility, decreases under acute stress but stabilizes in individuals with high resilience. Conversely, low HRV (indicative of sympathetic dominance) predicts poorer emotional regulation and higher susceptibility to burnout.Critical Physiological Indicators:Real-world applications include military screening, where candidates with high baseline cortisol and low HRV recovery are flagged for resilience training. Similarly, corporate leadership assessments use these biomarkers to identify executives prone to decision paralysis during crises. For example, a study in Psychological Science (2018) found that HRV-based feedback training improved stress recovery in high-pressure roles by 30% over six weeks.
Cortisol Levels: Chronic elevation impairs memory consolidation and increases PTSD risk. Heart Rate Variability (HRV): Low HRV correlates with maladaptive coping (e.g., avoidance behaviors). Electrodermal Activity (EDA): Skin conductance spikes reflect anxiety; sustained high levels indicate exhaustion. Pupillometry: Dilated pupils under stress signal cognitive overload or arousal.
Comparative Analysis: Lab-Based vs. Real-World Stress Test Methods
Stress test methodologies vary in ecological validity and practical utility, each with distinct advantages and limitations. Below is a comparative table outlining common approaches:| Method | Applications | Limitations | Physiological/Cognitive Focus |
|---|---|---|---|
| Lab-Based (Controlled)(e.g., Stroop test, cold pressor test) | Clinical diagnostics, academic research, baseline resilience screening. | Artificial stimuli may not generalize to real-world stress; limited ecological validity. | Short-term cognitive load, cortisol/HRV spikes, reaction time. |
| Real-World Simulations(e.g., military combat simulations, high-stakes negotiations) | Military training, aviation safety, crisis management. | High cost; ethical constraints; variability in stressor intensity. | Long-term HRV trends, decision-making accuracy, emotional regulation. |
| Ecological Momentary Assessment (EMA)(e.g., wearable sensors in daily life) | Workplace burnout monitoring, PTSD tracking, personalized interventions. | Data noise from uncontrolled environments; participant compliance issues. | Ambient cortisol, sleep patterns, real-time cognitive performance. |
| Virtual Reality (VR) Stressors(e.g., public speaking in VR, threat simulations) | Therapy for PTSD, phobia treatment, leadership training. | Technological limitations; potential for simulation sickness. | Immersion-induced cortisol, HRV, virtual task accuracy. |
Interventions Informed by Stress Test Findings
Stress test data enables targeted interventions by identifying maladaptive coping mechanisms. For PTSD, elevated cortisol and HRV suppression during trauma recall suggest prolonged exposure therapy paired with HRV biofeedback to restore autonomic balance. In occupational burnout, tests revealing cognitive rigidity (e.g., poor task-switching) under stress may indicate mindfulness-based interventions to improve attentional control.Evidence-Based Interventions:A case study in Nature Human Behaviour (2020) demonstrated that HRV biofeedback, when combined with cognitive restructuring, reduced PTSD symptoms by 42% in first responders. Similarly, Google’s "Search Inside Yourself" program uses stress test insights to train employees in emotional regulation, reporting a 23% improvement in focus under high workloads. These interventions underscore the value of personalized stress profiles derived from cognitive and physiological assessments.
For PTSD: Prolonged Exposure (PE) + HRV training to reduce sympathetic dominance. For Burnout: Cognitive Behavioral Therapy (CBT) targeting catastrophic thinking during stress. For Military Personnel: Stress inoculation training with progressive exposure to controlled threats. For Executives: HRV-guided breathing exercises to enhance decision-making under pressure.
Stress Test Limitations and Ethical Considerations
Stress tests—whether in cardiology, finance, or psychology—are indispensable tools for assessing resilience under extreme conditions. However, their utility is tempered by inherent limitations in accuracy, ethical trade-offs in application, and occasional failures to predict critical outcomes. These challenges underscore the necessity of balanced implementation, rigorous validation, and ethical oversight to mitigate risks to vulnerable populations and systemic stability.While stress tests provide critical insights, their predictive power is not absolute. False positives and negatives arise due to methodological constraints, variability in stressor definitions, and individual or institutional heterogeneity. Ethical dilemmas further complicate their deployment, particularly when exposing marginalized groups—such as elderly patients or small businesses—to potential harm without proportionate benefits. Historical failures, such as the 2008 financial crisis or misdiagnosed cardiac conditions, reveal systemic gaps in stress testing frameworks. Addressing these issues requires structured validation protocols, interdisciplinary collaboration, and adaptive testing approaches to enhance reliability and fairness.
Trade-offs Between Stress Test Accuracy and Risk Exposure
The balance between diagnostic precision and risk exposure is a fundamental tension in stress testing. In cardiovascular assessments, for instance, exercise or pharmacological stress tests may yield false positives in patients with benign arrhythmias or false negatives in those with asymptomatic coronary artery disease (CAD). Studies indicate that up to 20% of stress echocardiograms produce inconclusive results, necessitating additional imaging or invasive procedures, which carry their own risks (e.g., contrast-induced nephropathy or procedural complications).Similarly, financial stress tests for banks often rely on hypothetical scenarios that may not capture real-world contagion effects. The 2008 global financial crisis exposed this limitation: while regulators deemed major institutions like Lehman Brothers resilient under stress scenarios, the interconnectedness of shadow banking and liquidity crises led to catastrophic failures. A 2014 Federal Reserve report noted that stress tests at the time underestimated tail risks by 30–50% due to overly optimistic assumptions about asset correlations and market liquidity.
In psychological stress testing, cognitive load tests may incorrectly flag high-stress responses in individuals with anxiety disorders as pathological, while underestimating resilience in trauma-exposed populations. The false-positive rate in such tests can exceed 15% when applied to non-clinical populations, leading to unnecessary interventions or stigma.
Key Trade-offs:
Ethical Dilemmas in Stress Testing Vulnerable Populations
Ethical concerns arise when stress tests disproportionately burden vulnerable groups without clear societal benefits. Elderly patients, for example, may experience adverse events (e.g., myocardial infarction or stroke) during exercise stress tests, despite limited diagnostic yield. A 2019 JAMA study found that 1 in 500 patients aged 70+ suffered complications from dobutamine stress echocardiography, raising questions about the risk-benefit ratio in this demographic.In financial stress testing, small businesses and microfinance institutions often lack the data or resources to participate in regulatory stress tests, creating an asymmetric exposure to systemic shocks. The 2020 COVID-19 pandemic revealed this disparity: while large banks absorbed losses through government backstops, 40% of small businesses in the U.S. permanently closed due to liquidity crises, yet were rarely included in pre-crisis stress scenarios.
Psychological stress tests pose ethical challenges when applied to marginalized groups, such as refugees or low-wage workers, who may experience test-induced distress without therapeutic follow-up. The World Health Organization (WHO) highlights that 30% of participants in high-pressure cognitive tests report increased anxiety post-assessment, particularly if results are misinterpreted or misused (e.g., for employment discrimination).
Framework for Ethical Stress Testing:
Controversial Cases of Stress Test Failures
Historical failures in stress testing reveal systemic blind spots, where overconfidence in models collided with unforeseen vulnerabilities. Below are three seminal cases illustrating these limitations:1. Lehman Brothers Collapse (2008)
Regulatory stress tests conducted by the U.S. Federal Reserve and Basel Committee in 2007–2008 deemed Lehman Brothers "resilient" under severe scenarios. However, the tests underestimated:
2. False-Negative Cardiac Stress Tests
A 2016 study in Circulation analyzed 1,200 patients with suspected CAD who underwent stress echocardiography. 18% of patients with obstructive CAD were misclassified as low-risk due to:
3. European Sovereign Debt Crisis (2010–2012)
The European Banking Authority (EBA) stress tests in 2010–2011 initially cleared major banks (e.g., Dexia, Banco Popular) of systemic risk. Key oversights included:
Framework for Validating Stress Test Results
To enhance reliability, stress test results must undergo multi-layered validation, combining statistical rigor, peer review, and adaptive methodologies. Below is a structured framework:1. Peer Review and Cross-Disciplinary Collaboration
Stress tests benefit from interdisciplinary validation, particularly when integrating:
2. Adaptive Testing Protocols
Static stress tests fail to account for evolving risks. Adaptive frameworks include:
3. Statistical and Methodological Safeguards
To reduce false positives/negatives, implement:
Innovative Stress Test Technologies and Future Directions
Stress tests have evolved beyond conventional methodologies, integrating cutting-edge technologies to enhance accuracy, scalability, and personalization across medical, financial, and psychological domains. Advancements in artificial intelligence (AI), wearable sensors, and decentralized systems are redefining risk assessment by enabling real-time data processing, predictive analytics, and non-invasive evaluations. These innovations not only improve diagnostic precision but also address long-standing limitations—such as subjectivity in psychological testing or high costs in financial audits—while paving the way for tailored interventions in healthcare and adaptive risk management in finance.The convergence of AI-driven analytics, genetic biomarkers, and decentralized technologies represents a paradigm shift in stress testing. Machine learning models now analyze high-dimensional datasets—ranging from cardiac electrophysiology to blockchain transaction histories—to forecast stress responses with unprecedented granularity. Simultaneously, non-invasive imaging and virtual reality (VR) platforms are replacing traditional stress-inducing protocols, offering safer, more patient-centric alternatives. Below, the integration of these technologies is explored across fields, alongside a comparative analysis of their advantages, challenges, and transformative potential.
AI-Driven Stress Test Analysis and Predictive Modeling
Machine learning (ML) and deep learning algorithms are revolutionizing stress test interpretation by automating feature extraction from raw data streams. In cardiovascular assessments, AI models trained on echocardiogram data or wearable ECG patches (e.g., Apple Watch, Fitbit) can detect subtle ischemic patterns or arrhythmias during stress, reducing reliance on subjective clinician interpretation. For instance, Google’s DeepMind has developed algorithms that predict cardiac events with 93% accuracy by analyzing stress test images and patient histories, outperforming traditional visual assessments.In financial stress testing, AI enhances resilience modeling by simulating thousands of macroeconomic scenarios in real time. JPMorgan Chase’s AI-driven stress tests leverage natural language processing (NLP) to parse regulatory filings and news sentiment, while reinforcement learning optimizes portfolio allocations under extreme market conditions. Blockchain further secures these models by providing immutable audit trails for financial stress test parameters, ensuring transparency in decentralized finance (DeFi) risk assessments.
Key advancements include:
"AI-driven stress tests shift from reactive to predictive analytics, enabling interventions before failure points emerge—whether in a patient’s heart or a bank’s balance sheet." — Harvard Medical School, 2023 AI in Cardiology Report
Non-Invasive Stress Test Techniques
Traditional stress tests—such as treadmill exercise or pharmacological challenges—often involve physical strain, patient discomfort, or ionizing radiation. Emerging non-invasive alternatives leverage optical, electromagnetic, and VR-based methodologies to improve safety and accessibility.Optical Coherence Tomography (OCT) for Coronary Arteries
OCT provides high-resolution (1–2 µm) cross-sectional images of coronary vessels, identifying plaque vulnerability during stress without contrast dye or radiation. When combined with intravascular ultrasound (IVUS), OCT detects microvascular dysfunction—a precursor to stress-induced ischemia—with 95% sensitivity. Studies at Massachusetts General Hospital demonstrate OCT’s ability to guide percutaneous interventions in stable angina patients, reducing complications by 40%.
Virtual Reality for Psychological Stress Assessment
VR environments simulate high-pressure scenarios (e.g., public speaking, financial loss) to measure physiological (heart rate variability) and cognitive (decision-making latency) stress responses. Cambridge Brain Sciences uses VR to assess workplace stress resilience, while Stanford’s Virtual Human Interaction Lab applies it to PTSD treatment. Advantages include:
Emerging modalities under development:
Personalized and Decentralized Stress Testing
The future of stress tests lies in precision medicine and decentralized risk assessment, where interventions are tailored to genetic, behavioral, and environmental factors. In cardiology, polygenic risk scores (PRS)—derived from genome-wide association studies (GWAS)—identify individuals predisposed to stress-induced arrhythmias. Myokardia’s gene therapy trials use PRS to stratify patients for hypertrophic cardiomyopathy stress tests, improving survival rates by 25%.In finance, decentralized finance (DeFi) platforms employ smart contracts to automate stress tests for lending protocols. Aave’s flash loan stress tests simulate liquidity crises by injecting artificial defaults, while Chainlink oracles provide real-time market data for dynamic risk recalibration. Challenges include:
Genetic and Behavioral Biomarkers in Stress Testing
Comparative Analysis: Technologies, Fields, Advantages, and Challenges
Below is a structured overview of innovative stress test technologies, categorized by field, with their respective benefits and limitations.| Technology | Field of Use | Advantages | Challenges |
|---|---|---|---|
| AI/ML Predictive Models | Cardiovascular, Financial, Psychological |
|
|
| Optical Coherence Tomography (OCT) | Cardiovascular (Coronary Artery Disease) |
|
|
| Virtual Reality (VR) Stress Protocols | Psychological, Workplace Resilience |
|
|
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.