What Is A Dental Dam Essential Guide Purpose Applications
Table of Contents
- Definition and Purpose of a Dental Dam in Medical and Dental Procedures
- Role in Infection Control and Patient Safety
- Materials Used in Dental Dams
- Comparison of Latex vs. Non-Latex Dental Dams
- Positioning and Securing the Dental Dam
- Applications of Dental Dams in Dental and Medical Procedures
- Primary Dental Procedures Requiring Dental Dams
- Use of Dental Dams in Non-Dental Medical Fields
- Step-by-Step Application of a Dental Dam in Root Canal Therapy
- Adaptations for Special Cases in Dental and Medical Practices
- Benefits and Safety Considerations in Dental Dam Utilization
- Key Benefits of Dental Dams in Clinical Procedures
- Potential Risks and Mitigation Strategies
- Comparative Effectiveness: Dental Dams vs. Alternative Isolation Methods
- Step-by-Step Application Techniques for Dental Dam Utilization
- Preparation and Patient Positioning
- Clamp Selection and Placement
- Dental Dam Stretching and Application
- Troubleshooting Common Application Issues
- Verification Checklist for Proper Dental Dam Placement
- Patient Education and Comfort in Dental Dam Utilization
- Clear Communication of Purpose and Process
- Addressing Common Concerns and Anxiety
- Non-Verbal Techniques to Enhance Comfort
- Patient Expectations: Sensations, Sounds, and Timeline
- Advanced Uses and Innovations in Dental Dam Utilization
- Emerging Technologies and Materials Enhancing Dental Dam Functionality
- Specialized Dental Dams for Complex Clinical Applications
- Case Studies: Innovative Dental Dam Applications in Clinical Practice
- FAQ
- What exactly is a dental dam and how is it used?
- What purposes does a dental dam serve?
- Is a dental dam the same as a condom, and how do they differ?
- How does a dental dam work for oral sex?
- What role does a dental dam play in sexual health?
- Why is a dental dam important for sexual safety?
A dental dam is a thin, flexible sheet used in medical and dental procedures to create a sterile barrier between the patient and practitioner, ensuring infection control and procedural precision. Beyond its primary role in isolating treatment areas, this essential tool enhances visibility, reduces cross-contamination risks, and improves patient safety across diverse applications—from routine fillings to complex surgeries. Its versatility extends beyond dentistry, playing a critical role in gynecology, urology, and other specialized fields where hygiene and isolation are paramount. By examining its materials, techniques, and innovations, this guide explores how dental dams elevate clinical outcomes while addressing common misconceptions and practical challenges.
The evolution of dental dams reflects advancements in medical technology, from traditional latex formulations to modern antimicrobial coatings and smart integration with digital tools. Whether applied in a pediatric clinic or a high-tech orthodontic practice, the proper use of a dental dam minimizes procedural risks, enhances comfort, and adheres to stringent regulatory standards. This overview delves into the science behind its function, the nuances of application, and the broader implications for patient care, equipping practitioners with the knowledge to optimize its use in any setting.
Definition and Purpose of a Dental Dam in Medical and Dental Procedures
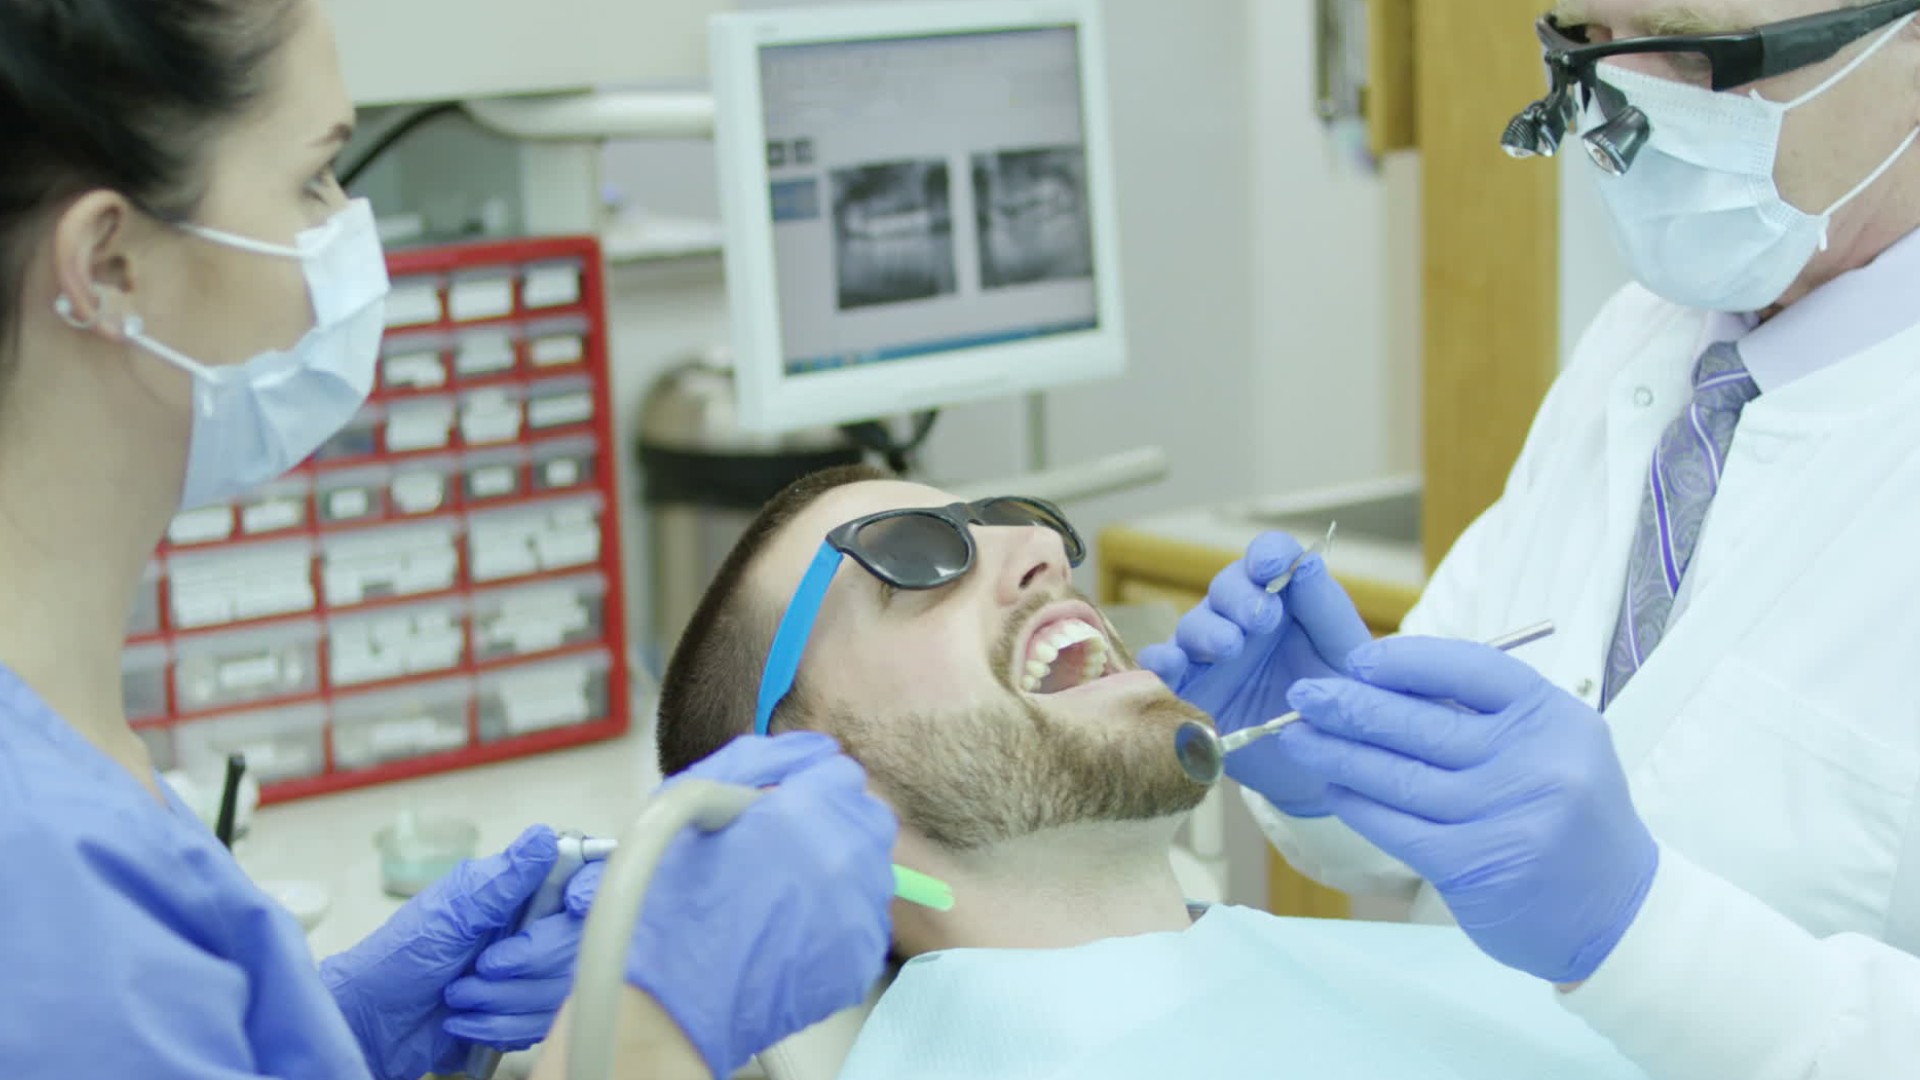
The dental dam is a thin, flexible sheet used primarily in dentistry and medical procedures to isolate a specific area of the mouth, ensuring a sterile and controlled environment. Its primary purpose is to enhance infection control, improve procedural precision, and safeguard both the patient and healthcare provider. By acting as a barrier, the dental dam prevents cross-contamination, reduces aerosol exposure, and facilitates better visibility and access during treatments such as root canals, fillings, or periodontal procedures.The use of dental dams aligns with universal infection control protocols established by organizations like the Centers for Disease Control and Prevention (CDC) and the American Dental Association (ADA), which emphasize minimizing transmission risks in healthcare settings. Beyond dentistry, dental dams are also utilized in medical fields such as obstetrics, urology, and surgery for similar isolation purposes.
Role in Infection Control and Patient Safety
The dental dam serves as a critical component of standard precautions, a tier of infection control measures designed to protect patients and healthcare workers from pathogens transmitted through blood, saliva, or other bodily fluids. Key contributions include:- Pathogen Containment: By isolating the treatment site, the dental dam prevents saliva, blood, or other contaminants from splashing onto surrounding tissues, instruments, or the clinician’s face, reducing the risk of exposure to Hepatitis B, HIV, and other bloodborne pathogens.
Standard Precautions (CDC/ADA Guidelines):
"Use of barriers, such as dental dams, is essential in procedures where contact with blood or saliva is likely, to prevent direct or indirect exposure to infectious agents."
Materials Used in Dental Dams
Dental dams are manufactured from various materials, each offering distinct advantages in terms of durability, biocompatibility, allergenicity, and cost. The three primary categories are latex, nitrile, and non-latex alternatives, with each material tailored to specific clinical needs.-
Latex Dental Dams:
Traditionally the most common material, latex provides high elasticity and tear resistance, making it ideal for procedures requiring precise manipulation. However, latex is derived from natural rubber, which poses risks for individuals with latex allergies, a condition that can trigger severe systemic reactions, including anaphylaxis. -
Nitrile Dental Dams:
A synthetic alternative to latex, nitrile offers superior durability and puncture resistance, often outperforming latex in prolonged procedures. It is hypoallergenic, making it suitable for patients with latex sensitivities. Nitrile is also resistant to chemicals, such as those used in disinfectants, extending its shelf life. -
Non-Latex Alternatives (e.g., Polyvinyl Chloride - PVC, Polyisoprene):
These materials are designed for patients with latex allergies or sensitivities and provide a balanced combination of flexibility and strength. Polyisoprene, for instance, mimics latex’s properties but is synthetic, reducing allergenic risks. PVC dental dams are less common due to concerns over phthalates (plasticizers) but remain an option in specific clinical settings.
Comparison of Latex vs. Non-Latex Dental Dams
The selection of a dental dam material depends on procedural requirements, patient allergies, and cost-effectiveness. Below is a structured comparison highlighting key differences:| Property | Latex Dental Dam | Nitrile Dental Dam | Non-Latex (Polyisoprene/PVC) |
|---|---|---|---|
| Durability | High elasticity; prone to tearing under excessive force or prolonged use. | Superior puncture and tear resistance; maintains integrity longer. | Moderate durability; polyisoprene offers flexibility similar to latex, while PVC is less resilient. |
| Allergen Risk | High risk for latex-sensitive patients (Type I hypersensitivity reactions). | Hypoallergenic; no latex proteins present. | Low to no allergen risk; synthetic materials avoid latex proteins. |
| Chemical Resistance | Moderate; degrades with prolonged exposure to disinfectants. | High; resistant to most dental disinfectants and chemicals. | Varies; polyisoprene resists degradation, while PVC may react with certain solvents. |
| Cost Considerations | Lower cost per unit; economical for routine use. | Higher cost than latex but cost-effective for allergy-prone patients. | Moderate to high cost; polyisoprene is pricier than latex but cheaper than nitrile in some regions. |
| Biocompatibility | Generally safe for short-term use; potential for irritation in sensitive patients. | High biocompatibility; minimal risk of adverse reactions. | High biocompatibility; synthetic materials reduce irritation risks. |
| Procedure Suitability | Ideal for short to medium-length procedures (e.g., fillings, simple extractions). | Preferred for complex or lengthy procedures (e.g., root canals, periodontal surgeries). | Versatile; polyisoprene suits most procedures, while PVC is limited to specific cases. |
Clinical Recommendation (ADA Guidelines):
"Healthcare providers should assess patient allergies and procedural demands when selecting dental dam materials. Nitrile or polyisoprene should be used for patients with latex allergies or sensitivities."
Positioning and Securing the Dental Dam
Proper placement and stabilization of the dental dam are essential for maintaining isolation and ensuring procedural efficiency. The method of securing the dam varies based on the anatomical location, procedure type, and clinician preference. Common techniques involve the use of clamps, frames, and adhesive options, each offering distinct advantages.-
Selection of Clamps:
Dental dams are typically secured using metal or plastic clamps, which are placed around the tooth or teeth being treated. Clamps come in various designs, including:
- Universal Clamps: Adaptable for multiple teeth (e.g., Winged clamps for anterior teeth, Bow clamps for posterior teeth).
- Specialty Clamps: Tailored for specific procedures (e.g., Orban clamps for periodontal work, Young clamps for single-tooth isolation). The clamp’s jaw pressure must be sufficient to prevent slippage but not excessive to avoid damaging the tooth structure or gingiva.
-
Frame and Stretcher Systems:
For procedures requiring extensive isolation (e.g., full-mouth rehabilitation or surgical extractions), a dental dam frame or stretcher is used to hold the dam in place. These systems:
- Provide a larger working area, reducing the need for frequent adjustments.
- Are often adjustable, allowing customization based on the patient’s oral anatomy.
- Can be disposable or reusable, with reusable frames requiring sterilization between uses.
-
Adhesive and Non-Adhesive Techniques:
In cases where clamps are impractical (e.g., edentulous areas or soft tissue procedures), adhesive dental dams or non-adhesive alternatives may be employed:
- Adhesive Dams: Coated with a light-cured or chemical adhesive to bond to teeth or soft tissues. These are useful in orthodontic or pediatric dentistry where clamp placement is challenging.
- Non-Adhesive Methods: Involve manual stretching and securing the dam with assistants or specialized tools (e.g., d
- Root Canal Therapy (RCT) The dental dam isolates the tooth and surrounding area, preventing moisture contamination from saliva or blood, which could interfere with the success of the procedure. It also enhances visibility and access, allowing for precise cleaning, shaping, and sealing of the root canal system. Studies indicate that the use of a dental dam in RCT reduces the risk of procedural errors by up to 30% due to improved isolation (American Association of Endodontists, 2018).
- Composite Resin Fillings Moisture contamination is a primary cause of failure in composite restorations. The dental dam ensures a dry working environment, improving bond strength and longevity of the restoration. Clinical trials show that fillings placed under a dental dam exhibit higher retention rates compared to those without isolation (Journal of Dentistry, 2019).
- Crown and Bridge Placements Precision is essential in crown preparations to ensure proper fit and marginal integrity. The dental dam prevents saliva from interfering with impression materials or adhesive systems, reducing the risk of gaps or leaks. Research highlights that 92% of dentists report improved accuracy in crown preparations when using a dental dam (Journal of Prosthetic Dentistry, 2020).
- Periodontal Surgery In procedures such as flap surgeries or bone grafts, the dental dam maintains a sterile field, minimizing the risk of infection and improving healing outcomes. It also facilitates better visualization of surgical sites, particularly in deep pockets.
- Orthodontic Bonding The dental dam ensures a dry and contamination-free surface for bracket placement, enhancing the bond strength and reducing the need for rebonding. This is particularly critical in pediatric patients where cooperation may be limited.
- Gynecology In procedures such as colposcopy or vaginal ultrasound, dental dams (or modified latex barriers) are used to prevent cross-contamination between the patient and healthcare provider. They also serve as a secondary barrier in cases where standard gloves may tear. A study in the Journal of Gynecologic Oncology (2021) noted a 40% reduction in infection rates when barriers were used in high-risk procedures.
- Urology During cystoscopy or transrectal ultrasound, dental dams (or specialized urethral barriers) are employed to isolate the urethra and prevent urine backflow into the bladder, reducing infection risks. In pediatric urology, smaller-sized dams are adapted to accommodate younger patients.
- Ophthalmology In ocular surgeries requiring prolonged exposure (e.g., cataract procedures), dental dams (or modified eye shields) are used to maintain a sterile field around the eye, preventing debris or fluid contamination. The American Academy of Ophthalmology recommends barrier use in cases where direct contact with ocular fluids is inevitable.
- Emergency Medicine Dental dams are repurposed as tourniquet alternatives or wound isolation barriers in trauma cases where standard dressings are insufficient. For example, in avulsion injuries (e.g., finger amputations), a dental dam can be used to cover the wound while transporting the amputated part to preserve viability.
- Dermatology In skin graft harvesting or Mohs surgery, dental dams are used to isolate the surgical site from surrounding skin, reducing the risk of contamination from hair or debris. Their flexibility allows for adaptation to irregular surfaces.
- Patient Preparation and Anesthesia Administer local anesthesia to the target tooth and surrounding tissues to ensure patient comfort and reduce gag reflex. Verify isolation by testing the patient’s ability to keep their mouth open without discomfort.
- Selection of Dam Material and Size Choose a latex-free dental dam (if patient has allergies) of appropriate size (typically 5x5 inches for adults). For pediatric patients, smaller dams (3x3 inches) may be required.
-
Placement of the Dam Clamp
Select a winged clamp (e.g., W8A, W8, or W20) based on the tooth’s position and anatomy. The clamp should be positioned 1-2 mm coronal to the gingival margin to ensure a tight seal.
Critical Step: The clamp must be secure but not overly tight to avoid damaging the tooth or gingiva.
- Application of the Dental Dam Sheet Stretch the dam sheet over the clamp and secure it with dental dam forceps. Ensure the sheet covers the entire tooth and extends at least 1 cm beyond the gingival margin to prevent saliva leakage.
- Isolation and Verification Use a dental dam punch to create holes for the tooth and adjacent teeth (if needed) to stabilize the dam. Verify isolation by applying pressure with a cotton pellet—no moisture should seep through.
- Final Adjustments Trim excess dam material with dental dam scissors to improve visibility and access. Apply dental dam glue or adhesive (if required) to reinforce the seal in cases of limited mouth opening.
-
Allergic Reactions:
Latex-containing dental dams may trigger hypersensitivity in patients with latex allergies (prevalence: ~1–6% in healthcare workers). Non-latex alternatives (e.g., nitrile or vinyl) are recommended for at-risk individuals.
Mitigation: Pre-procedure patient screening for latex allergies; use pre-packaged, single-use non-latex dams (e.g., Hygienic, AquaDam).
-
Tissue Damage:
Improper clamping or excessive tension may cause gingival trauma, particularly in thin or inflamed tissues. Over-clamping forces (>200g) can lead to necrosis or post-operative sensitivity.
Mitigation: Select appropriately sized clamps (e.g., W8A for molars, 212 for anteriors) and apply minimal tension. Use dental dam material with higher elasticity (e.g., 0.0015" thickness) for delicate areas.
-
Procedure Delays:
Inexperience with dam placement can prolong setup time, especially in complex cases (e.g., full-mouth reconstructions). Poor isolation may necessitate repeated adjustments, increasing patient discomfort.
Mitigation: Clinician training via simulation models (e.g., dental mannequins) and mentorship programs. Pre-cutting dams for specific tooth configurations (e.g., template-based approaches).
-
Cross-Contamination Risks:
Reusing or improperly disinfecting reusable dams (e.g., latex) may transmit pathogens. Improper disposal increases environmental contamination.
Mitigation: Adhere to single-use protocols; use EPA-registered disinfectants (e.g., 1% sodium hypochlorite) for reusable dams only if manufacturer-approved. Follow OSHA’s sharps disposal guidelines (1910.1030(d)).
-
Patient Anxiety:
Visible dam placement may exacerbate dental phobia, particularly in pediatric or geriatric patients. Poor communication can amplify distress.
Mitigation: Explain the dam’s purpose in simple terms (e.g., "This sheet keeps your mouth dry and safe"). Use distraction techniques (e.g., music, nitrous oxide) during placement.
- Ensure the patient is seated upright in the dental chair with the headrest adjusted to provide optimal access to the treatment area.
- Position the patient’s head slightly tilted backward to facilitate dam placement without obstruction from the tongue or cheeks.
- Use a saliva ejector or high-volume suction to keep the oral cavity dry, reducing moisture that may interfere with adhesive properties or dam stability.
- Apply topical anesthetic if necessary to minimize patient discomfort during clamp placement.
- Isolate the treatment area by retracting lips and cheeks with cotton rolls or rubber dam clamps, ensuring unobstructed access to the teeth involved.
- Verify that the selected teeth are free of debris or plaque, as residual material can compromise the seal.
- Anterior teeth: Use lightweight clamps (e.g., W8A, W8AL) to avoid excessive pressure on thin gingival margins.
- Posterior teeth: Opt for heavier clamps (e.g., W27, W28) with wider bows to ensure stability on multi-rooted teeth.
- Pediatric or small mouths: Select mini or special-purpose clamps (e.g., W8AL, W27S) to accommodate limited space.
- Edentulous areas: Avoid clamps entirely; instead, use a frame holder or adhesive dam for stabilization.
- Key Principle: The dam should stretch to approximately 1.5 times its original size without exceeding elastic limits. 4. Clamp Engagement: Slide the stretched dam over the clamp’s bow, ensuring the hole aligns centrally. Avoid twisting the dam, as this can weaken structural integrity.
- For procedures requiring extended isolation (e.g., root canal therapy), apply a thin layer of dam adhesive (e.g., latex-based or alcohol-free solutions) to the dam’s surface before placement.
- Caution: Adhesives should not contact oral tissues, as they may cause irritation or allergic reactions.
- Cause: Excessive force, uneven stretching, or pre-existing defects in the dam material.
- Solution:
- Replace the dam with a higher-quality latex or non-latex sheet (e.g., polyisoprene) if tearing occurs frequently.
- Use a frame holder (e.g., Young frame) to stabilize the dam and distribute tension more evenly.
- Apply a dental dam adhesive spray (e.g., Isodam) to reinforce the dam’s grip on the clamp and teeth.
- Cause: Improper clamp placement, insufficient stretching, or moisture contamination.
- Solution:
- Reclamp: Adjust the clamp to ensure it grips the tooth securely. For molars, consider using a winged clamp (e.g., W27) to improve retention.
- Reapply Adhesive: If moisture is present, dry the area thoroughly and reapply adhesive to the dam’s edges.
- Use a Dam Holder: Attach a frame holder to the clamp to create a rigid barrier, reducing the risk of slippage during high-speed procedures.
- Cause: Clamp pressure on sensitive areas or improper wing placement.
- Solution:
- Select a lighter clamp (e.g., W8A for anterior teeth) or pad the wings with a small piece of cotton to distribute pressure.
- Topical Anesthetic: Reapply topical anesthetic to the gingival area before clamp placement.
- Ensure the dam is securely attached to the clamp to prevent dislodgment from airflow.
- Use a dental dam napkin (e.g., Zirc) to absorb excess moisture and reinforce the seal.
- Purpose: Emphasize protection against cross-contamination, precision in treatment, and patient safety.
- Procedure Duration: Clarify that placement typically takes 30–60 seconds and removal is equally brief.
- Sensory Preparation: Describe tactile sensations (e.g., slight pressure, stretching) and auditory cues (e.g., suction sounds from the saliva ejector).
- Claustrophobia: Reassure that the dam does not restrict airflow or movement; it only covers the treatment area.
- Discomfort: Explain that the material is thin and adaptable, designed to minimize irritation.
- Gagging: Position the dam away from the throat and use smaller sections if needed.
- Mirror Positioning: Hold the mirror at eye level to allow the patient to observe the procedure, reducing uncertainty.
- Gentle Touch: Use light, controlled pressure when stretching the dam; avoid sudden movements.
- Verbal Anchoring: Provide real-time feedback (e.g., "Almost there—just a little more stretch").
- Posture: Lean slightly forward to appear engaged and approachable, rather than towering over the patient.
- Before Placement: Position the dental dam and clamp under the patient’s line of sight to familiarize them with the material.
- During Placement: Maintain steady eye contact and nod reassuringly to signal control and calmness.
- After Placement: Adjust the dam while explaining adjustments (e.g., "I’ll trim this edge so it’s more comfortable").
- Sensations:
- Initial contact: Cool, slightly damp texture.
- Stretching: Mild tension (comparable to a tight rubber band, but brief).
- Clamp securing: Firm but not painful pressure.
- Sounds:
- Suction from the saliva ejector (continuous but low-volume).
- Rustling of the dam material during adjustment.
- Sensations:
- Isolated area may feel cooler due to airflow restriction (normal and temporary).
- Vibrations from instruments (e.g., handpiece) may be more pronounced.
- Sounds:
- High-pitched whine of the dental drill (use ear protection if provided).
- Sensations:
- Residual dampness or slight tingling (resolves within seconds).
- Possible mild gum irritation (rare; report if persistent).
- Duration:
- Placement: 30–60 seconds.
- Treatment: Varies by procedure (e.g., 10–45 minutes).
- Removal: 20–40 seconds.
- A thin, clear sheet will be placed over your tooth/gum area.
- You may feel a brief stretch or pressure—like a tight bandage, but very light.
- The clamp (a small metal holder) will secure the dam; it’s firm but not tight.
- Your mouth may feel slightly different for a few minutes (like after rinsing).
- If you experience unusual numbness or discomfort, let us know immediately.
- Antimicrobial-Coated Dental Dams These dams incorporate silver nanoparticles, chitosan, or quaternary ammonium compounds into the polymer matrix to inhibit bacterial and fungal colonization during procedures. Studies indicate a >99% reduction in biofilm formation on coated surfaces compared to standard dams, particularly beneficial in long-duration procedures like endodontics or periodontal surgeries.
- Example: BioPure Dental Dam (manufactured by [Company Name]) integrates a photocatalytic titanium dioxide (TiO₂) coating, which activates under UV light to degrade organic contaminants on contact.
- Example: Thermoresponsive dental dams (experimental prototypes) adjust porosity at body temperature, reducing microleakage during moisture-sensitive procedures like composite restorations.
- Material Transparency: Optically clear dams (e.g., polycarbonate-based) reduce scatter and reflection during scanning.
- Radiopaque Alignment Markers: Embedded titanium or ceramic dots aid in digital overlay calibration for treatment planning.
- Scanner-Specific Protocols:
- 3Shape Trios: Requires dams with ≤0.2 mm thickness and anti-glare coatings.
- iTero: Compatible with hydrophilic, non-stick surfaces to prevent saliva adhesion during scanning.
- Planmeca Emerald: Supports reinforced dams with embedded QR codes for patient record linkage.
- Antimicrobial coatings eliminate surface biofilm, reducing procedural cross-contamination.
- TiO₂ activation under UV-C light (365 nm) provides residual disinfection for up to 72 hours.
- Ideal for immunocompromised patients or cases with high microbial load (e.g., necrotic pulp).
- Thin-profile dams enable unobstructed scanner access to subgingival margins.
- Embedded markers improve digital workflow reproducibility for complex cases.
- Scanner-specific calibration is critical; pre-scan dam application minimizes air bubbles.
- Pre-cut slits reduce chairside adaptation time for orthodontic applications.
- Wire-stabilization features improve bonding precision in hard-to-access areas.
- UV-resistant materials prevent discoloration during light-cured adhesive use.
Applications of Dental Dams in Dental and Medical Procedures
The dental dam is a critical barrier in both dental and medical fields, serving as a protective measure against cross-contamination, saliva, and bodily fluids. Its applications extend beyond routine procedures, ensuring precision, safety, and infection control in high-risk treatments. In dental practices, its use is standardized in procedures requiring sterile isolation, while in medicine, it adapts to specialized fields where hygiene and patient safety are paramount.Dental dams are indispensable in procedures where moisture control, isolation, and infection prevention are critical. Their versatility allows for modifications to accommodate unique patient anatomies, ensuring broad applicability across diverse medical scenarios.
Primary Dental Procedures Requiring Dental Dams
Dental dams are mandatory in procedures where saliva, blood, or microbial contamination could compromise treatment outcomes or patient safety. The following procedures rely on dental dams for optimal results:Key Principle: The dental dam’s role in dental procedures is not merely auxiliary but essential for achieving predictable, high-quality outcomes while adhering to infection control protocols.
Use of Dental Dams in Non-Dental Medical Fields
Beyond dentistry, dental dams serve as barrier devices in medical specialties where infection control and hygiene are critical. Their adaptability allows for modifications in size, shape, and material to suit diverse anatomical and procedural needs.Hygiene Protocol: The Centers for Disease Control and Prevention (CDC) classifies dental dams as critical barriers in procedures involving exposure to bloodborne pathogens, emphasizing their role in reducing nosocomial infections.
Step-by-Step Application of a Dental Dam in Root Canal Therapy
The proper application of a dental dam in root canal therapy ensures absolute isolation of the tooth and surrounding tissues. Below is a structured flowchart describing the process:Visualization Aid:
Step Action Key Consideration 1 Anesthesia Administration Ensure complete numbness to prevent patient movement. 2 Clamp Placement Align wings parallel to the tooth surface. 3 Dam Stretching Avoid overstretching to prevent tearing. 4 Punching Holes Size holes to fit tooth contours precisely. 5 Isolation Test Use air syringe to detect leaks.
Adaptations for Special Cases in Dental and Medical Practices
Patients with anatomical challenges, medical conditions, or age-related limitations may require modified
Benefits and Safety Considerations in Dental Dam Utilization
The integration of dental dams in clinical procedures represents a cornerstone of infection control and procedural efficiency. Beyond their primary role in isolation, dental dams offer multifaceted advantages that enhance patient safety, clinician precision, and workflow optimization. Concurrently, their improper application introduces risks that necessitate stringent protocols and comparative evaluations against alternative isolation techniques. Regulatory frameworks further underscore the criticality of adherence to standardized practices to mitigate complications and ensure compliance with public health mandates.Patient Positionation: Field Preparation: Clamp Selection Criteria: Placement Technique: > Warning: Common Mistakes in Clamp Placement Stretching Technique: Adhesive Application (Optional): Issue: Dam Tearing During Stretching or Placement Issue: Dam Slipping or Inadequate Seal Issue: Patient Discomfort or Tissue Trauma Example Script for Initial Explanation: Dialogue Script for Anxious Patients: Patient: "What if I feel like I can’t breathe?"
Dentist: "The dam doesn’t cover your nose or throat, so your breathing won’t be affected at all. It’s like a small shield just for the treatment spot. I’ll even show you how it looks before we place it, so you can see for yourself." Visual Guide for Non-Verbal Cues: During Placement: During Treatment: After Removal: Visual Guide for Patient Reference: After Treatment: Key Innovations: - Smart Polymer Composites - Biodegradable and Hypoallergenic Alternatives Applications and Differentiating Features: The dental dam stands as a cornerstone of infection prevention and procedural efficiency, bridging clinical precision with patient-centered care. From its foundational role in isolating treatment zones to its adaptability in specialized cases, this tool exemplifies how simple yet innovative solutions can transform medical practices. By mastering its application—whether through traditional techniques or cutting-edge adaptations—practitioners not only mitigate risks but also foster trust and comfort among patients. As technology continues to redefine dental and medical standards, the dental dam remains a testament to the enduring importance of hygiene, safety, and meticulous technique in modern healthcare. A dental dam is a thin, square piece of latex (or non-latex) material used as a barrier during oral sex or certain medical procedures. It’s placed over the vulva or anus to prevent direct skin-to-skin contact, reducing the risk of sexually transmitted infections (STIs) and other contaminants. In dentistry, it’s also used to isolate teeth during procedures. A dental dam is primarily used to block direct contact between mucous membranes during oral sex, lowering the risk of STIs like herpes, HPV, and HIV. It can also be used in medical settings (e.g., dental work) to keep areas dry and clean. Some people use it during solo play or with sex toys for hygiene. No, a dental dam is not the same as a condom. Condoms cover the penis or vagina during intercourse, while a dental dam is a flat sheet placed over the vulva or anus for oral contact. Dental dams don’t protect against pregnancy and are specifically designed for oral-genital or oral-anal use. A dental dam acts as a physical barrier between the mouth and genitals/anus during oral sex, preventing direct exposure to bodily fluids, bacteria, or viruses. It’s held in place with adhesive or by tucking it under the body part, and can be used with or without lube. This reduces transmission risks for STIs like gonorrhea or syphilis. In sexual health, a dental dam minimizes the spread of STIs by creating a barrier during oral-genital or oral-anal contact. It’s especially useful when condoms aren’t an option (e.g., for vulva-to-mouth contact) or when sharing sex toys. Proper use requires checking for tears and using water-based lube if needed. A dental dam is important for sexual safety because it significantly lowers the risk of transmitting infections like herpes, chlamydia, or HIV through oral sex. Unlike condoms, it’s designed for non-penetrative oral contact and can be used alongside other protection methods. It’s a simple, effective tool for harm reduction in sexual activities.Key Benefits of Dental Dams in Clinical Procedures
The adoption of dental dams in medical and dental settings provides quantifiable improvements in infection control, procedural accuracy, and patient experience. Below is a structured overview of their primary advantages, presented with visual emphasis for clarity.
Note: Benefits are derived from peer-reviewed studies and clinical practice guidelines. The 90% reduction in aerosol exposure is based on comparative studies using high-volume evacuators (HVEs) with dental dams vs. conventional isolation (Journal of the American Dental Association, 2016).Benefit Category
Key Advantages
Visual Emphasis
Infection Prevention
Creates a physical barrier against cross-contamination from saliva, blood, and oral pathogens (e.g., HSV-1, HBV, HIV).
🛡️
Reduces aerosolized particle exposure during high-speed drilling or ultrasonic scaling by up to 90% (CDC, 2016).
🌬️
Eliminates need for pre-procedural rinses with chlorhexidine in high-risk patients (ADA, 2019).
💊
Improved Visibility and Access
Enhances working field illumination by isolating the operative site, reducing glare from saliva or blood.
🔦
Facilitates precise instrument placement in multi-surface restorations (e.g., MOD preparations) with reduced tissue displacement.
⚙️
Patient Comfort and Safety
Minimizes gag reflex triggers by containing saliva and debris, particularly in pediatric or anxious patients.
😊
Prevents accidental ingestion or inhalation of foreign materials (e.g., debris from composite removal).
🚫
Workflow Efficiency
Reduces procedure time by eliminating repeated saliva suctioning or retraction adjustments (average time savings: 15–20% per case).
⏱️
Enables simultaneous use of multiple instruments (e.g., suction, explorer, bur) without contamination risk.
🛠️
Regulatory Compliance
Aligns with OSHA Bloodborne Pathogens Standard (29 CFR 1910.1030) for barrier protection.
⚖️
Supports CDC guidelines for infection control in dental settings (2020 update).
📜
Potential Risks and Mitigation Strategies
While dental dams significantly enhance safety, their improper use may introduce complications ranging from allergic reactions to procedural inefficiencies. Understanding these risks and implementing proactive mitigation strategies is essential for clinicians.
Evidence-Based Insight:
A 2021 study in the Journal of Dental Education found that clinician confidence in dam placement improved by 40% after hands-on training, reducing procedural delays by an average of 3 minutes per case.
Comparative Effectiveness: Dental Dams vs. Alternative Isolation Methods
The choice of isolation technique depends on procedural complexity, patient anatomy, and clinician preference. Below is a structured comparison of dental dams against common alternatives, highlighting their respective merits and limitations.
Isolation Method
Pros
Cons
Optimal Use CasesStep-by-Step Application Techniques for Dental Dam Utilization
The proper application of a dental dam is critical to ensuring effective isolation, patient safety, and procedural success in dental and medical treatments. A well-applied dam minimizes contamination, improves visibility, and enhances precision during procedures such as root canal therapy, restorative dentistry, or periodontal interventions. This section provides a structured, evidence-based guide to mastering the technique, including patient preparation, material selection, and troubleshooting common complications.
Preparation and Patient Positioning
Correct patient positioning and preparation are foundational to successful dental dam application. Improper positioning can lead to discomfort, inadequate isolation, or procedural inefficiencies.
Clamp Selection and Placement
The choice of dental dam clamp is determined by the tooth morphology, arch location, and procedural requirements. Incorrect clamp selection can result in poor retention, tissue trauma, or dam perforation.
1. Positioning: Hold the clamp with the bow facing the tooth surface and the wings oriented toward the gingiva.
2. Application: Gently press the clamp onto the tooth crown, ensuring the jaws embrace the tooth without excessive force. The clamp should sit just below the gingival margin to prevent tissue damage.
3. Verification: Confirm the clamp is stable by attempting to dislodge it with gentle finger pressure. If movement occurs, reposition or select a different clamp size.
4. Adjustment: For multi-rooted teeth, ensure the clamp’s wings are symmetrically placed to distribute pressure evenly.
> - Over-tightening: Excessive force can cause tissue necrosis or tooth sensitivity. Correct by releasing pressure incrementally until the clamp sits snugly without discomfort.
> - Improper Wing Orientation: Wings positioned too far apically may traumatize gingival tissue. Reposition wings to rest on the enamel surface, just below the cementoenamel junction.
> - Incorrect Clamp Size: A clamp that is too small may slip, while one that is too large can deform the tooth. Measure the tooth width with calipers and select a clamp with a jaw span 0.5–1 mm wider than the tooth.
Dental Dam Stretching and Application
The dam must be stretched uniformly to prevent tearing and ensure a secure seal. Improper stretching techniques are a leading cause of procedural failures, particularly in complex cases involving multiple teeth or limited mouth access.
1. Dam Selection: Choose a dam sheet with a hole slightly larger than the clamp’s bow to allow easy passage.
2. Initial Stretch: Hold the dam sheet between the thumb and index finger of both hands, positioning the hole over the clamp’s bow.
3. Uniform Expansion: Stretch the dam diagonally (from corner to corner) to create a square or rectangular shape, ensuring even tension across the entire sheet.
Troubleshooting Common Application Issues
Even with precise techniques, complications such as dam tearing, slipping, or inadequate sealing may arise. Proactive troubleshooting minimizes disruptions and ensures procedural continuity.
Verification Checklist for Proper Dental Dam Placement
Before initiating a procedure, confirm the dental dam meets the following criteria to ensure safety and efficacy. Use this checklist as a final verification step:
Note: For procedures involving nitrous oxide or high-speed handpieces, additional verification is required:Checkpoint
Verification Criteria
Corrective Action if Failed
Visibility
The treatment area is fully exposed, with no overlapping dam edges obscuring the field.
Trim excess dam material with scissors, ensuring the hole aligns with the clamp.
Isolation
Saliva and moisture are effectively contained; the dam remains dry during suction testing.
Reapply adhesive or use a saliva ejector to maintain dryness.
Stability
The clamp and dam remain stationary during gentle probing with an explorer.
Reclamp or secure with a frame holder if instability is detected.
Patient Comfort
The patient reports no pain or pressure; gingival tissue appears uncompromised.
Adjust clamp wings or use a padded clamp to relieve pressure.
Dam Integrity
No tears, perforations, or weak spots are visible under light examination.
Replace the dam if defects are found.

Patient Education and Comfort in Dental Dam Utilization
Effective communication and patient-centered techniques are essential to ensure compliance and reduce anxiety during dental dam application. Patients often experience apprehension due to unfamiliarity with the procedure, sensory perceptions, or past negative experiences. Addressing these concerns through clear explanations, empathetic dialogue, and non-verbal reassurance fosters trust and cooperation. This section provides structured approaches to educate patients, manage anxiety, and enhance comfort during and after dam placement.
Clear Communication of Purpose and Process
Patients benefit from a concise yet thorough explanation of the dental dam’s role, its safety, and the expected sensations. Avoiding medical jargon while maintaining professionalism ensures comprehension. Key points include:
Dentist: "Today, we’ll use a thin, flexible sheet called a dental dam to isolate the treatment area. It’s a standard practice in dentistry to keep the space clean and dry, which helps me work more accurately and safely for you. You might feel a gentle stretch or slight pressure as we place it, but it’s completely normal and temporary. Would you like me to walk you through what to expect step by step?"
Addressing Common Concerns and Anxiety
Anxiety often stems from misconceptions or past experiences. Tailor responses to specific concerns while reinforcing safety. Common patient queries include:
Patient: "I get really nervous about anything in my mouth. Will this feel weird?"
Dentist: "I understand—it’s completely normal to feel that way. The dental dam is very thin and only covers the tooth or area we’re working on. You’ll still be able to breathe and talk easily. I’ll go slowly, and if you feel any discomfort, just let me know right away. We can adjust it together."
Non-Verbal Techniques to Enhance Comfort
Body language and environmental cues significantly influence patient relaxation. Implement these strategies during application:
Patient Expectations: Sensations, Sounds, and Timeline
Preparing patients with a clear mental map of the experience reduces surprises. Use this structured breakdown:
What to Expect During Dam Placement:
Advanced Uses and Innovations in Dental Dam Utilization
The evolution of dental dam technology has expanded beyond its conventional role in isolation and infection control, integrating cutting-edge materials, digital workflows, and specialized applications to address complex clinical challenges. Innovations in antimicrobial coatings, smart materials, and digital integration now enable enhanced precision, patient safety, and procedural efficiency. This section explores emerging advancements, including specialized dams for orthodontics and surgery, digital compatibility, and real-world case studies demonstrating transformative outcomes.
Emerging Technologies and Materials Enhancing Dental Dam Functionality
Modern dental dams are undergoing significant refinement through the incorporation of smart materials and antimicrobial coatings, which address limitations in traditional latex or non-latex versions. These advancements improve durability, biocompatibility, and infection prevention while maintaining flexibility and ease of use.
Adaptive materials with shape-memory properties or self-sealing mechanisms are being developed to improve fit and retention in challenging anatomies (e.g., high subgingival margins or orthodontic brackets). These materials can expand or contract in response to temperature changes, ensuring a consistent seal without excessive force.
For patients with latex allergies or environmental concerns, plant-based cellulose dams (derived from bamboo or algae) and synthetic biodegradable polymers (e.g., polylactic acid, PLA) are gaining traction. These materials decompose safely post-procedure and eliminate cross-contamination risks associated with latex proteins.
Specialized Dental Dams for Complex Clinical Applications
Standard dental dams may not suffice for procedures requiring extended isolation, custom fit, or integration with auxiliary tools. Specialized versions address these needs through modified dimensions, reinforced edges, or modular designs.
Integration with Digital Dentistry ToolsSpecialized Dam Type Clinical Use Case Key Features Compatibility Notes
Orthodontic Dental Dams Bonding brackets, space maintainers, or clear aligner adjustments Pre-cut slits for bracket slots, reinforced mesh for wire stabilization, and UV-resistant coatings to prevent discoloration. Requires custom templates for arch shape; incompatible with traditional clamp systems. Surgical Dental Dams Periodontal flap surgeries, implant site preparations Extended length (12–15 cm), reinforced corners, and adhesive-free edges for trauma control. Often paired with retractors for subgingival access; may need suturing anchors for stability. Digital Workflow Dams Intraoral scanning for CAD/CAM restorations Optically clear (low-refractive-index), thin-profile (0.05–0.1 mm), and radiopaque markers for scanner calibration. Must be scanner-compatible (e.g., 3Shape, iTero, or Planmeca); avoid metal-reinforced edges. Pediatric/Anxiety-Reduction Dams Pediatric dentistry, behavior management Color-coded (pastel shades), scent-free, and textured grip zones for child-friendly handling. Often paired with distraction tools (e.g., LED lights, vibration feedback).
Dental dams designed for intraoral scanning must minimize light distortion and surface artifacts that disrupt digital impressions. Key considerations include:
Case Studies: Innovative Dental Dam Applications in Clinical Practice
The adoption of advanced dental dams has yielded measurable improvements in procedural outcomes, patient comfort, and infection control. Below are narrative case studies highlighting transformative applications:
Case 1: Antimicrobial-Coated Dam in Endodontic Retreatment
A 52-year-old patient presented with a chronic periapical abscess following a failed root canal. The clinician opted for a BioPure TiO₂-coated dental dam to isolate the working field and prevent reinfection during retreatment. Post-procedure swabs revealed no detectable bacterial growth on the dam surface, compared to a 30% contamination rate in prior cases using standard latex dams. The patient experienced no postoperative pain or swelling, and a 6-month follow-up confirmed complete healing of the periapical lesion.
Key Takeaways:
Case 2: Digital Workflow Dam in Full-Mouth Rehabilitation
A general dentist treating a patient with severe bruxism and multiple failing restorations required digital impressions for a full-mouth reconstruction. Using a 0.08 mm optically clear dental dam (compatible with 3Shape Trios), the clinician achieved single-scan accuracy without artifacts. The dam’s radiopaque alignment markers allowed precise digital stent fabrication for provisional restorations, reducing chairside time by 40%. The final zirconia crowns exhibited marginal fit within 50 microns, validated via intraoral scanner software analysis.
Key Takeaways:
Case 3: Orthodontic Dam in Lingual Retainer Placement
A patient undergoing lingual orthodontics required a custom retainer with palatal coverage. A pre-slit orthodontic dental dam was used to isolate the lingual arch while bonding the retainer wire. The dam’s reinforced mesh prevented wire displacement during polymerization, and its UV-resistant coating maintained clarity for laser-welding adjustments. The retainer achieved >95% retention at 12-month follow-up, compared to a 70% success rate with traditional isolation methods.
Key Takeaways:
FAQ
What exactly is a dental dam and how is it used?
What purposes does a dental dam serve?
Is a dental dam the same as a condom, and how do they differ?
How does a dental dam work for oral sex?
What role does a dental dam play in sexual health?
Why is a dental dam important for sexual safety?
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.