Knee Joint What Type Of Joint Anatomical Biomechanical Analysis

Published

Table of Contents

The knee joint represents one of the most complex and functionally critical articulations in the human musculoskeletal system, serving as the primary load-bearing hinge between the femur and tibia while accommodating dynamic movements essential for locomotion. Classified anatomically as a modified hinge joint, its unique structural design—combining elements of hinge, condyloid, and planar articulations—enables not only flexion and extension but also limited rotational and accessory motions. This dual functionality demands precise coordination between bony surfaces, ligamentous stabilizers, and soft-tissue structures, all of which contribute to its vulnerability to injury and degenerative conditions. Understanding its classification, biomechanical behavior, and pathological adaptations is fundamental for clinicians, biomechanists, and rehabilitation specialists aiming to optimize joint integrity and restore functional mobility.

Beyond its mechanical role, the knee’s stability relies on an intricate interplay of hyaline cartilage, fibrocartilage menisci, and a network of ligaments (including the ACL, PCL, MCL, and LCL) that resist excessive translation and torsion. Disruptions in these components—whether through acute trauma, repetitive stress, or age-related degeneration—can precipitate cascading effects on gait mechanics, muscle activation patterns, and long-term joint congruency. This analysis explores the knee’s anatomical classification, ligamentous stabilization mechanisms, biomechanical ranges of motion, and clinical assessment techniques, while examining adaptive strategies and evidence-based interventions to mitigate dysfunction.

knee joint what type of joint

Classification and Structure of the Knee Joint

The knee joint represents one of the most complex and biomechanically sophisticated articulations in the human body, serving as a critical weight-bearing and load-transmitting interface between the lower limb and the pelvis. Anatomically classified as a modified hinge joint, its primary function is flexion-extension, while limited medial-lateral rotation and accessory movements occur during specific phases of gait or functional activities. This classification arises from its composite structure, combining elements of a hinge joint (for primary motion) and a modified condylar joint (enabling rotational components under constrained conditions). The knee’s stability and functionality depend on its bony architecture, articular surfaces, and associated soft-tissue structures, which collectively distribute forces across multiple planes.

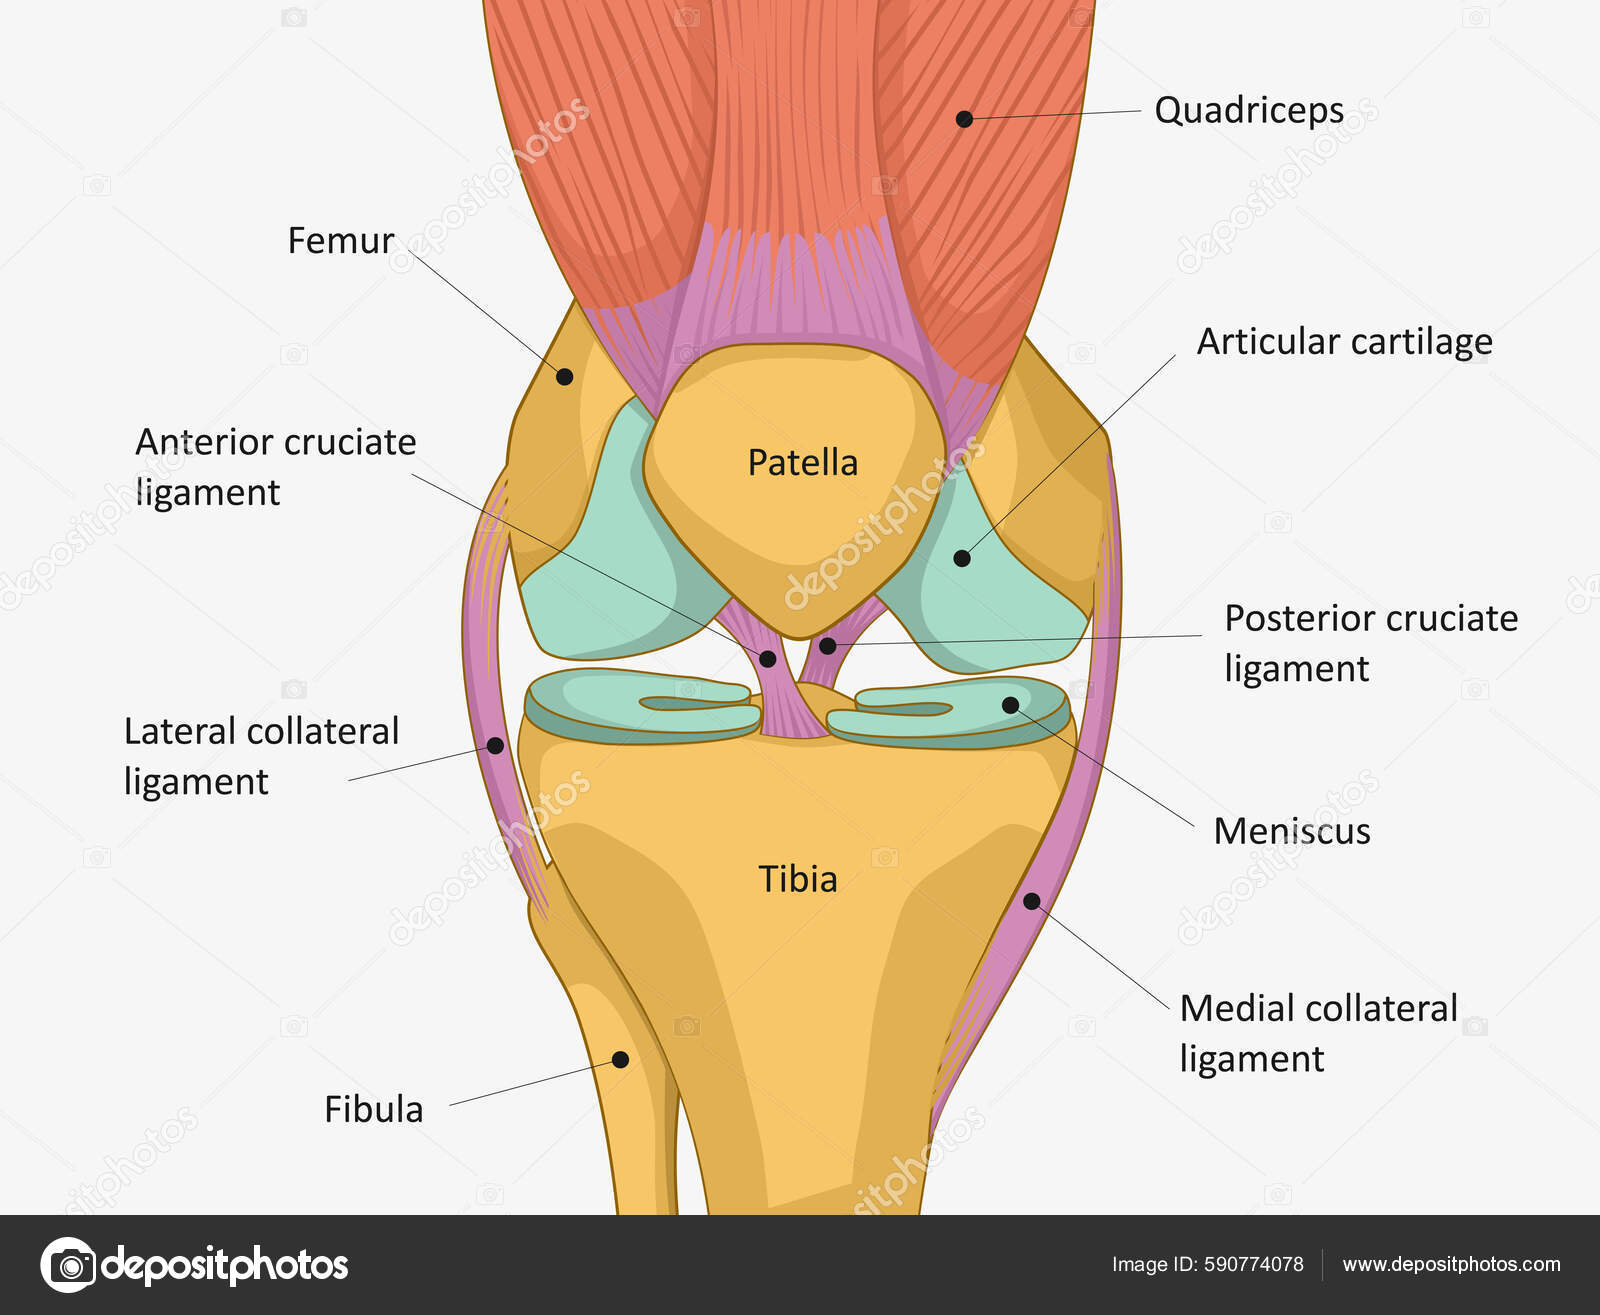
The knee joint is formed by the articulation of three primary bony components: the femur (thigh bone), the tibia (shin bone), and the patella (kneecap). These structures interact through specialized articular surfaces lined with distinct cartilage types—hyaline cartilage (for smooth gliding) and fibrocartilage (for shock absorption and stability)—each playing a critical role in load distribution, joint congruency, and protection against degenerative changes. The following sections detail the anatomical classification, bony components, and articular surface morphology of the knee joint, including their functional adaptations.

Anatomical Classification and Primary Motion Characteristics

The knee joint is classified as a modified hinge joint due to its dominant flexion-extension axis while incorporating secondary rotational capabilities. Unlike a pure hinge joint (e.g., the elbow), the knee permits screw-home mechanism—a terminal rotation of the tibia relative to the femur during full extension, which enhances stability through ligamentous tension. This classification is supported by the following structural features:

- Bicondylar Articulation: The distal femur and proximal tibia form two distinct condylar surfaces (medial and lateral), allowing for differential motion between the compartments.

  • Patellofemoral Articulation: The patella engages with the femoral trochlea, converting quadriceps forces into a mechanical advantage for extension while protecting the joint.
  • Ligamentous Constraints: The anterior cruciate ligament (ACL) and posterior cruciate ligament (PCL) limit anterior-posterior translation, while the collateral ligaments (medial/lateral) restrict varus-valgus stress.
  • The knee’s modified hinge classification reflects its evolutionary adaptation to bear axial loads while accommodating dynamic movements, distinguishing it from simpler synovial joints.

    Bony Components and Articular Surface Morphology

    The knee joint’s bony architecture is designed to distribute mechanical stresses efficiently across its three primary components: the femur, tibia, and patella. Each structure contributes unique articular surfaces that influence joint congruency, stability, and range of motion.

    1. Femoral Condyles and Tibial Plateau

    The distal femur features two condylar surfaces—medial and lateral—which articulate with the corresponding tibial plateaus. These surfaces exhibit distinct geometric properties:

    - Medial Condyle:

  • Shape: Elongated and convex anteroposteriorly, with a larger articular surface area.
  • Cartilage: Thicker hyaline cartilage (up to 3–4 mm) to accommodate higher compressive forces.
  • Function: Primarily responsible for weight-bearing during stance phase and medial compartment stability.
  • - Lateral Condyle:

  • Shape: Rounded and slightly concave, with a smaller contact area.
  • Cartilage: Thinner hyaline cartilage (2–3 mm) but reinforced by the fibula’s lateral support.
  • Function: Facilitates rotational movements (e.g., during the screw-home mechanism) and absorbs shear forces.
  • The tibial plateaus are reciprocally shaped to match the femoral condyles, with the medial plateau being broader and slightly concave, while the lateral plateau is more convex and elevated (due to the fibular head’s influence). The intercondylar eminence (anterior and posterior horns) separates the plateaus and serves as an attachment site for the cruciate ligaments.

    The medial femoral condyle’s greater surface area and thicker cartilage reflect its role as the primary weight-bearing compartment, whereas the lateral condyle’s geometry supports dynamic rotational movements.

    Articular Surface Alignment and Cartilage Distribution

    The knee’s articular surfaces are optimized for load transmission through a combination of hyaline cartilage (covering femoral/tibial condyles and patella) and fibrocartilage (menisci). The following table summarizes the key features of these surfaces:
    Articular Surface Cartilage Type Functional Role Key Structural Adaptations
    Medial Femoral Condyle Hyaline Cartilage Primary weight-bearing; resists compressive forces during stance. Thicker cartilage (3–4 mm); convex AP curvature; larger contact area.
    Lateral Femoral Condyle Hyaline Cartilage Facilitates rotation; absorbs shear forces. Thinner cartilage (2–3 mm); rounded convexity; smaller contact area.
    Medial Tibial Plateau Hyaline Cartilage Distributes axial loads; stabilizes medial compartment. Broad and concave; reinforced by MCL and deep MCL attachments.
    Lateral Tibial Plateau Hyaline Cartilage Supports rotational movements; reduces lateral compartment stress. Convex; elevated by fibular head; shallower than medial plateau.
    Patellar Facets Hyaline Cartilage Enhances quadriceps leverage; protects joint during extension. Three facets (medial, lateral, odd); thickest cartilage (6–7 mm).
    Medial/Lateral Menisci Fibrocartilage Shock absorption; increases joint congruency; stabilizes translation. Semicircular shape; medial meniscus C-shaped, lateral meniscus O-shaped; attached to tibial plateau via coronary ligaments.
    The menisci, composed of fibrocartilage, act as secondary shock absorbers, increasing the contact area between the femur and tibia by up to 70%, thereby reducing peak stresses by 50% during weight-bearing.

    Patellofemoral Articulation and Functional Adaptations

    The patella, the largest sesamoid bone in the body, articulates with the femoral trochlea, forming the patellofemoral joint. This articulation serves three critical functions:

    1. Mechanical Advantage: The patella increases the leverage of the quadriceps tendon by 30–50%, enhancing extension torque.
    2. Joint Protection: It shields the anterior knee from direct trauma and reduces quadriceps tendon friction.
    3. Load Distribution: During flexion, the patella tracks within the trochlear groove, distributing forces across its three articular facets (medial, lateral, and odd facets).

    The trochlear groove of the femur exhibits a sulcus angle (average 143°), which influences patellar tracking. Deviations (e.g., shallow grooves or dysplasia) can predispose to patellofemoral pain syndrome or instability. The patellar cartilage is the thickest in the body (6–7 mm), reflecting its role in withstanding repetitive compressive stresses during activities such as squatting or stair climbing.

    The patellofemoral joint’s design exemplifies a trade-off between mobility and stability, where the patella’s mobility allows for deep flexion but requires precise tracking to prevent lateral subluxation.

    Ligamentous and Soft-Tissue Stabilization of the Knee Joint

    The knee joint’s stability relies on a complex interplay of ligamentous and soft-tissue structures, which collectively resist excessive motion, distribute mechanical loads, and maintain proprioceptive feedback. While bony anatomy provides inherent constraints, ligaments and secondary stabilizers—such as the menisci, joint capsule, and tendinous structures—augment stability through passive and active mechanisms. Disruption of these structures, particularly through traumatic injury, alters joint biomechanics, leading to compensatory movements and long-term degenerative changes. This section examines the primary ligamentous stabilizers, their mechanical contributions, and the roles of secondary stabilizers in load distribution and proprioception, followed by an analysis of injury-induced biomechanical alterations.

    Primary Ligamentous Stabilizers and Their Mechanical Contributions

    The knee’s primary ligaments—anterior cruciate ligament (ACL), posterior cruciate ligament (PCL), medial collateral ligament (MCL), and lateral collateral ligament (LCL)—provide distinct yet complementary constraints to knee motion. Their attachment points, fiber orientations, and stress vectors determine their functional roles in resisting anterior-posterior (AP) translation, rotational forces, and valgus/varus stresses.

    Anterior Cruciate Ligament (ACL)

  • Attachment Points: Originates from the posteromedial aspect of the lateral femoral condyle and inserts on the anteromedial tibial plateau (within the intercondylar eminence).
  • Stress Vectors: Primarily resists anterior tibial translation (via its anteromedial bundle) and internal rotation of the tibia. The posterolateral bundle tightens in extension, limiting hyperextension.
  • Mechanical Contribution:
  • AP Stability: Prevents excessive anterior shift of the tibia relative to the femur, particularly under load-bearing conditions (e.g., during deceleration in sports).
  • Rotational Control: Acts as a secondary restraint to internal rotation, especially in flexion (>30°).
  • Valgus Stress: Provides minor resistance to valgus forces when the knee is near full extension.
  • Clinical Relevance: ACL deficiency increases risk of secondary meniscal tears (due to increased tibiofemoral shear forces) and osteoarthritis (via altered contact mechanics).
  • Posterior Cruciate Ligament (PCL)

  • Attachment Points: Originates from the anterolateral aspect of the medial femoral condyle and inserts on the posterior intercondylar area of the tibia.
  • Stress Vectors: Resists posterior tibial translation (via its anterolateral bundle) and external rotation of the tibia. The posteromedial bundle tightens in flexion.
  • Mechanical Contribution:
  • AP Stability: Primary restraint to posterior tibial displacement (e.g., during dashboard injuries in motor vehicle accidents).
  • Rotational Control: Limits external rotation, particularly in flexion.
  • Load Distribution: Acts as a secondary stabilizer to valgus/varus stresses when the knee is flexed.
  • Clinical Relevance: PCL injuries often present with posterior sag sign and may lead to patellofemoral pain due to altered tibiofemoral alignment.
  • Medial Collateral Ligament (MCL)

  • Attachment Points: Superficial fibers attach from the medial femoral epicondyle to the medial tibial condyle; deep fibers (coronary ligament) blend with the medial meniscus.
  • Stress Vectors: Resists valgus stresses and external rotation of the tibia. Tightens progressively from extension to flexion.
  • Mechanical Contribution:
  • Valgus Stability: Primary restraint to valgus forces (e.g., during lateral impact or cutting maneuvers).
  • Rotational Coupling: Works synergistically with the ACL to limit internal rotation.
  • Meniscal Protection: Deep fibers provide indirect meniscal stability by limiting excessive tibial rotation.
  • Clinical Relevance: MCL injuries are common in contact sports and often heal conservatively due to its rich vascular supply.
  • Lateral Collateral Ligament (LCL)

  • Attachment Points: Attaches from the lateral femoral condyle to the head of the fibula, with no meniscal attachment.
  • Stress Vectors: Resists varus stresses and internal rotation of the tibia. Remains isometric across knee flexion.
  • Mechanical Contribution:
  • Varus Stability: Primary restraint to varus forces (e.g., during medial impact).
  • Rotational Control: Limits internal rotation, particularly in extension.
  • Biceps Femoris Synergy: The arcuate complex (including the popliteofibular ligament) augments LCL function in resisting posterior tibial translation.
  • Clinical Relevance: LCL injuries are less common than MCL injuries but often coexist with posterolateral corner (PLC) injuries, leading to multiligamentous instability.
  • Comparative Analysis of Secondary Stabilizers

    While primary ligaments provide the knee’s gross stability, secondary stabilizers—including the menisci, joint capsule, and tendinous structures—enhance load distribution, proprioception, and fine-tuned motion control. Their contributions are often overlooked but critical in maintaining joint homeostasis.

    Menisci
    The medial and lateral menisci function as fibrocartilaginous shock absorbers, distributing 50–70% of the compressive load across the tibiofemoral joint. Their structural and biomechanical roles include:

  • Load Transmission:
  • Medial Meniscus: Bears 50–80% of the load in the medial compartment due to its C-shaped morphology and deeper attachment to the tibial plateau.
  • Lateral Meniscus: More mobile, with a posterior root attachment that resists hoop stresses during flexion.
  • Joint Congruency:
  • Deepen the tibial plateau, increasing contact area by 68% (lateral) and 55% (medial) compared to meniscectomized knees.
  • Hoop Stress Mechanism: Radial fibers resist tibiofemoral shear forces, preventing extrusion during weight-bearing.
  • Proprioception:
  • Mechanoreceptors (Ruffini endings, Pacinian corpuscles) detect joint position and movement, contributing to neuromuscular control.
  • Clinical Impact of Meniscal Injury:
  • Tear Propagation: Radial tears disrupt hoop stresses, leading to joint space narrowing and osteoarthritis.
  • Meniscectomy Risks: Accelerates tibiofemoral contact pressures by 200–300%, increasing degenerative changes.
  • Joint Capsule and Synovium

  • Anatomical Features:
  • Suprapatellar, infrapatellar, and lateral recessions expand during knee flexion, accommodating volume changes.
  • Synovial membrane secretes synovial fluid, reducing friction and providing nutrient transport to avascular structures (e.g., menisci).
  • Mechanical Contribution:
  • Passive Constraint: Limits hyperextension and excessive flexion through capsular tightness.
  • Proprioceptive Feedback: Free nerve endings in the capsule contribute to knee position sense, particularly in low-load conditions.
  • Pathological Changes:
  • Synovitis (e.g., in rheumatoid arthritis) increases intra-articular pressure, compromising joint stability.
  • Capsular Laxity: Seen in ligamentous insufficiency (e.g., chronic ACL deficiency), leading to joint hypermobility.
  • Popliteus Tendon and Posterolateral Corner (PLC)
    The popliteus tendon and posterolateral structures (LCL, popliteofibular ligament, fabellofibular ligament) form a dynamic stabilizer complex critical for rotational control.
  • Popliteus Tendon:
  • Attachment Points: Originates from the lateral femoral condyle, inserts on the posterior tibia (forming the popliteal hiatus).
  • Function:
  • Internal Rotation: Actively unlocks the knee from screw-home mechanism (terminal extension) by internally rotating the tibia.
  • Secondary Restraint: Assists the ACL in resisting posterior tibial translation and external rotation.
  • Injury Implications: Popliteus tears may mimic PLC deficiency, leading to posterolateral rotatory instability.
  • Posterolateral Corner (PLC) Complex:
  • Components: LCL, popliteofibular ligament, fabellofibular ligament, lateral gastrocnemius tendon.
  • Mechanical Role:
  • Resists varus stress, external rotation, and posterior tibial translation in flexion.
  • Coupled Motion: PLC injuries often present with positive dial test (excessive external rotation of the tibia at 30° and 90° flexion).
  • Clinical Significance: PLC injuries are associated with multiligamentous trauma (e.g., dashboard injuries) and
  • knee joint what type of joint - Ilustrasi 2

    Biomechanics and Range of Motion of the Knee Joint

    The knee joint exhibits complex biomechanical behavior, integrating multiple degrees of freedom to facilitate dynamic weight-bearing and non-weight-bearing movements. Its functional efficiency relies on the interplay between bony congruency, ligamentous constraints, and muscular stabilization, which collectively determine its range of motion (ROM) and stability. Understanding these mechanics is critical for assessing pathological deviations, designing rehabilitation protocols, and optimizing performance in athletic or clinical settings.

    The knee’s biomechanical function is governed by its triplanar motion, where flexion, extension, and accessory motions (e.g., rotation, glide) occur in a coordinated manner. These movements are influenced by the joint’s closed-packed and loose-packed positions, which dictate ligamentous tension and articular contact areas. Additionally, weight-bearing versus non-weight-bearing conditions alter muscle activation patterns, joint loading, and compensatory strategies, necessitating a differential analysis for clinical or biomechanical evaluation.

    Degrees of Freedom and Range of Motion

    The knee joint possesses six degrees of freedom (DOF), though not all are equally pronounced due to its structural constraints. The primary motions—flexion/extension, internal/external rotation, and accessory motions (glide, spin, roll)—occur within specific ROM limits, which vary based on joint position and loading conditions.

    Flexion/Extension

  • Non-weight-bearing ROM: 0° (full extension) to 135–150° (flexion), with elite athletes (e.g., gymnasts) achieving up to 170° through hypermobility adaptations.
  • Weight-bearing ROM: Reduced to 0–120° due to femoral condylar rollback and tibial plateau constraints, particularly in deep flexion where the posterior cruciate ligament (PCL) limits further movement.
  • Key anatomical landmarks:
  • 0° extension: Achieved when the femur and tibia are aligned in the sagittal plane, with the femoral condyles fully seated on the tibial plateau.
  • 90° flexion: The patella disengages from the trochlear groove, and the PCL becomes taut, preventing hyperextension.
  • Accessory Rotations

  • Open-chain (non-weight-bearing) rotation:
  • Internal rotation (medial tibial torsion): 10–30° at 90° flexion, increasing to 40° in deep flexion due to posterolateral corner (PLC) laxity.
  • External rotation (lateral tibial torsion): 20–40° at 90° flexion, constrained by the anterior cruciate ligament (ACL) and medial collateral ligament (MCL).
  • Closed-chain (weight-bearing) rotation:
  • Screw-home mechanism: The final 5–10° of extension locks the knee via external rotation of the tibia relative to the femur, stabilized by the ACL and menisci.
  • Deep flexion (>120°): The tibia internally rotates to accommodate femoral condylar shapes, a motion critical for activities like squatting or kneeling.
  • Accessory Motions (Arthrokinematics)
    These motions—spin, roll, and glide—occur concurrently with osteokinematic movements and are essential for joint lubrication and congruency.

  • Rollback: During flexion, the femur rolls posteriorly on the tibia (up to 10–15 mm in deep flexion), facilitated by the PCL and menisci.
  • Glide (translation): The tibia glides anteriorly during extension (up to 5–10 mm) and posteriorly during flexion, influenced by ligamentous tension.
  • Spin: Occurs around a vertical axis, particularly in open-chain rotation (e.g., pivoting during cutting maneuvers).
  • Clinical Relevance:
    Accessory motion deficits (e.g., restricted posterior tibial glide) correlate with patellofemoral pain syndrome or ACL-deficient knees, where compensatory motions increase joint stress.

    Closed-Packed and Loose-Packed Positions

    The knee’s closed-packed position (CPP) and loose-packed position (LPP) define the joint’s maximal congruency and ligamentous tension, respectively, and are critical for assessment and mobilization techniques.

    Closed-Packed Position (Maximal Congruency and Ligamentous Tension)

  • Definition: The position where joint surfaces are maximally congruent, and ligaments are taught, minimizing accessory motion.
  • Knee CPP:
  • Full extension (0°) with external tibial rotation (screw-home mechanism).
  • Ligamentous tension: ACL, MCL, and PLC are maximally taut, providing static stability.
  • Clinical relevance:
  • Stress testing (e.g., Lachman test, valgus/varus stress) is performed near CPP to isolate ligamentous integrity.
  • Post-surgical assessment (e.g., ACL reconstruction) evaluates ROM restoration toward CPP to ensure functional stability.
  • Loose-Packed Position (Minimal Congruency and Ligamentous Laxity)

  • Definition: The position where joint surfaces are least congruent, and ligaments are relaxed, allowing maximal accessory motion.
  • Knee LPP:
  • 20–30° of flexion with neutral rotation.
  • Ligamentous tension: Reduced compared to CPP, permitting mobilization techniques (e.g., posterior glide of the tibia to improve flexion).
  • Clinical relevance:
  • Joint mobilization (e.g., Grade III oscillations) is most effective in LPP to restore ROM without excessive stress.
  • Patient comfort: LPP is often the resting position for knee injuries (e.g., meniscal tears), as it minimizes pain during examination.
    1. Step-by-Step Analysis of CPP and LPP Transition
      The shift between CPP and LPP demonstrates the knee’s adaptive biomechanics during movement. For example:
      1. From LPP (20–30° flexion) to CPP (0° extension):
      2. The tibia externally rotates via the screw-home mechanism, engaging the ACL and tightening the PLC.
      3. The menisci shift anteriorly to accommodate femoral condylar rollback.
      4. From CPP (0° extension) to deep flexion (>90°):
      5. The tibia internally rotates, reducing ligamentous tension and allowing the femur to rollback.
      6. The PCL becomes the primary stabilizer, preventing hyperextension.
    2. Clinical Application in Joint Assessment
    3. ROM assessment: Measuring flexion/extension from LPP toward CPP identifies contracture (e.g., post-traumatic stiffness) or hypermobility (e.g., ligamentous laxity).
    4. Mobilization techniques: Applying anterior/posterior glides in LPP improves patellar tracking or tibiofemoral articulation without provoking pain.

    Biomechanical Comparison: Weight-Bearing vs. Non-Weight-Bearing Conditions

    Muscle synergies and joint loading differ significantly between weight-bearing (closed-chain) and non-weight-bearing (open-chain) activities, influencing knee stability and injury risk. The following table summarizes these differences, including key muscle activations and their biomechanical roles.
    Parameter Non-Weight-Bearing (Open-Chain) Weight-Bearing (Closed-Chain)
    Primary Motion Isolated flexion/extension, rotation, or glide (e.g., leg lifts, manual therapy). Combined flexion/extension with axial compression (e.g., squatting, walking).
    Joint Loading Low to moderate (ligamentous tension dominates). High (axial load increases joint reaction forces by 3–6× body weight during activities like stair descent).
    Muscle Synergies
    • Quadriceps (VMO emphasis): Eccentric control during flexion (e.g., terminal swing phase).
    • Hamstrings: Dynamic stabilization via ACL substitution (e.g., preventing anterior tibial translation).
    • Gastrocnemius: Assists flexion in open-chain (e.g., knee curl), but

      Pathologies and Functional Adaptations of the Knee Joint

      The knee joint is susceptible to a spectrum of degenerative, traumatic, and overuse pathologies that disrupt its biomechanical integrity, leading to altered movement patterns and compensatory adaptations. Pathologies such as osteoarthritis (OA), meniscal injuries, and patellofemoral dysfunction not only compromise joint congruency but also trigger systemic physiological responses, including muscle atrophy, ligamentous laxity, and synovial inflammation. Understanding these pathological changes and their resultant functional adaptations is critical for clinical assessment, rehabilitation strategies, and long-term joint preservation.

      The progression of knee pathologies often follows a predictable trajectory, where initial structural damage—such as cartilage fibrillation or meniscal tears—eventually leads to secondary impairments in proprioception, neuromuscular control, and dynamic stability. Compensatory mechanisms, while initially protective, can exacerbate joint stress in adjacent structures, creating a cycle of degenerative change. Clinical observations frequently reveal asymmetrical gait patterns, quadriceps inhibition, and altered hip-knee-ankle kinematics as hallmark adaptations to instability.

      Common Knee Pathologies and Their Impact on Joint Congruency

      Pathological conditions of the knee joint primarily affect congruency through alterations in articular surface contact, ligamentous tension, and soft-tissue integrity. Below are key pathologies categorized by their primary mechanism of joint disruption:
        The degenerative joint diseases (e.g., osteoarthritis, osteonecrosis) reduce congruency by degrading hyaline cartilage and subchondral bone, leading to increased joint space narrowing and altered load distribution. In primary osteoarthritis, chondrocyte-mediated cartilage breakdown results in exposed subchondral bone, forming osteophytes that further disrupt normal joint mechanics. Advanced OA often presents with a varus or valgus deformity, where medial or lateral compartment collapse forces the femur and tibia into non-physiological alignment, increasing shear stresses on the menisci and ligaments.

        Meniscal injuries, whether traumatic (e.g., bucket-handle tears) or degenerative (e.g., horizontal cleavage), compromise the knee’s shock-absorption capacity and secondary stability. The menisci contribute ~50% of the knee’s load-bearing function, and their resection—even partial—accelerates articular cartilage degeneration by 3–5 times due to increased peak contact pressures. Clinically, meniscal tears often manifest as joint-line tenderness, mechanical symptoms (locking/catching), and effusion, with long-term consequences including accelerated OA progression.

        Patellofemoral pain syndrome (PFPS) disrupts congruency through altered patellar tracking, where lateral patellar tilt or subluxation increases compressive forces on the lateral facet of the femur. This condition arises from quadriceps vastus medialis obliquus (VMO) weakness, increased Q-angle, or tight lateral retinaculum, leading to malalignment and chondromalacia patellae. Patients typically present with anterior knee pain during stair climbing, prolonged sitting, or squatting, often accompanied by patellar crepitus upon palpation.

        Traumatic injuries, such as anterior cruciate ligament (ACL) tears or tibial plateau fractures, acutely destabilize the knee by disrupting ligamentous or bony constraints. ACL deficiency, for instance, increases anterior tibial translation by 8–10 mm, leading to secondary meniscal and chondral damage. Post-traumatic osteoarthritis (PTOA) develops in ~50% of ACL-deficient knees within 10–15 years due to persistent abnormal kinematics and altered muscle activation patterns.

      Adaptive Strategies to Knee Instability and Their Clinical Manifestations

      The body employs a range of compensatory mechanisms to mitigate knee instability, though these adaptations often introduce secondary biomechanical inefficiencies. These strategies can be categorized into muscular, articular, and gait-related adaptations, each with distinct clinical presentations:
        Muscular adaptations primarily involve quadriceps and hamstring hypertrophy or atrophy, depending on the pathology. In ACL-deficient knees, quadriceps avoidance gait emerges as a protective mechanism to reduce anterior shear forces, leading to gluteus maximus and hamstring overactivation to stabilize the tibia. This pattern is observable as reduced knee flexion during stance phase and increased hip extension moment, which can contribute to low back pain or patellofemoral stress. Conversely, chronic joint effusion (e.g., in OA) triggers quadriceps inhibition due to pain and mechanical blockade, resulting in muscle atrophy (up to 30% strength loss in severe cases) and further destabilization.

        Articular adaptations include joint effusion, synovial thickening, and osteophyte formation, which alter intra-articular pressures and movement patterns. Effusion, for example, increases intra-articular pressure by ~50 mmHg during walking, reducing joint play and promoting antalgic gait (limping) to minimize pain. Osteophytes, while initially compensatory, can restrict range of motion (ROM) by 10–20° in flexion/extension and increase impingement risks during terminal knee extension.

        Gait adaptations are among the most observable clinical signs of knee pathology. In varus OA, patients adopt a trendelenburg gait (pelvic drop on the ipsilateral side) to reduce medial compartment loading, while valgus OA may lead to lateral trunk lean to shift the ground reaction force medially. Meniscal tear patients often exhibit quadriceps lag (delayed knee extension during heel strike) and reduced terminal knee extension, as the body prioritizes stability over efficiency. These adaptations, while functional in the short term, accelerate degenerative changes in adjacent joints (e.g., hip or ankle) due to altered biomechanical loading.

      Aging fundamentally alters the knee joint’s structural and functional properties, predisposing individuals to degenerative pathologies and reduced resilience to mechanical stress. Key age-related deteriorations include:
        Cartilage elasticity declines due to reduced proteoglycan content and increased water content, leading to stiffening of the articular surface. By age 70, cartilage thickness decreases by ~30%, and its compressive modulus increases by ~50%, reducing shock absorption. This change is exacerbated in senescent chondrocytes, which exhibit decreased synthetic activity and increased apoptotic rates, accelerating OA progression.

        Synovial fluid viscosity decreases with aging, primarily due to reduced hyaluronic acid concentration, which impairs lubrication and nutrient distribution. Studies show a ~40% reduction in synovial fluid viscosity by age 65, contributing to increased joint friction and pain during high-load activities. Additionally, synovial membrane inflammation becomes more prevalent, even in asymptomatic individuals, due to low-grade systemic inflammation (inflammaging).

        Ligamentous laxity increases with age due to collagen cross-link degradation and reduced fibroblast activity. The ACL and PCL lose ~10–15% of their ultimate tensile strength by age 60, while the medial collateral ligament (MCL) exhibits increased elongation under load. This laxity compromises dynamic stability, increasing the risk of strain injuries (e.g., MCL sprains) and secondary OA from altered joint kinematics.

        Age-related knee joint deterioration follows a multifactorial trajectory, where biochemical stiffening of cartilage, reduced synovial lubrication, and ligamentous laxity converge to create a vicious cycle of mechanical inefficiency and degenerative change. By age 80, ~80% of individuals exhibit radiographic OA, though only ~50% report symptomatic pain, highlighting the disparity between structural and functional decline. Rehabilitation strategies in older adults must prioritize low-impact joint loading, proprioceptive training, and anti-inflammatory interventions to mitigate these age-related vulnerabilities.

      knee joint what type of joint - Ilustrasi 3

      Clinical Assessment Techniques for Knee Joint Evaluation

      The knee joint is a complex structure subjected to high mechanical loads, making clinical assessment essential for diagnosing injuries, degenerative conditions, and functional impairments. Effective evaluation combines physical examination techniques, palpation protocols, and advanced imaging modalities to correlate clinical findings with anatomical pathology. This section provides a structured approach to assessing knee integrity, emphasizing standardized tests, palpatory techniques, and imaging interpretations to guide diagnosis and treatment planning.

      Physical Examination Tests for Knee Joint Stability and Pathology

      Physical examination remains the cornerstone of knee assessment, allowing clinicians to identify ligamentous instability, meniscal tears, patellofemoral dysfunction, and other pathologies. Tests are categorized based on their primary diagnostic focus—ligamentous integrity, meniscal function, or patellar tracking—and must be performed systematically to avoid misinterpretation. Normal findings are defined by the absence of pain, laxity, or abnormal motion, whereas abnormal findings include increased joint play, pain reproduction, or audible/visible signs of dysfunction.

      Ligamentous Stability Tests
      The anterior cruciate ligament (ACL) and posterior cruciate ligament (PCL) provide primary restraints to anterior-posterior translation, while the medial and lateral collateral ligaments (MCL/LCL) stabilize valgus-varus stresses. The following tests assess these structures:

      - Lachman Test
      Purpose: Evaluates ACL integrity by assessing anterior tibial translation.
      Technique: Patient supine with knee flexed 20–30°. Stabilize femur with one hand while applying anterior force to proximal tibia with the other. Compare bilaterally.
      Normal: Firm endpoint with <3 mm translation.
      Abnormal: Soft or absent endpoint with >5 mm translation (positive for ACL deficiency).

      - Anterior Drawer Test
      Purpose: Alternative to Lachman for ACL assessment, though less sensitive in acute injuries.
      Technique: Knee flexed 90°, feet flat. Sit on patient’s foot and pull tibia anteriorly while stabilizing femur.
      Normal: Minimal anterior movement with firm endpoint.
      Abnormal: Excessive translation (>5 mm) or sagging of tibia (indicative of ACL tear).

      - Posterior Drawer Test
      Purpose: Evaluates PCL integrity.
      Technique: Knee flexed 90°, apply posterior force to proximal tibia.
      Normal: Minimal posterior translation with firm endpoint.
      Abnormal: >5 mm translation or "subluxation" sensation (PCL insufficiency).

      - Valgus and Varus Stress Tests
      Purpose: Assess MCL and LCL stability.
      Technique: Apply valgus (abduction) or varus (adduction) force to knee at 0° (ligamentous) and 30° (capsular) flexion.
      Normal: Minimal gapping (<2 mm) with firm endpoint.
      Abnormal: Excessive gapping (>5 mm) or pain (ligamentous or capsular injury).

      Meniscal Pathology Tests
      Meniscal tears often present with joint line tenderness, mechanical symptoms (locking/catching), and positive provocation tests:

      - McMurray Test
      Purpose: Detects meniscal tears via palpation of "clicking" or "popping."
      Technique: Knee extended, apply valgus/varus stress while internally/externally rotating tibia. Flex knee while maintaining stress.
      Normal: Smooth motion without clicks.
      Abnormal: Audible/ palpable click or pain at 90° flexion (indicative of tear).

      - Apley’s Compression/Grind Test
      Purpose: Differentiates meniscal from ligamentous pathology.
      Technique: Patient prone, knee flexed 90°. Apply axial load with internal/external rotation.
      Normal: Minimal pain or resistance.
      Abnormal: Pain with rotation (meniscal tear) vs. pain with compression (ligamentous injury).

      - Bounce Home Test
      Purpose: Assesses meniscal locking.
      Technique: Passively extend knee from 90° flexion. Observe for abrupt resistance or inability to fully extend.
      Normal: Smooth extension to full range.
      Abnormal: Blocked extension (indicative of displaced meniscal fragment).

      Patellofemoral Dysfunction Tests
      Patellar instability and chondral pathology are evaluated through tracking and apprehension tests:

      - Patellar Apprehension Test
      Purpose: Identifies patellar instability or subluxation tendency.
      Technique: Patient supine, laterally displace patella while observing for facial grimacing or resistance.
      Normal: No apprehension or pain.
      Abnormal: Patient resists or expresses fear of dislocation (positive for instability).

      - Fairbank’s Apprehension Test
      Purpose: Alternative for patellar instability.
      Technique: Knee extended, apply lateral force to patella.
      Normal: No reaction.
      Abnormal: Apprehension or quadriceps contraction.

      - Clarke’s Sign
      Purpose: Detects patellofemoral pain syndrome.
      Technique: Patient supine, knee extended. Apply downward pressure on patella while patient contracts quadriceps.
      Normal: No pain or crepitus.
      Abnormal: Pain or inability to maintain contraction (chondromalacia patellae).

      Structured Palpation Protocol for Knee Joint Structures

      Systematic palpation of the knee joint identifies bony tenderness, ligamentous pathology, and soft-tissue abnormalities. The following table outlines key structures, their anatomical locations, and palpatory techniques, organized by region for efficiency.
      Structure Location Technique
      Patella Anterior knee, within quadriceps tendon and patellar ligament.
      • Palpate superior pole (quadriceps insertion), inferior pole (patellar tendon), and medial/lateral facets.
      • Assess for tenderness, effusion, or crepitus during active/passive motion.
      • Note patellar alignment (high/low riding, tilt, or subluxation).
      Patellar Ligament Inferior pole of patella to tibial tuberosity.
      • Palpate for thickness, tenderness, or nodules (e.g., Osgood-Schlatter disease).
      • Compare bilaterally for asymmetry.
      Joint Line (Menisci) Medial and lateral aspects of knee, ~1 cm proximal to tibial plateau.
      • Apply firm pressure along joint line with knee in extension and flexion.
      • Note tenderness, clicks, or pain with compression (suggestive of meniscal tears).
      • Medial joint line tenderness often indicates medial meniscus pathology.
      Medial Collateral Ligament (MCL) From medial femoral condyle to medial tibial plateau.
      • Palpate along ligament’s path with knee extended and flexed.
      • Assess for tenderness, swelling, or gaping with valgus stress.
      • Distinguish between superficial (MCL) and deep (medial meniscus) tenderness.
      Lateral Collateral Ligament (LCL) From lateral femoral condyle to fibular head.
      • Palpate with knee extended, noting tenderness or swelling.
      • Compare with contralateral side for asymmetry.
      • LCL injuries often present with varus laxity.
      Iliotibial Band (ITB) Lateral knee, from greater trochanter to Gerdy’s tubercle.
      • Palpate with knee extended and flexed to 30° to identify friction or tenderness.
      • Assess for ITB syndrome (pain with resisted hip abduction).
      Popliteal Fossa Structures

      Rehabilitation and Movement Optimization of the Knee Joint

      The restoration of knee joint function following injury or surgery requires a structured, phase-specific approach that balances biomechanical restoration, neuromuscular control, and progressive loading. Evidence-based rehabilitation protocols must account for tissue healing timelines, ligamentous or meniscal pathology, and the patient’s functional demands. Movement optimization integrates proprioceptive and dynamic stabilization techniques to minimize compensatory movement patterns, reduce reinjury risk, and restore sport- or activity-specific performance. This section outlines phase-specific exercise progression, comparative intervention strategies, and the neurophysiological integration of proprioceptive training to enhance joint awareness and functional recovery.

      Phase-Specific Exercise Progression for Knee Stability Restoration

      Rehabilitation following knee injury or surgery follows distinct phases—acute (0–2 weeks), subacute (2–6 weeks), and chronic (>6 weeks)—each with specific goals, exercise modalities, and progression criteria. The acute phase prioritizes pain management, edema reduction, and early neuromuscular activation, while the subacute phase introduces controlled range of motion (ROM) and closed-chain strengthening. The chronic phase emphasizes dynamic stability, plyometrics, and sport-specific drills, with progression contingent on clinical milestones such as pain-free ROM, normalized gait mechanics, and single-leg balance proficiency.

      Acute Phase (0–2 Weeks): Protection and Early Activation
      The primary objectives are minimizing joint effusion, restoring passive ROM, and initiating quadriceps activation without excessive stress on healing tissues. Cryotherapy, compression, and elevation remain cornerstone interventions, supplemented by:

    • Isometric quadriceps sets (3 sets × 10 seconds) to prevent atrophy and inhibit arthrogenic muscle inhibition.
    • Heel slides (seated or supine) for gentle patellar mobilization and early hamstring activation, limited to pain-free ranges.
    • Stationary cycling (low resistance) to promote blood flow without axial loading, initiated only after medical clearance (e.g., post-ACL reconstruction).
    • Electrical stimulation (NMES) for quadriceps activation in cases of severe inhibition or post-surgical immobility.
    • Progression Criteria for Acute Phase:
    • Pain-free passive ROM within 90° flexion and full extension (within 5° of contralateral limb).
    • Ability to perform isometric quadriceps holds for 10 seconds without compensatory hip hitching.
    • Minimal effusion (<1+ swelling) and no signs of joint irritation post-exercise.
    • Subacute Phase (2–6 Weeks): Controlled Mobility and Strength
      This phase transitions to closed-chain exercises, emphasizing co-contraction of quadriceps and hamstrings to stabilize the knee during functional movements. Open-chain exercises are avoided to reduce anterior tibial shear forces. Key interventions include:
    • Terminal knee extension (TKEs) to improve quadriceps activation and patellar tracking, progressing from seated to standing with manual resistance.
    • Mini-squats (0°–45° knee flexion) on stable surfaces to restore single-leg control, with emphasis on symmetrical weight distribution.
    • Step-ups (low height, 5–10 cm) to reintroduce dynamic loading while maintaining hip extension dominance.
    • Sliding board exercises for controlled anterior-posterior glide of the tibia, improving neuromuscular coordination.
    • Eccentric hamstring curls (seated or prone) to address quadriceps dominance and enhance posterior knee stability.
    • Progression Criteria for Subacute Phase:
    • Active ROM within 10° of contralateral limb (full extension and ≥120° flexion for most activities).
    • Ability to perform single-leg mini-squats (5 reps × 2 sets) without valgus collapse or compensatory trunk lean.
    • No effusion post-exercise; single-leg stance (10 seconds) on firm surface without assistance.
    • Chronic Phase (>6 Weeks): Dynamic Stability and Return to Function
      The focus shifts to high-demand activities, incorporating plyometrics, agility drills, and sport-specific movements. Proprioceptive challenges and resistance training are integrated to restore neuromuscular control under fatigue. Critical exercises include:
    • Single-leg deadlifts to improve hip-knee dissociation and core stability.
    • Lateral bounds and skater hops for multiplanar power generation, progressing from bilateral to unilateral.
    • Plyometric drop jumps (from 20–40 cm) to train reactive strength, with landing mechanics emphasizing knee alignment (avoiding excessive valgus).
    • Sport-specific agility drills (e.g., cutting drills for soccer, deceleration for basketball), incorporating cognitive load (e.g., reactionary starts).
    • Resisted terminal knee extension (RTKE) with bands to enhance quadriceps force production in late-range flexion.
    • Progression Criteria for Chronic Phase:
    • Pain-free single-leg squat to 90° with bodyweight or added resistance (e.g., goblet squat).
    • Ability to perform double-leg plyometrics (e.g., box jumps) with controlled landings before advancing to single-leg.
    • No effusion or joint line tenderness post-exercise; single-leg hop test distance ≥90% of contralateral limb.
    • Successful completion of sport-specific drills without compensatory movement patterns (e.g., trunk rotation to avoid knee valgus).
    • Comparative Analysis of Conservative vs. Surgical Interventions for Knee Pathologies

      The choice between conservative (non-operative) and surgical management of knee pathologies depends on the specific diagnosis, patient demographics, and functional goals. Below is a comparative table summarizing evidence-based outcomes for common knee conditions, including success rates, rehabilitation timelines, and functional recovery metrics. Data are derived from systematic reviews, randomized controlled trials (RCTs), and clinical practice guidelines (e.g., AAOS, ESSKA).
      Pathology Conservative Intervention Surgical Intervention Success Rate (Functional Outcome) Rehabilitation Timeline (Return to Activity) Key Limitations
      ACL Injury Rehabilitation-focused (no reconstruction) Anatomical ACL reconstruction (autograft/ allograft)
      • 30–50% return to pre-injury sport level (higher in low-demand athletes).
      • Risk of secondary meniscal/chondral injury: 20–30% at 5 years.
      • IKDC subjective score: 60–70/100.
      • Full weight-bearing: 2–4 weeks.
      • Return to sport: 6–9 months (with criteria-based progression).
      • Pivot-shift test normalization: 90% at 12 months.
      • High reinjury risk (15–20%) in non-compliant patients.
      • Limited evidence for non-copers in high-risk sports.
      • 90% return to sport at 2 years (RCTs).
      • IKDC score: 85–90/100.
      • Graft failure rate: 2–5% at 10 years.
      • Brace use: 6 weeks.
      • Criteria-based RTP: 7–12 months.
      • Full strength recovery: 12–18 months.
      • Surgical risks: Infection (1–2%), stiffness (5–10%).
      • Higher cost and donor-site morbidity (autograft).
      Meniscus Tears Physical therapy (PT) and activity modification Partial meniscectomy or meniscal repair
      • 50–60% improvement in pain/VAS scores.
      • 20–30% progression to osteoarthritis at 10 years.
      • Tegner score improvement: 3–4 points.
      • Partial meniscectomy: 2–4 weeks (weight-bearing as tolerated).
      • Meniscal repair: 6–12

        The knee joint’s classification as a modified hinge underscores its evolutionary adaptation to balance stability with mobility, a design that, while resilient, remains susceptible to mechanical failure under pathological or overuse conditions. From the precise articulation of the femoral condyles with the tibial plateau to the proprioceptive feedback provided by menisci and ligamentous receptors, every structural element plays a role in maintaining joint homeostasis. Clinical insights into pathologies such as ACL tears or osteoarthritis reveal not only the biomechanical consequences of instability but also the body’s compensatory mechanisms—ranging from altered muscle recruitment to joint effusion—which, if unaddressed, can accelerate degenerative changes. Rehabilitation strategies, from phase-specific exercise protocols to proprioceptive training, must therefore align with the knee’s inherent biomechanical constraints to restore function without compromising long-term joint integrity. Ultimately, this analysis highlights the knee’s status as a paradigm of musculoskeletal complexity, where anatomical precision, dynamic stability, and adaptive resilience converge to sustain human movement.

        FAQ

        Is the knee joint classified as a type of synovial joint, and if so, which specific subtype does it belong to?

        Yes, the knee is a synovial joint and specifically a hinge joint (primarily) with some modified plane joint characteristics (e.g., rotation during flexion). It’s the largest synovial joint in the body, featuring articulating surfaces covered by hyaline cartilage and enclosed in a fibrous capsule.

        What materials and structures make up the knee joint?

        The knee joint is composed of bone (femur, tibia, patella), articular cartilage (hyaline cartilage covering ends), ligaments (ACL, PCL, MCL, LCL), menisci (fibrocartilage cushions), synovial fluid (lubrication), and the joint capsule (fibrous outer layer + synovial membrane). Tendons (e.g., quadriceps, patellar) also reinforce stability.

        Leave a Comment

        Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.