Can a child be sedated at the dentist and how it works safely
Table of Contents
- Understanding Dental Sedation for Children: An Overview
- Purpose and Role of Sedation in Pediatric Dentistry
- Types of Dental Sedation for Children and Their Applications
- Prevalence of Dental Anxiety in Children and the Impact of Sedation
- Types of Sedation Used in Pediatric Dentistry: Pros, Cons, and Suitability
- Nitrous Oxide (Laughing Gas) Sedation: Mechanism and Application in Mild Anxiety
- Oral Sedation: Medication-Based Calm for Moderate Anxiety
- Intravenous (IV) Sedation: Precision and Real-Time Adjustment for Complex Procedures
- General Anesthesia in Pediatric Dentistry: Indications and Safety Protocols
Every child deserves a pain-free and anxiety-free dental visit, yet the fear of needles, drills, or even the dentist’s chair can turn routine check-ups into traumatic experiences. Dental sedation for children is not just a luxury but often a necessary tool to ensure their well-being, allowing dentists to perform critical procedures without distress. From mild cases of nervousness to complex treatments requiring multiple appointments, sedation transforms pediatric dentistry from a source of dread into a manageable, even positive experience.
Behind every sedation choice lies a careful balance of safety, effectiveness, and the child’s unique needs. Nitrous oxide, oral medications, intravenous sedation, and general anesthesia each serve distinct purposes, tailored to age, medical history, and the procedure’s complexity. Yet misconceptions persist—some parents question whether sedation is truly safe, while others assume it’s reserved only for extreme cases. This exploration delves into the science, benefits, and realities of pediatric dental sedation, backed by expert insights and real-world applications to demystify the process.

Understanding Dental Sedation for Children: An Overview
Dental sedation plays a pivotal role in pediatric dentistry by ensuring that children receive necessary dental care without experiencing undue anxiety, pain, or discomfort. For many children, even routine procedures like cavity fillings or cleanings can trigger fear due to unfamiliarity with dental tools, clinical environments, or past negative experiences. Sedation techniques allow dentists to create a calm, controlled environment, enabling them to perform treatments effectively while prioritizing the child’s emotional and physical well-being. This approach not only facilitates smoother procedures but also fosters long-term positive associations with dental visits, reducing the likelihood of dental phobia in adulthood. The use of sedation in pediatric dentistry is grounded in evidence-based practices, supported by decades of research and clinical guidelines. According to a 2021 study published in the Journal of the American Dental Association (JADA), approximately 20% of children exhibit moderate to severe dental anxiety, with younger children (ages 3–6) being particularly vulnerable. Sedation addresses these concerns by tailoring the level of relaxation to the child’s needs, ranging from mild sedation for cooperative children to deeper states for those with complex medical histories or extensive treatment requirements. By understanding the purpose, types, and applications of sedation, parents and caregivers can make informed decisions that align with their child’s dental health needs.
Purpose and Role of Sedation in Pediatric Dentistry
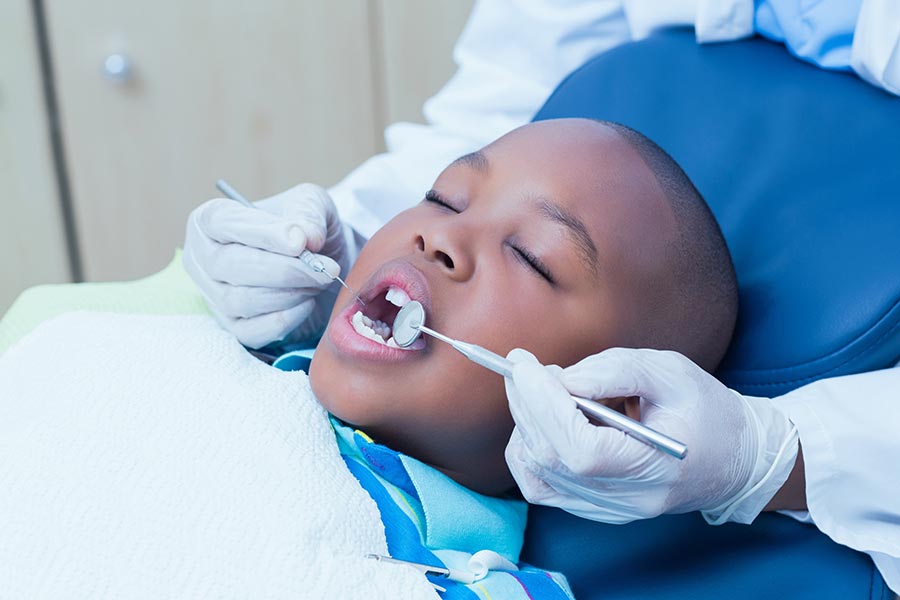 Sedation in pediatric dentistry serves multiple critical functions, primarily centered on anxiety management, pain control, and procedural efficiency. For children with dental anxiety or special needs, the fear of dental visits can lead to avoidance behaviors, resulting in untreated cavities, gum disease, or oral infections. Sedation mitigates these risks by inducing a state of relaxation, allowing dentists to complete treatments without distress. Additionally, sedation is beneficial for children who:
Beyond emotional comfort, sedation enhances procedural outcomes by reducing patient movement, which is crucial for precision in treatments like root canals or dental implants. A 2019 study in Pediatric Dentistry highlighted that children under sedation exhibited a 60% reduction in procedural anxiety compared to those without sedation, with dentists reporting improved access to hard-to-reach areas and fewer complications.
Types of Dental Sedation for Children and Their Applications
Dental sedation encompasses a spectrum of techniques, each tailored to the child’s age, medical history, and the complexity of the procedure. The four primary types—nitrous oxide, oral sedation, intravenous (IV) sedation, and general anesthesia—vary in depth, administration method, and recovery time. Below is a comparative analysis to illustrate their distinctions and appropriate use cases.
| Type of Sedation | How It Works | Common Uses in Pediatric Dentistry | Safety Profile | Recovery Time |
|---|---|---|---|---|
| Nitrous Oxide (Laughing Gas) | Administered via a nasal mask, nitrous oxide induces mild sedation by combining oxygen with a low concentration of nitrous oxide gas. The child remains conscious but experiences relaxation and euphoria. |

|
|
5–10 minutes post-procedure; children can resume normal activities immediately. |
| Oral Sedation | Involves the administration of sedative medications (e.g., halcion or valium) via liquid or pill form, taken 30–60 minutes before the procedure. The child enters a deeper state of relaxation but remains responsive. |
|
|
1–4 hours, depending on the medication and child’s metabolism. |
| Intravenous (IV) Sedation | Administered through an IV, IV sedation delivers sedative drugs directly into the bloodstream, allowing for precise control over the depth of sedation. The child may drift in and out of consciousness but can be easily aroused. |
|
|
30 minutes to 2 hours; children must rest for several hours post-procedure. |
| General Anesthesia | Induces a deep state of unconsciousness, where the child is completely unaware of the procedure. Administered by an anesthesiologist, it may involve IV drugs or inhaled gases. |
|
|
4–6 hours; children must be observed for 24 hours for any delayed reactions. |
The choice of sedation method depends on a multifactorial assessment, including the child’s age, medical history, and the dentist’s expertise. For instance, nitrous oxide is often the first-line option for cooperative children, while general anesthesia may be reserved for cases involving trauma, severe anxiety, or extensive treatment plans.
Prevalence of Dental Anxiety in Children and the Impact of Sedation
Dental anxiety is a widespread issue among children, with studies indicating that up to 25% of children experience significant fear during dental visits, often stemming from:
The consequences of untreated dental anxiety extend beyond the dental chair, including:
Sedation serves as a proactive solution by normalizing the dental experience for anxious children. A 2020 meta-analysis in The Journal of Dentistry for Children found
Types of Sedation Used in Pediatric Dentistry: Pros, Cons, and Suitability
Pediatric dentistry employs various sedation techniques tailored to a child’s age, anxiety level, and the complexity of the dental procedure. Sedation not only ensures comfort but also minimizes fear and movement during treatment, making it critical for both the child’s experience and the dentist’s ability to perform precise work. The choice of sedation method depends on factors such as the child’s medical history, the duration of the procedure, and the level of cooperation expected. Understanding the mechanisms, benefits, and limitations of each sedation type—ranging from mild nitrous oxide to deep general anesthesia—helps parents and dental professionals make informed decisions. This section explores the four primary sedation methods used in pediatric dentistry, their suitability for different scenarios, and the collaborative efforts of the dental team to ensure safety and efficacy.
Nitrous Oxide (Laughing Gas) Sedation: Mechanism and Application in Mild Anxiety
Nitrous oxide, commonly known as laughing gas, is a colorless and odorless gas administered through a nasal mask during dental procedures. Its mechanism involves binding to opioid receptors in the brain, producing a mild euphoric and analgesic effect while preserving the child’s ability to breathe independently and respond to verbal commands. The onset of sedation occurs within 2–5 minutes, and effects dissipate rapidly—typically within 3–5 minutes after discontinuing administration—due to its short half-life. This rapid reversibility makes nitrous oxide an ideal choice for short procedures (under 30–45 minutes) and children with mild anxiety or fear of the dental environment. The primary advantage of nitrous oxide lies in its minimal systemic effects and lack of significant side effects when used appropriately. Children remain conscious and cooperative, allowing the dentist to monitor their responsiveness throughout the procedure. However, it is not suitable for children with respiratory conditions (e.g., asthma, obstructive sleep apnea), severe anxiety, or those who cannot tolerate the nasal mask. Additionally, nitrous oxide is contraindicated in cases of first-trimester pregnancy or vitamin B12 deficiency, as prolonged exposure may exacerbate neurological symptoms. Real-World Application: Nitrous oxide is frequently used for routine cleanings, fluoride treatments, fillings, and simple extractions in children aged 4–12 years. For example, a 6-year-old with mild dental anxiety undergoing a cavity filling may benefit from nitrous oxide to reduce stress without the need for deeper sedation. The gas is also advantageous in special needs children who may not tolerate other sedation methods due to sensory sensitivities.
Oral Sedation: Medication-Based Calm for Moderate Anxiety
Oral sedation involves administering sedative medications (e.g., midazolam, hydroxyzine, or chloral hydrate) 30–60 minutes before the procedure to induce a relaxed, drowsy state. Unlike nitrous oxide, oral sedation affects the central nervous system, producing amnesia, reduced anxiety, and mild pain relief, but it does not eliminate consciousness. The dosage varies by age, weight, and medical history, with pediatric dentists typically prescribing low doses to avoid excessive sedation. Midazolam, a benzodiazepine, is the most commonly used oral sedative due to its fast onset (15–30 minutes) and short duration (1–4 hours). However, it may cause drowsiness, confusion, or nausea post-procedure. Hydroxyzine, an antihistamine with sedative properties, is preferred for children who cannot tolerate benzodiazepines, though its effects last longer (up to 6–8 hours), requiring parental supervision during recovery. Chloral hydrate, though effective, is less commonly used today due to its slow metabolism and higher risk of respiratory depression in some children. Ideal Candidates: Oral sedation is suitable for children aged 5–12 years with moderate anxiety or those requiring multiple procedures (e.g., multiple fillings, space maintainers). It is particularly useful for shy or highly sensitive children who may not respond well to nitrous oxide alone. However, it is contraindicated in children with:
Recovery Considerations: Children undergoing oral sedation must not drive or operate machinery for at least 24 hours due to potential residual drowsiness. Parents are advised to arrange for transportation and monitor for excessive sleepiness or vomiting in the hours following the procedure.
Intravenous (IV) Sedation: Precision and Real-Time Adjustment for Complex Procedures
IV sedation delivers sedative medications directly into the bloodstream, allowing immediate onset (within 30–60 seconds) and precise control over the depth of sedation. An anesthesiologist or dentist with advanced sedation certification administers the sedatives (e.g., propofol, midazolam, or fentanyl) while continuously monitoring vital signs (heart rate, oxygen saturation, blood pressure) via pulse oximetry, ECG, and capnography. This real-time adjustment ensures the child remains comfortable but responsive, with the ability to maintain an airway independently. Process Overview: 1. Pre-Procedure Assessment: The child’s medical history is reviewed to rule out contraindications (e.g., heart conditions, allergies to sedatives, or bleeding disorders). 2. IV Line Insertion: A small catheter is placed in the child’s arm or hand, and a local anesthetic is applied to minimize discomfort. 3. Titration of Sedatives: The sedative dose is gradually increased until the child reaches a desired level of relaxation, typically assessed using the Ramsay Sedation Scale (ranging from anxious to deep sedation). 4. Continuous Monitoring: The dental team observes for signs of oversedation (e.g., shallow breathing, reduced responsiveness) and adjusts the medication accordingly. 5. Recovery: Upon completion, the sedative effects wear off within 30–60 minutes, though children may experience mild grogginess or nausea. Suitability and Risks: IV sedation is ideal for longer procedures (e.g., multiple extractions, root canals, or orthodontic treatments) and children with severe anxiety or special needs. However, it requires higher monitoring intensity and is not recommended for children with:
Expert Insight: Dr. Emily Carter, a pediatric dentist specializing in sedation, notes:
"IV sedation is my go-to for children aged 7–16 undergoing extensive work, such as full-mouth reconstructions. The ability to titrate the drug in real-time ensures safety while keeping the child comfortable. However, it’s crucial to have an anesthesiologist present for high-risk cases."
Real-World Application: A 12-year-old requiring four wisdom teeth extractions may benefit from IV sedation to prevent movement and reduce pain perception. The controlled environment allows the dentist to complete the procedure efficiently while minimizing trauma for the child.
General Anesthesia in Pediatric Dentistry: Indications and Safety Protocols
General anesthesia induces a controlled, drug-induced unconsciousness, allowing the child to undergo complex or lengthy procedures without awareness or pain. Administered by an anesthesiologist in a hospital or specialized dental facility, it is reserved for cases where other sedation methods are ineffective or unsafe. The child is monitored via advanced equipment (e.g., bispectral index (BIS) monitoring for brain activity, endotracheal tube for airway management) throughout the procedure. When Is General Anesthesia Necessary? General anesthesia is typically recommended for:
Administration Methods: 1. Inhalation Anesthesia: Gases like sevoflurane or nitrous oxide are delivered via a mask. 2. IV Anesthesia: Medications such as propofol or ketamine are administered intravenously. 3. Combined Approach: Often, both inhalation and IV methods are used for rapid induction and maintenance. Recovery and Risks: Children typically recover in a post-anesthesia care unit (PACU) for 1–4 hours, with parental supervision required for at least 24 hours.
The answer to whether a child can be sedated at the dentist is a resounding yes—and it often marks the difference between a stressful visit and a seamless one. By understanding the nuances of each sedation method, recognizing the red flags that warrant deeper medical evaluation, and preparing thoughtfully, parents and dentists can collaborate to create an environment where even the youngest patients feel secure. Sedation is not just about numbing fear; it’s about empowering children to take control of their dental health without the shadow of anxiety looming over them.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.