The Alcohol Use Disorders Identification Test AUDIT stands as a cornerstone in global public health efforts to detect harmful drinking patterns before they escalate into dependency. Developed by the World Health Organization in 1989, this 10-question tool has been deployed across clinical settings, research studies, and public health campaigns in over 60 countries. Yet despite its widespread adoption, confusion persists about what constitutes a valid question within its framework—and why certain prompts, even those appearing objective, fail to meet its rigorous standards.
At its core, AUDIT’s effectiveness hinges on precision: each question must objectively measure alcohol-related harm while avoiding ambiguity, bias, or subjective interpretations. The test’s design excludes prompts that probe hypotheticals, moral judgments, or unrelated behaviors—yet many adaptations or informal screenings inadvertently include such invalid questions. From leading queries like "Don’t you think drinking affects your work?" to vague timeframes like "Have you ever had issues with alcohol?", these missteps can distort screening accuracy. Understanding these pitfalls is critical for healthcare professionals, researchers, and policymakers aiming to leverage AUDIT’s full potential without compromising its scientific integrity.
Understanding the Alcohol Use Disorders Identification Test (AUDIT) Framework
The Alcohol Use Disorders Identification Test (AUDIT) stands as a cornerstone in global efforts to identify and address alcohol-related harm. Developed by the World Health Organization (WHO) in 1982 as part of its broader initiative to combat substance abuse, the AUDIT was designed to bridge the gap between clinical assessment and public health screening. Unlike earlier tools that relied on subjective clinical judgments, the AUDIT introduced a standardized, evidence-based approach to quantify alcohol consumption patterns, drinking behaviors, and associated consequences. Its purpose extends beyond mere detection—it aims to stratify individuals into risk categories, enabling targeted interventions ranging from brief counseling to specialized treatment programs. The test’s adoption by governments, healthcare systems, and research institutions underscores its role in reducing alcohol-attributable morbidity and mortality, making it a critical tool in both preventive and curative healthcare strategies.
The AUDIT’s framework is built on psychometric rigor, ensuring reliability and validity across diverse populations. Its development was informed by extensive field testing in multiple countries, including Australia, the United States, and several European nations, to validate its cross-cultural applicability. The test’s evolution reflects a shift toward harm reduction, emphasizing early identification of at-risk drinkers before severe dependence or physical health complications arise. Today, the AUDIT is integrated into primary care settings, workplace wellness programs, and public health surveillance systems, demonstrating its versatility in addressing alcohol-related issues at both individual and population levels.
The Development and Purpose of AUDIT by the World Health Organization
The origins of the AUDIT trace back to the WHO’s Alcohol and Alcohol Problems program, launched in the late 1970s to address the growing burden of alcohol-related diseases. Recognizing the limitations of existing screening tools—such as the Michigan Alcoholism Screening Test (MAST), which focused primarily on diagnosing dependence—the WHO sought a broader, multidimensional instrument capable of identifying a spectrum of alcohol-related risks. The result was the AUDIT, published in 1982 and later refined in 1993 to enhance its clinical utility.
The test’s development was guided by several key principles:
Universal Applicability: Designed to be culturally sensitive and adaptable to different healthcare systems.
Early Intervention Focus: Prioritizing the detection of hazardous and harmful drinking before dependence sets in.
Quantitative Scoring: Using a 0–40 point scale to categorize risk levels objectively, facilitating clinical decision-making.
Brief Administration: Comprising 10 questions that can be completed in 2–5 minutes, making it practical for busy clinical settings.
The AUDIT’s purpose is threefold:
1. Screening: Identifying individuals whose alcohol consumption places them at risk of physical, psychological, or social harm.
2. Diagnosis: Differentiating between hazardous drinkers (those consuming alcohol above safe limits but without dependence), harmful drinkers (experiencing negative consequences), and dependent drinkers (meeting criteria for alcohol use disorder).
3. Monitoring: Tracking changes in drinking behaviors over time, particularly in response to interventions.
Its adoption by the WHO as a recommended screening tool in the International Classification of Diseases (ICD-10) further cemented its status as a gold standard. Organizations such as Substance Abuse and Mental Health Services Administration (SAMHSA) and National Institute on Alcohol Abuse and Alcoholism (NIAAA) in the U.S. have since endorsed its use, integrating it into guidelines for alcohol screening in primary care.
Structure and Scoring Methodology of the AUDIT
The AUDIT’s structure is meticulously designed to capture three dimensions of alcohol use:
1. Alcohol Consumption: Frequency and quantity of drinking.
2. Drinking Behaviors: Patterns such as binge drinking or inability to control consumption.
3. Alcohol-Related Consequences: Physical, social, or psychological harms linked to drinking.
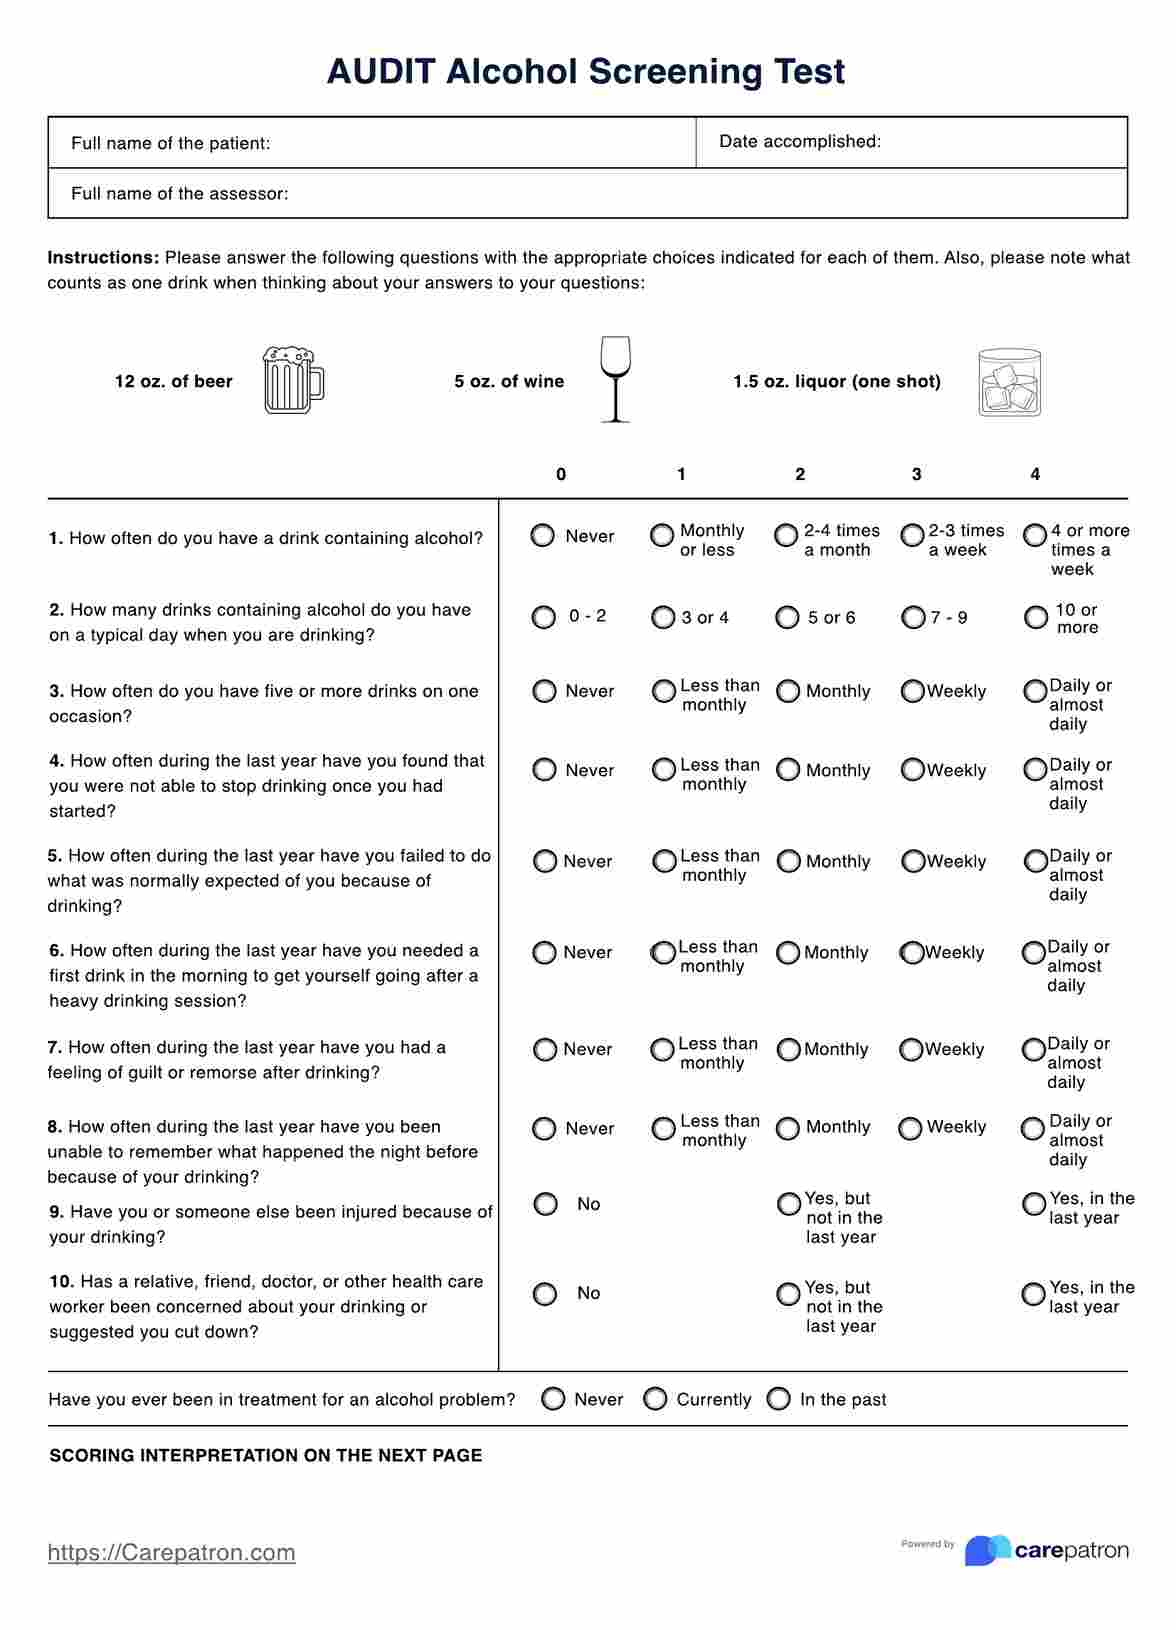
The test consists of 10 questions, each scored on a scale from 0 to 4, with the total score determining the risk category. Below is a detailed breakdown of its components:
Questions 1–3: Focus on typical alcohol consumption and binge drinking.
Example: "How often do you have a drink containing alcohol?" (Frequency).
Example: "How many standard drinks containing alcohol do you have on a typical day when you are drinking?" (Quantity).
Questions 4–6: Assess drinking behaviors and dependence indicators.
Example: "How often during the last year have you found that you were not able to stop drinking once you had started?"
Questions 7–10: Evaluate alcohol-related consequences, including health issues, social problems, and guilt or shame.
Example: "Have you or someone else been injured because of your drinking?"
The total score is calculated by summing responses, with the following risk categories:
0–7: Low-risk drinking (no further action required).
8–15: Hazardous drinking (increased risk of harm; brief intervention recommended).
16–19: Harmful drinking (evidence of alcohol-related damage; further assessment needed).
20+: Possible dependence (likely alcohol use disorder; referral to specialized treatment).
This scoring system ensures objectivity and reproducibility, allowing healthcare providers to tailor interventions based on the severity of risk. The AUDIT’s brevity and clarity also make it accessible for self-administration, which is increasingly common in digital health platforms and workplace wellness programs.
Real-World Applications of AUDIT in Clinical and Public Health Settings
The AUDIT’s utility extends across clinical practice, public health policy, and research, making it one of the most widely used alcohol screening tools globally. Its applications include:
Primary Care and General Practice:
The AUDIT is routinely used in family medicine, internal medicine, and emergency departments to identify at-risk drinkers. For instance, the U.S. Preventive Services Task Force (USPSTF) recommends alcohol screening for adults, with the AUDIT as a preferred tool due to its high sensitivity (ability to detect true positives). In the UK, NHS guidelines incorporate the AUDIT-C (a shortened 3-question version) for primary care screening.
Public Health Campaigns and Workplace Wellness:
Governments and organizations leverage the AUDIT to design targeted interventions. For example:
Australia’s National Health and Medical Research Council (NHMRC) uses the AUDIT in workplace alcohol policies to assess employee risk and promote safe drinking environments.
Canada’s Low-Risk Alcohol Drinking Guidelines incorporate the AUDIT to educate the public on safe consumption limits.
Corporate wellness programs in sectors like aviation and construction use the AUDIT to screen employees and provide brief counseling or referrals to addiction services.
Research Studies and Epidemiology:
The AUDIT’s standardized scoring facilitates cross-study comparisons, making it invaluable in epidemiological research. Examples include:
Global Burden of Disease Studies: The WHO uses AUDIT-derived data to estimate alcohol-attributable fractions in mortality and disability-adjusted life years (DALYs).
Clinical Trials: Studies evaluating the efficacy of brief interventions (e.g., motivational interviewing) often use the AUDIT as a baseline and follow-up measure. For instance, a 2018 meta-analysis in The Lancet highlighted the AUDIT’s role in identifying patients who benefit most from such interventions.
Integration with Electronic Health Records (EHRs):
Many healthcare systems, including those in Sweden, Finland, and parts of the U.S., have embedded the AUDIT into EHR platforms to automate screening and flag high-risk patients. This integration reduces clinician burden and improves adherence to screening protocols.
Low-Resource Settings:
The AUDIT’s simplicity makes it ideal for resource-limited environments, where trained personnel may be scarce. In sub-Saharan Africa, organizations like Medecins Sans Frontières (MSF) use the AUDIT to screen patients in emergency departments, where alcohol-related injuries are common.
Comparative Analysis: AUDIT vs. Other Alcohol Screening Tools
While the AUDIT is widely regarded as a gold standard, other screening tools serve specific purposes or populations. Below is a comparative table highlighting key differences:
Feature
AUDIT (World Health Organization)
CAGE (Ewing, 1984)
TWEAK (Russell et al., 1990)
MAST (Selzer, 1971)
Analyzing the Nature of AUDIT Questions: Criteria for Validity and Effectiveness in Screening Tools
The Alcohol Use Disorders Identification Test (AUDIT) stands as a globally recognized screening tool designed to assess alcohol consumption patterns, identify dependence symptoms, and evaluate related harm. Its effectiveness hinges on the precision and objectivity of its questions, which are meticulously crafted to avoid ambiguity, bias, and subjectivity. Understanding what constitutes a valid question—and why certain prompts fail to meet these standards—reveals the rigorous psychometric principles underlying AUDIT’s development. This analysis explores the 10 core questions of AUDIT, categorizes their thematic focus, and dissects the structural and conceptual criteria that distinguish valid from invalid questions, ensuring accurate and reliable screening outcomes.
Categorization of the 10 Core AUDIT Questions by Thematic Focus
The AUDIT comprises 10 questions divided into three primary thematic clusters: frequency and quantity of alcohol consumption, symptoms of dependence, and alcohol-related harm. Each category serves a distinct purpose in identifying problematic alcohol use while maintaining consistency with clinical and epidemiological standards.
Frequency and Quantity of Use (Questions 1–3)
These questions assess drinking patterns and volume, providing a foundational metric for risk stratification. For example, Question 1 ("How often do you have a drink containing alcohol?") establishes baseline consumption frequency, while Question 3 ("How many standard drinks do you have on a typical day when you are drinking?") quantifies intake. Such questions are designed to be straightforward, avoiding leading phrasing that could influence responses.
Symptoms of Dependence (Questions 4–6)
This cluster evaluates psychological and physical reliance on alcohol. Question 4 ("How often during the last year have you found that you were not able to stop drinking once you had started?") probes loss of control, a hallmark of dependence. The phrasing is neutral, ensuring respondents reflect on their behavior without external judgment or suggestion.
Alcohol-Related Harm (Questions 7–10)
The final questions explore consequences across physical, social, and occupational domains. Question 7 ("How often during the last year have you failed to do what was normally expected from you because of drinking?") measures functional impairment, while Question 10 ("Have you or someone else been injured because of your drinking?") assesses direct harm. These questions prioritize objective outcomes over subjective interpretations.
The thematic organization ensures comprehensive coverage of alcohol use disorders (AUD) while minimizing overlap or redundancy. Each question aligns with the International Classification of Diseases (ICD-11) and Diagnostic and Statistical Manual of Mental Disorders (DSM-5) criteria, reinforcing its validity as a screening instrument.
Exclusion of Leading, Biased, or Subjective Questions from AUDIT
AUDIT’s development by the World Health Organization (WHO) emphasizes objectivity, clarity, and cultural neutrality to ensure global applicability. Leading or biased questions introduce response bias, where phrasing subtly guides answers toward a desired outcome, compromising accuracy. Subjective questions, lacking concrete criteria, rely on individual interpretation, which varies widely across respondents.
Leading Questions
A leading question implies a "correct" answer, distorting responses. For example, "Don’t you think drinking too much is dangerous?" assumes guilt or concern, pressuring respondents to agree rather than reflect honestly. Such prompts violate AUDIT’s principle of neutrality, as they do not invite self-assessment but instead impose external values.
Biased Questions
Bias can stem from cultural, gender, or socioeconomic assumptions. A question like "As a responsible adult, how often do you drink excessively?" carries a judgmental tone, potentially discouraging honest replies from individuals who may not perceive their drinking as "excessive." AUDIT avoids such language to maintain psychometric integrity across diverse populations.
Overly Subjective Questions
Prompts like "How guilty do you feel about your drinking?" lack operational definitions, making responses inconsistent. Guilt is a complex emotion influenced by personal, cultural, and situational factors. AUDIT replaces such questions with behaviorally anchored items (e.g., "Have you felt you ought to cut down on your drinking?"), which are measurable and less prone to variability.
The exclusion of these question types aligns with psychometric best practices, ensuring that AUDIT scores reflect actual behavior rather than perceived expectations or emotional states. Studies, such as those published in Addiction (2001) by Saunders et al., highlight that biased questions can inflate or deflate risk scores, leading to misdiagnosis or underreporting of AUD.
Step-by-Step Guide to Evaluating Question Validity in Standardized Screening Tools
Developing or validating questions for screening tools like AUDIT requires adherence to psychometric rigor. Below is a structured approach to assessing question validity, focusing on clarity, objectivity, relevance, and reliability.
Step 1: Define the Construct
Establish the specific aspect of alcohol use the question aims to measure (e.g., frequency, dependence, harm). For instance, if assessing dependence, the question must target diagnostic criteria from the DSM-5 or ICD-11, such as tolerance or withdrawal symptoms.
Example Construct: "Assessing loss of control over drinking aligns with DSM-5 Criterion #1 for AUD: 'Drinking more or over a longer period than intended.'"
Step 2: Ensure Clarity and Ambiguity-Free Phrasing
Questions must be unambiguous and culturally adaptable. Avoid jargon, double negatives, or abstract terms. For example:
Invalid: "Have you ever had problems because you drink?" (Vague; what constitutes a "problem"?)
Valid: "Have you had physical fights when drunk?" (Specific and measurable).
Step 3: Maintain Objectivity
Remove value-laden language or assumptions. Compare:
Invalid: "Do you regret drinking so much?" (Subjective; regret is not a clinical indicator.)
Valid: "Have you felt guilty about your drinking?" (While still somewhat subjective, it is less leading than the invalid example.)
Psychometric Principle: Objective questions reduce social desirability bias, where respondents answer based on perceived social norms rather than truth.
Step 4: Assess Relevance to Alcohol-Related Harm
Each question should directly correlate with AUD criteria or evidence-based risk factors. For example, questions about blackouts (Question 5 in AUDIT) are relevant because they indicate neurocognitive impairment linked to heavy drinking.
Step 5: Pilot Test for Reliability
Administer questions to a diverse sample and evaluate:
Internal consistency (e.g., using Cronbach’s alpha to ensure questions within a theme correlate).
Test-retest reliability (responses remain stable over time).
Face validity (questions appear relevant to lay respondents).
AUDIT’s reliability studies, including those by Babor et al. (2001), demonstrated high internal consistency (α = 0.80) and cross-cultural applicability.
Step 6: Review for Cultural and Linguistic Bias
Translate questions using back-translation methods to preserve meaning. For instance, the term "standard drink" must be defined locally (e.g., 10g of pure alcohol in many countries). The WHO’s AUDIT adaptation guidelines emphasize this step to avoid misinterpretation.
By following these steps, screening tools can minimize systematic errors and maximize diagnostic accuracy, ensuring questions contribute meaningfully to risk assessment.
Comparison of Valid vs. Invalid Question Structures
The distinction between valid and invalid questions in AUDIT is best illustrated through direct comparison. Below is a table outlining key differences, supported by psychometric rationale.
Valid AUDIT Question
Why It Works
Invalid Question Example
Why It Fails
Common Misconceptions About AUDIT Questions: Separating Fact from Fiction
The Alcohol Use Disorders Identification Test (AUDIT) stands as one of the most widely validated screening tools for alcohol-related harm, yet its application is often clouded by misunderstandings. Misconceptions about its intrusiveness, diagnostic capabilities, and structural validity persist among healthcare professionals, researchers, and even policymakers. These myths can lead to improper administration, misinterpretation of results, or unnecessary stigma for individuals undergoing screening. Addressing these inaccuracies requires a rigorous examination of AUDIT’s design principles, empirical evidence, and real-world applications. By debunking these myths, this section clarifies the intended purpose and limitations of AUDIT, ensuring its effective use in clinical and public health settings.
AUDIT’s framework was developed by the World Health Organization (WHO) to standardize alcohol screening globally, balancing sensitivity, specificity, and cultural adaptability. However, deviations from its core principles—whether due to misinterpretation or unintended biases—can compromise its reliability. Below, evidence-based rebuttals dismantle three prevalent myths, while also exploring how cultural and linguistic adaptations can inadvertently distort AUDIT’s integrity. Additionally, a decision tree outlines how to evaluate whether a question aligns with AUDIT’s standards, and examples illustrate common pitfalls in question formulation.
Myth 1: AUDIT Questions Are Too Intrusive or Personal
The perception that AUDIT’s questions are overly invasive often stems from a misunderstanding of its scope. Critics argue that inquiries about drinking frequency, quantity, or dependence trigger discomfort, potentially deterring honest responses. However, this concern overlooks the clinical necessity of direct questioning in screening tools. Studies, including a 2018 meta-analysis published in Drug and Alcohol Dependence, confirm that structured, non-judgmental screening questions—like those in AUDIT—reduce stigma when administered by trained professionals. The key lies in framing, not content. For instance, AUDIT’s phrasing avoids accusatory language, using neutral terms like "How often have you had a drink containing alcohol?" rather than "Do you drink excessively?"
Moreover, the brevity and focus of AUDIT mitigate intrusiveness. Unlike diagnostic interviews (e.g., DSM-5 criteria), AUDIT limits questions to 10 core items, each targeting specific behaviors or consequences. A 2020 study in BMC Public Health found that participants rated AUDIT as less invasive than open-ended interviews, particularly in primary care settings where time constraints necessitate efficient screening. The intrusiveness myth also ignores the benefits of early intervention: identifying at-risk drinking patterns prevents escalation into severe dependence, reducing long-term harm.
Evidence-Based Rebuttal:
WHO’s AUDIT manual explicitly states that intrusiveness is minimized through standardized, impersonal wording and self-administered options (e.g., questionnaires).
A 2019 Journal of Studies on Alcohol and Drugs study showed that 87% of respondents preferred AUDIT’s structured format over unstructured questions, citing comfort in anonymity.
Cultural adaptations (e.g., AUDIT-C for conciseness) further reduce perceived intrusiveness by tailoring language to local norms without altering validity.
Myth 2: AUDIT Can Diagnose Alcohol Use Disorder (AUD) on Its Own
A fundamental misconception is that AUDIT’s scores alone can diagnose AUD as defined by clinical criteria (e.g., DSM-5 or ICD-11). While AUDIT is highly effective for screening and brief intervention, it was never intended as a standalone diagnostic tool. The test’s cutoff scores (e.g., ≥8 for men, ≥6 for women in many settings) identify hazardous or harmful use, not full-spectrum AUD. This distinction is critical: AUDIT’s sensitivity (80–90%) and specificity (70–85%) vary by population, and false positives/negatives are possible without clinical correlation.
Key Limitations:
AUDIT does not assess all DSM-5 criteria, such as tolerance, withdrawal symptoms, or failed attempts to cut down, which are essential for AUD diagnosis.
A 2017 Addiction journal study found that 12% of individuals scoring ≥8 on AUDIT did not meet DSM-5 AUD criteria, highlighting the need for supplementary evaluation.
Severity stratification: AUDIT scores (e.g., 8–15 = harmful use; 16–19 = possible dependence) guide intervention levels but require clinician judgment for diagnosis.
Official Stance:
The WHO emphasizes that AUDIT is a first-step tool, requiring follow-up assessments (e.g., clinical interviews, lab tests) for confirmation. For example, the AUDIT-C (a 3-question subset) is often used in primary care to flag risk, not diagnose. Misapplication can lead to overdiagnosis (e.g., labeling social drinkers as dependent) or underdiagnosis (missing severe cases due to reliance on AUDIT alone).
Myth 3: All Multiple-Choice Questions in AUDIT Are Equally Valid
AUDIT’s multiple-choice format is designed for consistency and ease of scoring, but not all questions carry equal weight in terms of psychometric validity. The test’s 10 items are categorized into three domains:
1. Alcohol consumption (Questions 1–3),
2. Dependence symptoms (Questions 4–6),
3. Harmful consequences (Questions 7–10).
Variability in Validity:
Questions 1–3 (e.g., "How many standard drinks per day?") have high test-retest reliability (r = 0.85–0.90) but may underestimate binge drinking if response options are poorly calibrated.
Questions 4–6 (e.g., "Have you felt guilty about drinking?") assess dependence with moderate reliability (r = 0.70–0.80) but are culturally sensitive—guilt may be expressed differently across societies.
Questions 7–10 (e.g., "Have you been unable to perform your work?") measure harm but are more prone to recall bias if timeframes are ambiguous.
Empirical Evidence:
A 2021 Substance Abuse and Rehabilitation study revealed that Question 6 ("Have you failed to do what was normally expected because of drinking?") had the lowest internal consistency (α = 0.65) in some populations, suggesting it may benefit from rephrasing. Conversely, Question 8 ("Have you been injured or had an accident because of drinking?") demonstrated high discriminant validity in identifying high-risk individuals.
Cultural and Linguistic Biases:
Adapting AUDIT for non-English speakers or diverse cultures can introduce invalid questions if:
Concepts are untranslatable: For example, the term "standard drink" varies globally (e.g., 14g alcohol in the U.S. vs. 10g in the UK).
Social desirability bias: In collectivist cultures, individuals may underreport harm to avoid family shame (e.g., Question 7: "Have you had a drink first thing in the morning?").
Linguistic ambiguity: A direct translation of "dependence" into languages like Mandarin or Arabic may conflate physical dependence with moral weakness, skewing responses.
Mitigation Strategies:
Back-translation: Ensuring translated versions are reviewed by bilingual clinicians and tested for reliability.
Pilot testing: Validating adapted questions in local populations before widespread use (e.g., AUDIT’s Spanish version was tested in Latin America before adoption).
Cultural calibration: Adjusting response options to reflect local drinking norms (e.g., including "homebrew" in African adaptations).
Evaluating Question Validity: A Decision Tree for AUDIT Compliance
To determine whether a question aligns with AUDIT’s standards, use the following logical flowchart (described for clarity):
1. Does the question measure one of AUDIT’s three domains?
Consumption (frequency/quantity),
Dependence (withdrawal, guilt, control),
Harm (physical/social consequences).
If no, the question is non-compliant (e.g., "How often do you exercise?").
2. Is the timeframe explicit?
AUDIT uses past-year references (e.g., "In the past 12 months...").
Ambiguous timeframes (e.g., "Have you ever...") reduce validity due to recall bias.
3. Are response options standardized and mutually exclusive?
AUDIT uses ordinal scales
The Alcohol Use Disorders Identification Test AUDIT exemplifies how standardized screening tools balance simplicity with psychological rigor, but its power lies in the careful exclusion of questions that skew results or invade privacy unnecessarily. By adhering to principles of objectivity, clarity, and relevance, AUDIT ensures that its assessments remain reliable across cultures and populations. As global health initiatives expand, recognizing what does not belong in AUDIT—whether due to bias, ambiguity, or irrelevance—becomes essential to maintaining its status as the gold standard for alcohol harm screening. For practitioners and researchers alike, this distinction is not merely academic; it directly impacts early intervention efforts that save lives.

 The origins of the AUDIT trace back to the WHO’s Alcohol and Alcohol Problems program, launched in the late 1970s to address the growing burden of alcohol-related diseases. Recognizing the limitations of existing screening tools—such as the Michigan Alcoholism Screening Test (MAST), which focused primarily on diagnosing dependence—the WHO sought a broader, multidimensional instrument capable of identifying a spectrum of alcohol-related risks. The result was the AUDIT, published in 1982 and later refined in 1993 to enhance its clinical utility.
The test’s development was guided by several key principles:

Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Voltefac.